Related Experiment Video
Updated: Aug 12, 2026


A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
Decrease in the incidence of post-dural puncture headache: maintaining CSF volume
1Department of Anesthesiology, University of California San Diego, USA. kkuczkowski@ucsd.edu

The incidence of epidural needle-induced post-dural puncture headache (PDPH) in parturients following dural puncture with a large bore (18-gauge) needle has been reported to range 76-85%. We describe seven cases in which the performance of epidural anesthesia in parturients was complicated by an unintentional dural puncture with an 18-gauge epidural needle. In all seven cases, the unintentional dural puncture was followed by (i) injection of the CSF in the glass syringe back into the subarachnoid space through the epidural needle, (ii) insertion of a epidural catheter into the subarachnoid space (now referred to as an intrathecal catheter), (iii) injection of a small amount of preservative free saline (3-5 ml) into the subarachnoid space through the intrathecal catheter, (iv) administration of bolus and then continuous intrathecal labor analgesia through the intrathecal catheter and then (v) leaving the intrathecal catheter in-situ for a total of 12-20 h. PDPH occurred in only one of these cases (14%).
The incidence of epidural needle-induced post-dural puncture headache (PDPH) in parturients following dural puncture with a large bore (18-gauge) needle has been reported to range 76-85%. We describe seven cases in which the performance of epidural anesthesia in parturients was complicated by an unintentional dural puncture with an 18-gauge epidural needle. In all seven cases, the unintentional dural puncture was followed by (i) injection of the CSF in the glass syringe back into the subarachnoid space through the epidural needle, (ii) insertion of a epidural catheter into the subarachnoid space (now referred to as an intrathecal catheter), (iii) injection of a small amount of preservative free saline (3-5 ml) into the subarachnoid space through the intrathecal catheter, (iv) administration of bolus and then continuous intrathecal labor analgesia through the intrathecal catheter and then (v) leaving the intrathecal catheter in-situ for a total of 12-20 h. PDPH occurred in only one of these cases (14%).
Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:21
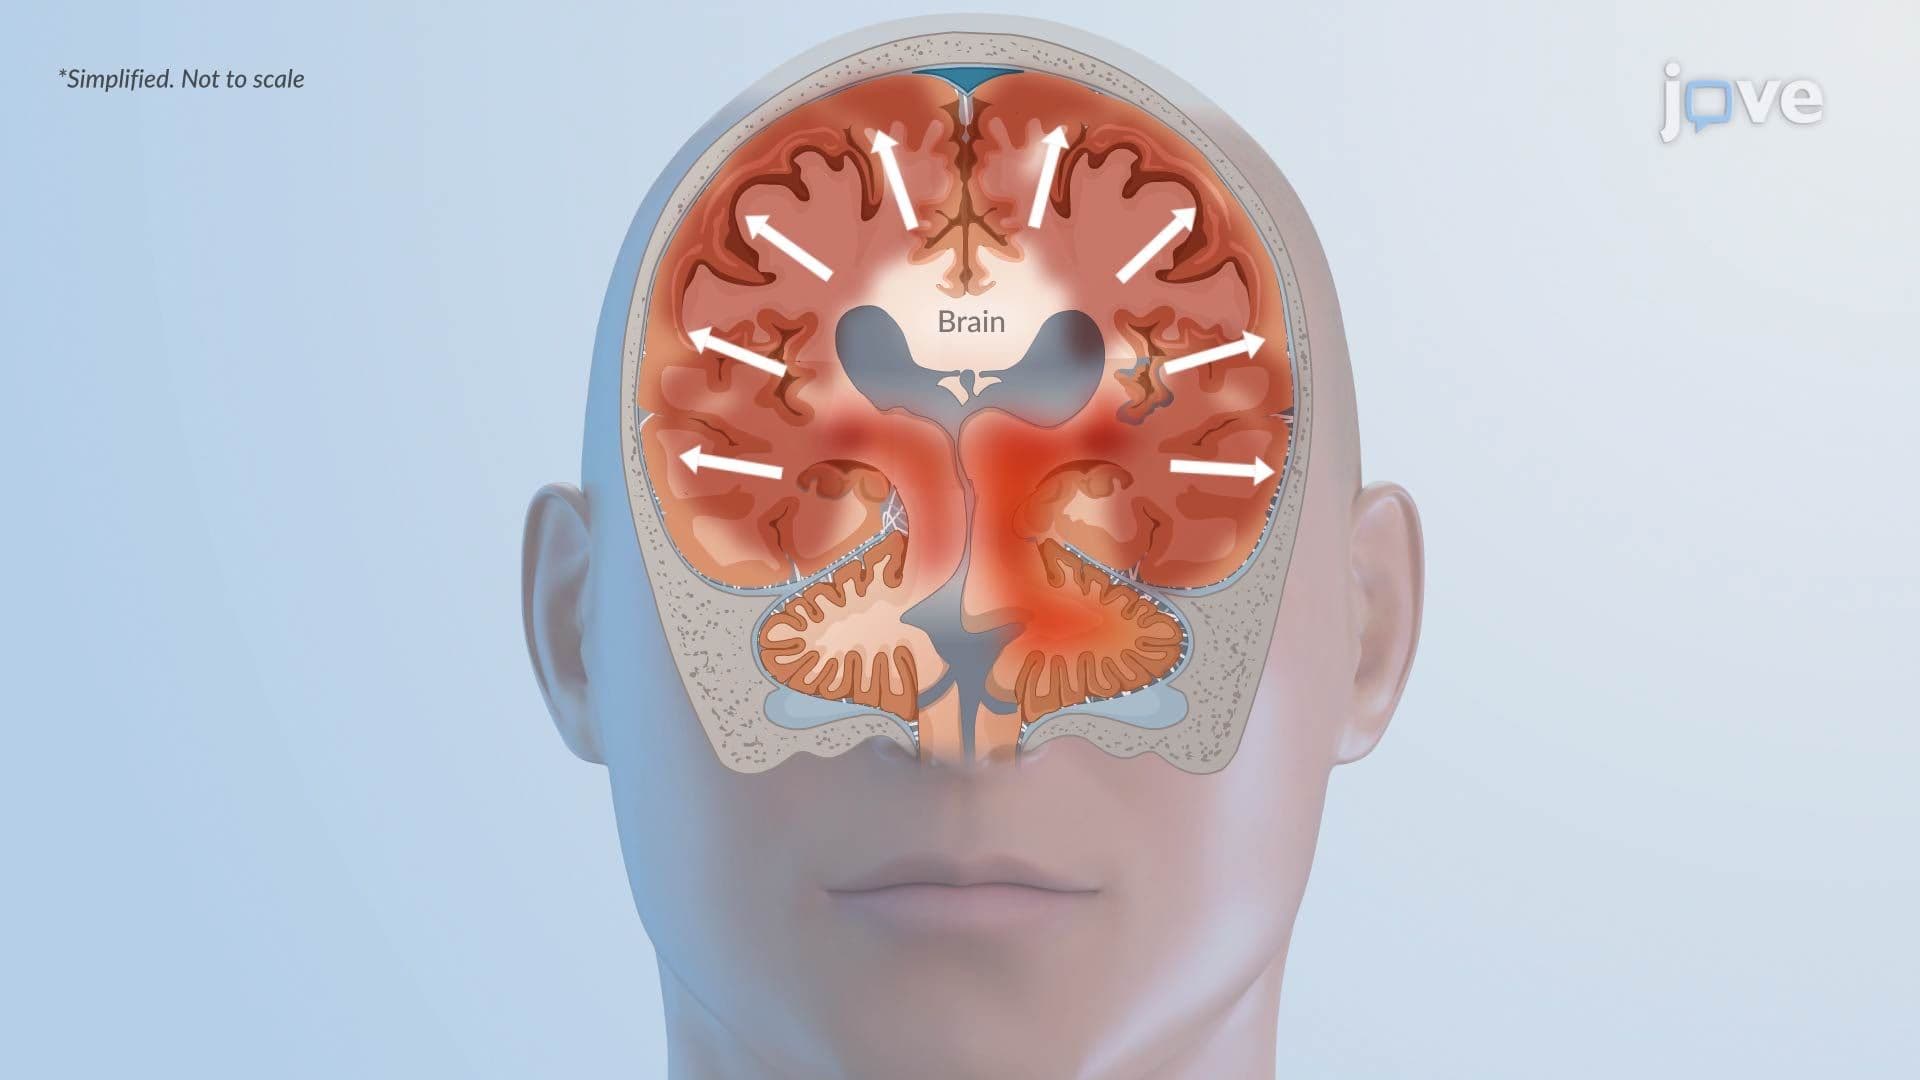
Cytotoxic Edema: Pathophysiology