Related Experiment Video
Updated: Aug 12, 2026
Histological Quantification of Chronic Myocardial Infarct in Rats
Published on: December 11, 2016
[Relationship between myocardial viability and ventricular late potentials in patients with history of myocardial

Insights
Patients with viable myocardium after myocardial infarction are more likely to have ventricular late potentials and arrhythmias. This finding highlights the importance of assessing myocardial viability for risk stratification in post-infarction patients.
Area of Science:
- Cardiology
- Electrophysiology
- Cardiac Imaging
Context:
- Myocardial infarction survivors are at risk for ventricular arrhythmias.
- Assessing myocardial viability is crucial for risk stratification.
- Late ventricular potentials (LVPs) are potential predictors of arrhythmias.
Purpose:
- To investigate the relationship between viable myocardium and the presence of LVPs in myocardial infarction survivors.
- To determine if dobutamine stress echocardiography (DSE) can identify patients at higher risk for arrhythmias based on myocardial viability.
Summary:
- This study analyzed 34 myocardial infarction survivors using high-resolution ECG, DSE, and Holter monitoring.
- Patients with viable (hibernating) myocardium detected by DSE showed a significantly higher incidence of LVPs (61.1%) compared to those with irreversible dysfunction (18.7%).
- Viable myocardium was associated with a higher prevalence of high-grade ventricular arrhythmias, though no direct correlation was found with Lown grade.
Impact:
- Dobutamine stress echocardiography can help identify myocardial infarction survivors at increased risk for ventricular arrhythmias by detecting viable myocardium.
- The presence of viable myocardium is a significant predictor of late ventricular potentials and high-grade ventricular arrhythmias.
- Findings contribute to improved risk stratification and management strategies for patients post-myocardial infarction.
Aim:
To study relationship between presence and volume of viable myocardium and registration of late ventricular potentials in patients with history of myocardial infarction.
Material And Methods:
High resolution ECG, dobutamine stress echocardiography and Holter ECG monitoring were carried out 34 patients (mean age 54.1-/+3.1 years) with history of documented myocardial infarction.
Results:
According to data of dobutamine stress echo patients were divided into 2 groups: with irreversible myocardial dysfunction (n=16, group 1) and with hibernating myocardium (n=18, group 2). Ventricular late potentials were registered in 3 (18.7%) and 11 (61,1%) patients in groups 1 and 2, respectively. Group 2 patients more often had high-grade ventricular arrhythmias. There was no association between presence of ventricular late potentials and Lown grade of ventricular arrhythmias on Holter ECG. Duration of filtered QRS (QRSt) complex correlated directly with index of regional wall motion abnormality, end-diastolic volume, and negatively - with total ejection fraction.
Conclusion:
Among myocardial infarction survivors patients in whom dobutamine stress echo detects viable myocardium significantly more often have ventricular late potentials and high grade ventricular arrhythmias compared with patients with myocardial scars without viable myocardium.
More Related Videos
 14:35
Post-Myocardial Infarction Heart Failure in Closed-chest Coronary Occlusion/Reperfusion Model in Göttingen Minipigs and Landrace Pigs
Published on: April 17, 2021
 08:19
Transthoracic Echocardiography to Assess Post-Resuscitation Left Ventricular Dysfunction After Acute Myocardial Infarction and Cardiac Arrest in Pigs
Published on: July 12, 2022
Related Concept Videos
 01:30
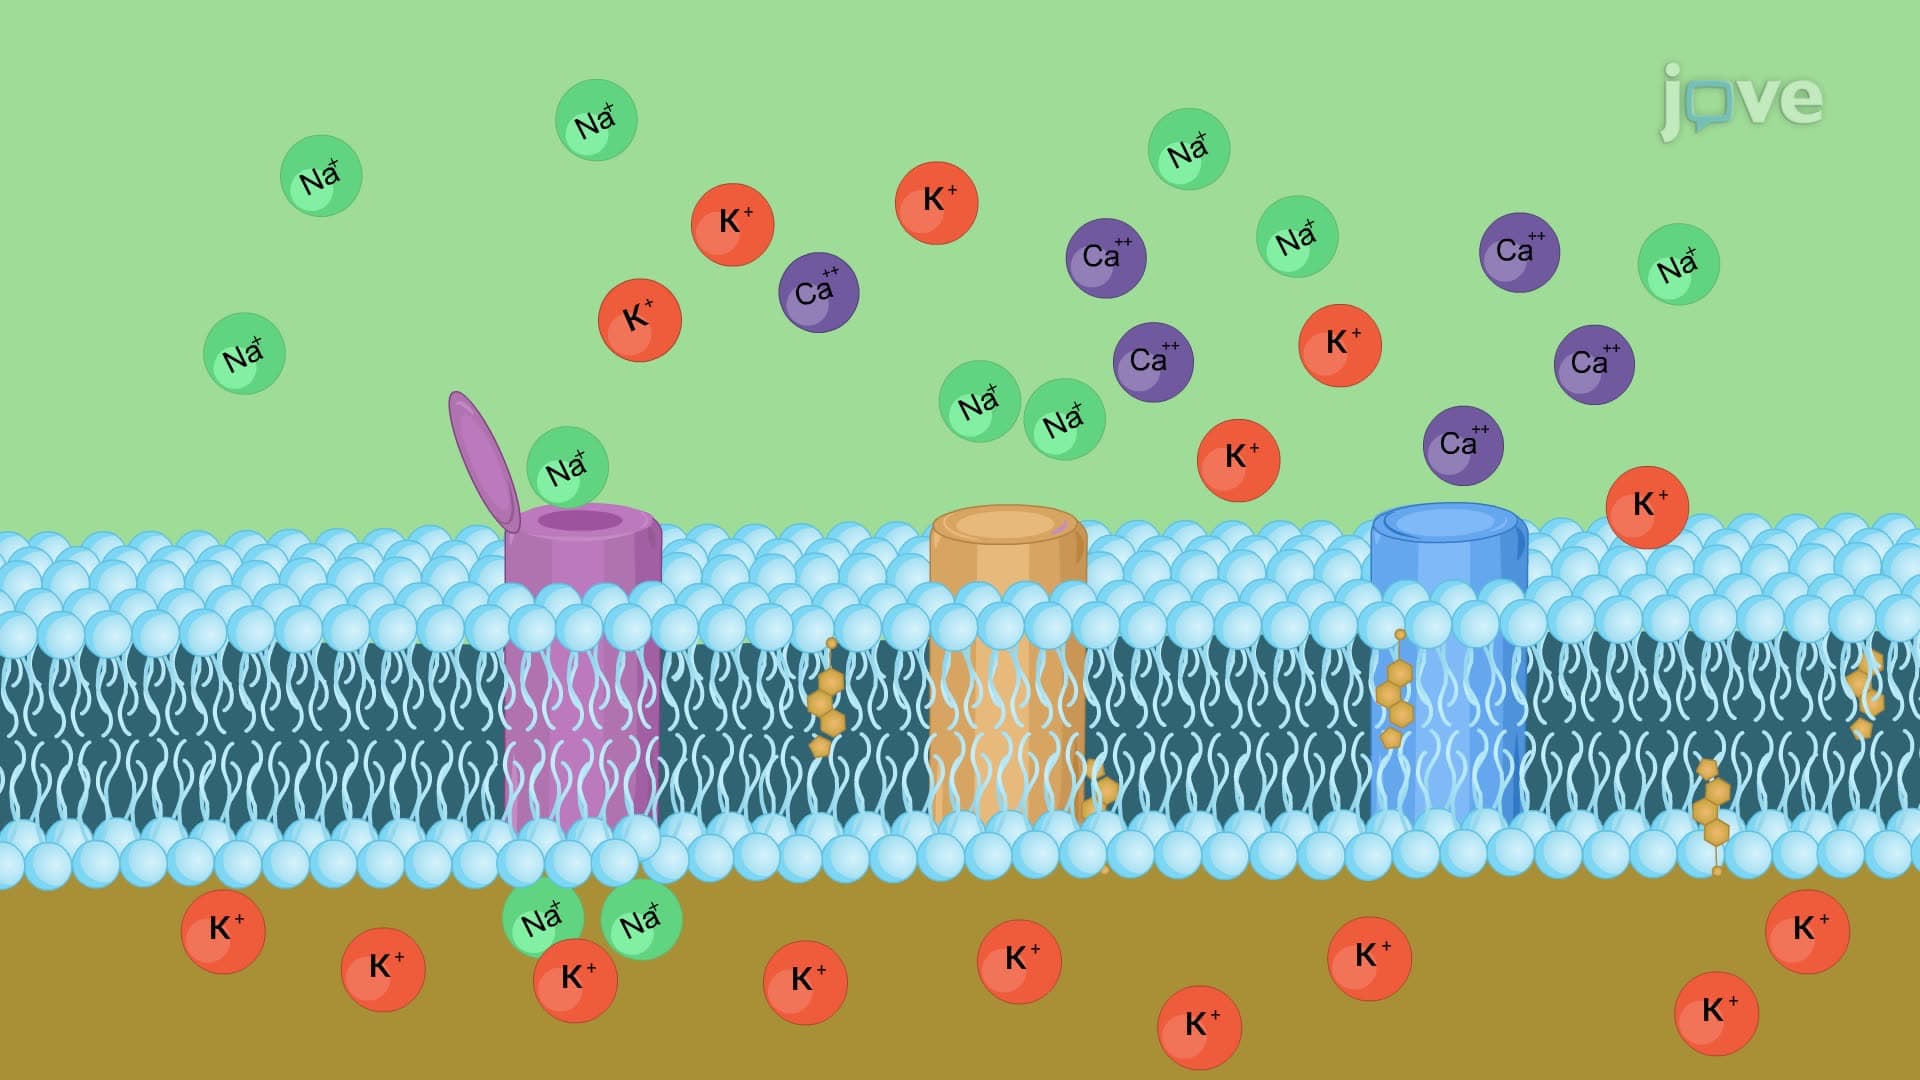
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:14
Myocarditis III: Medical Management
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care