Related Experiment Video
Updated: Sep 28, 2026


Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
Potentially fatal bleeding in acute pancreatitis: pathophysiology, prevention, and treatment
Giancarlo Flati1, Ake Andrén-Sandberg, Massimo La Pinta
1II Department of Surgery, Policlinico Umberto I, University of Rome La Sapienza, Rome, Italy. giancarloflati@hotmail.com

Introduction:
Massive bleeding may complicate the course of either acute or chronic pancreatitis. Although the latter is more frequently involved when bleeding occurs in the acute form, a poorer prognosis is to be expected. Abscess, severe inflammation, regional necrosis, and pseudocysts may cause major vessel erosion, with or without pseudoaneurysm formation, whose eventual rupture may result in massive bleeding into the gastrointestinal tract, retroperitoneum, and peritoneal cavity.
Aims:
To define the most important pathophysiologic mechanisms and factors that might contribute to a better understanding, better prevention, and more efficient treatment of severe hemorrhage complicating acute necrotizing pancreatitis. Awareness of high-risk conditions occurring during the natural evolution of the disease (from extensive local severe enzymatic damage to late septic sequelae), avoidance of a too early and too aggressive approach to sterile pancreatic necrosis, and providing prompt and effective treatment of local septic complications, when they occur, are crucial steps for bleeding prevention.
Methodology:
Forty-four cases of severe bleeding following acute pancreatitis that were reported during the last decade since 1992 (including the six cases reported here) are reviewed, analyzed, and summarized.
Results:
The overall mortality rate was 34.1%. Splenic artery, portal vein, spleen, and unspecified peripancreatic vessels were the most commonly involved sources of bleeding, with associated mortality rates of 33.3%, 50.0%, 30%, and 28.5%, respectively. Massive hemorrhage was more frequently associated with severe necrosis, with a mortality rate of 37.9%.
Conclusion:
The increased use of diagnostic and interventional radiology, in association with prompt surgical treatment, appears to be the way to improve survival rates in cases of arterial bleeding. Venous bleeding due to lesion of major peripancreatic veins or diffuse bleeding represents a therapeutic challenge, and treatment of these conditions should be tailored to the individual case, as no general rule can be suggested. In extreme cases, open packing or salvage emergency pancreatectomy may represent the only chances for survival.

Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
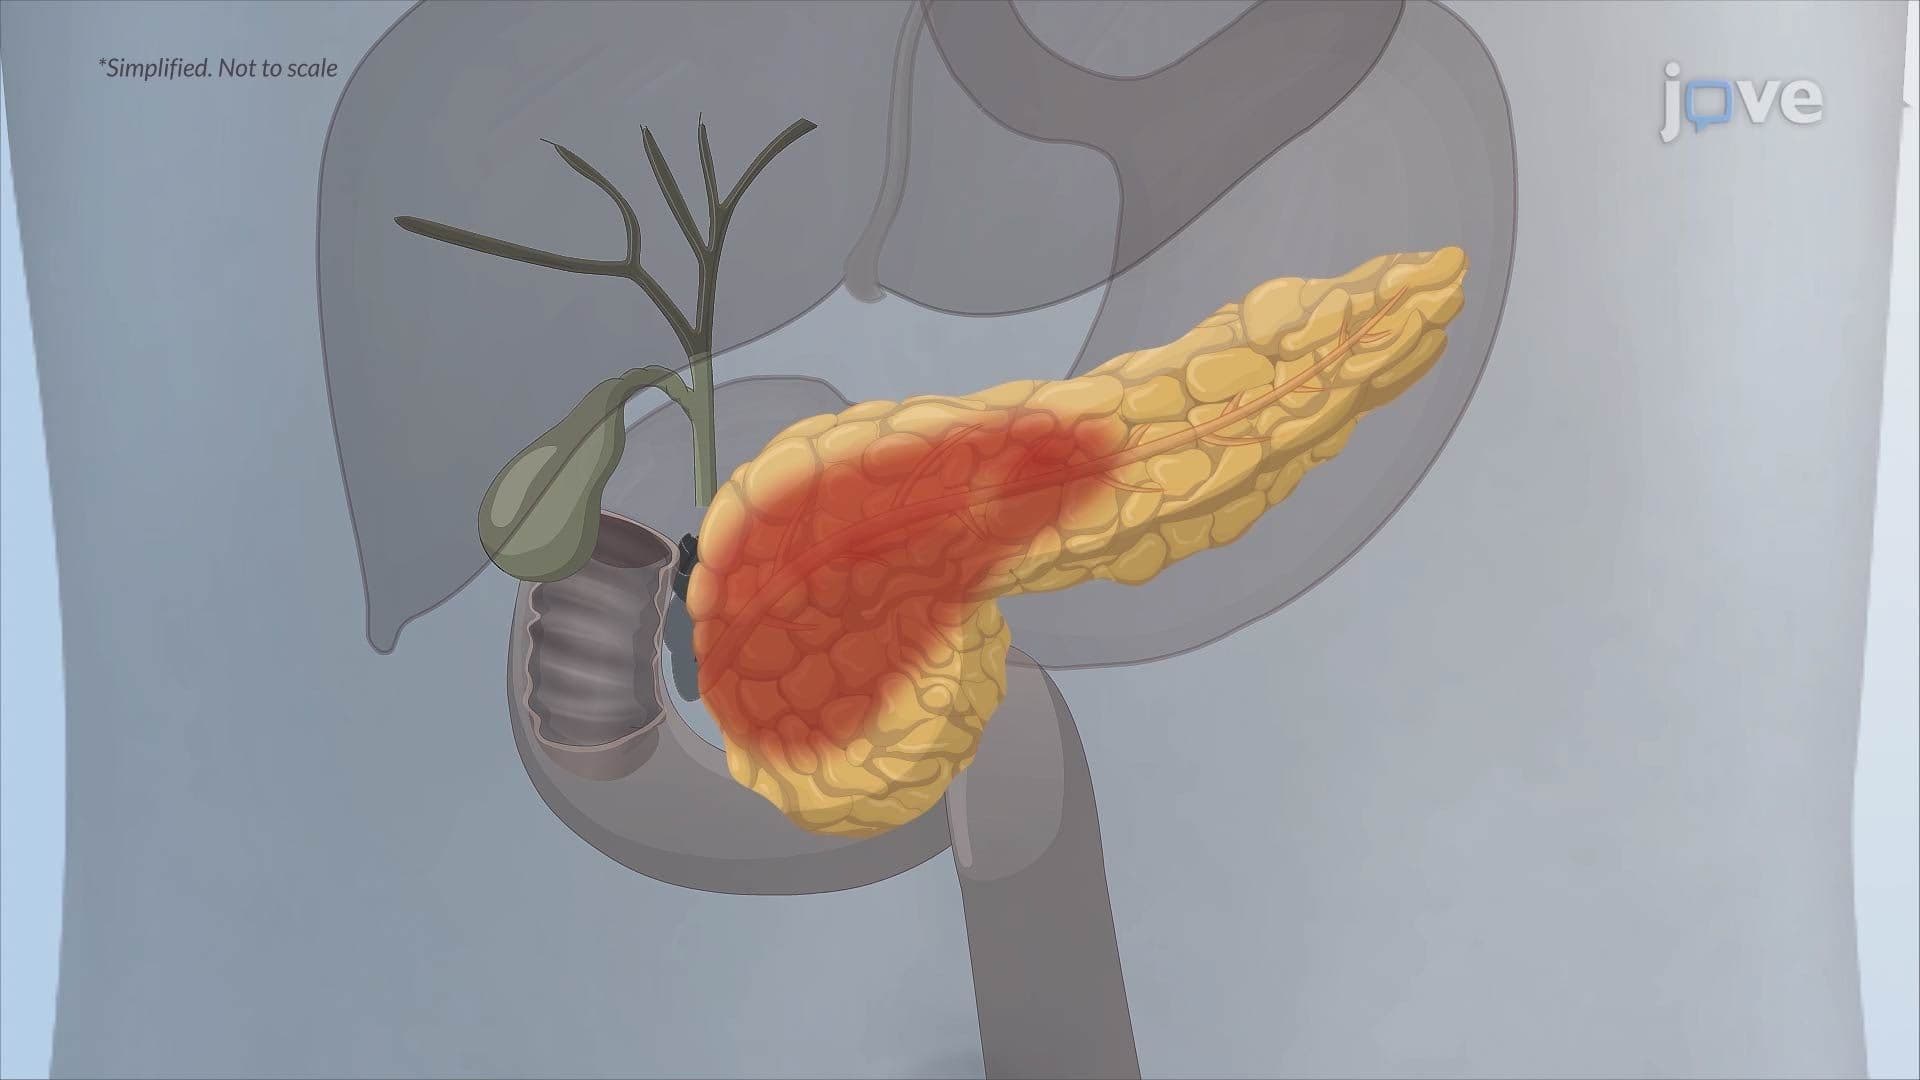
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction