Related Experiment Video
Updated: Sep 28, 2026

Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Whole body oxygen consumption and critical oxygen delivery in response to prolonged and severe carbon monoxide
Howard A Smithline1, Kevin R Ward, Donald A Chiulli
1Baystate Medical Center, Department of Emergency Medicine, Baystate, MA, USA.

Background:
Carbon monoxide (CO) poisoning remains the leading cause of death by poisoning in the world. One of the major proposed mechanisms for CO toxicity is the binding of CO to cytochrome oxidase and interference with cellular oxygen utilization but evidence for this is inconclusive.
Aim Of Study:
This study examined the effects of prolonged CO exposure on the dynamics of whole body oxygen consumption (VO(2)) and oxygen delivery (DO(2)) in an attempt to observe if CO exposure results in a defect of oxygen utilization defect as determined by a reduction in VO(2) during the course of poisoning prior to reaching the point where VO(2) is directly dependent on DO(2). This critical level of DO(2) (DO(2)crit) produced by CO poisoning was compared to historical values produced by other insults, which decrease global body DO(2).
Methods:
Five small dogs were ventilated for 2 h with 0.25% CO and room air followed by 0.5% CO until death. Cardiac index (Q), DO(2), VO(2), oxygen extraction ratio (OER), and systemic lactate were measured every 15 min until death.
Results:
Carboxyhemoglobin (COHb) levels increased linearly over 2.5 h to values above 80% until death. VO(2) remained constant and not significantly different from baseline below a COHb of 80%. At COHb levels above 80%, VO(2) precipitously dropped. Similarly lactate levels were not significantly elevated from baseline until VO(2) dropped. DO(2) decreased by 78% (from 23+/-6 ml/kg/min to 5+/-4 ml/kg/min) over time despite an increase in Q by 58% until levels of COHb were above 80%. OER increased from 19+/-5% to 50+/-11% until death. The calculated DO(2)crit was 10.7+/-4 ml/min/kg, which is not significantly different from values ranging from 7 to 13 ml/min/kg reported in the literature due to other insults, which reduce DO(2).
Conclusion:
In this canine model of prolonged CO exposure, no gradual reduction in VO(2) or increase in systemic lactate prior to reaching DO(2)crit was noted. In addition, CO exposure does not appear to change the DO(2)crit. The combination of these findings does not support the theory that CO produces a whole body intracellular defect in oxygen utilization.
Related Concept Videos
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:27
Oxygen Transport in the Blood
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:20
Respiration and Gaseous Exchange
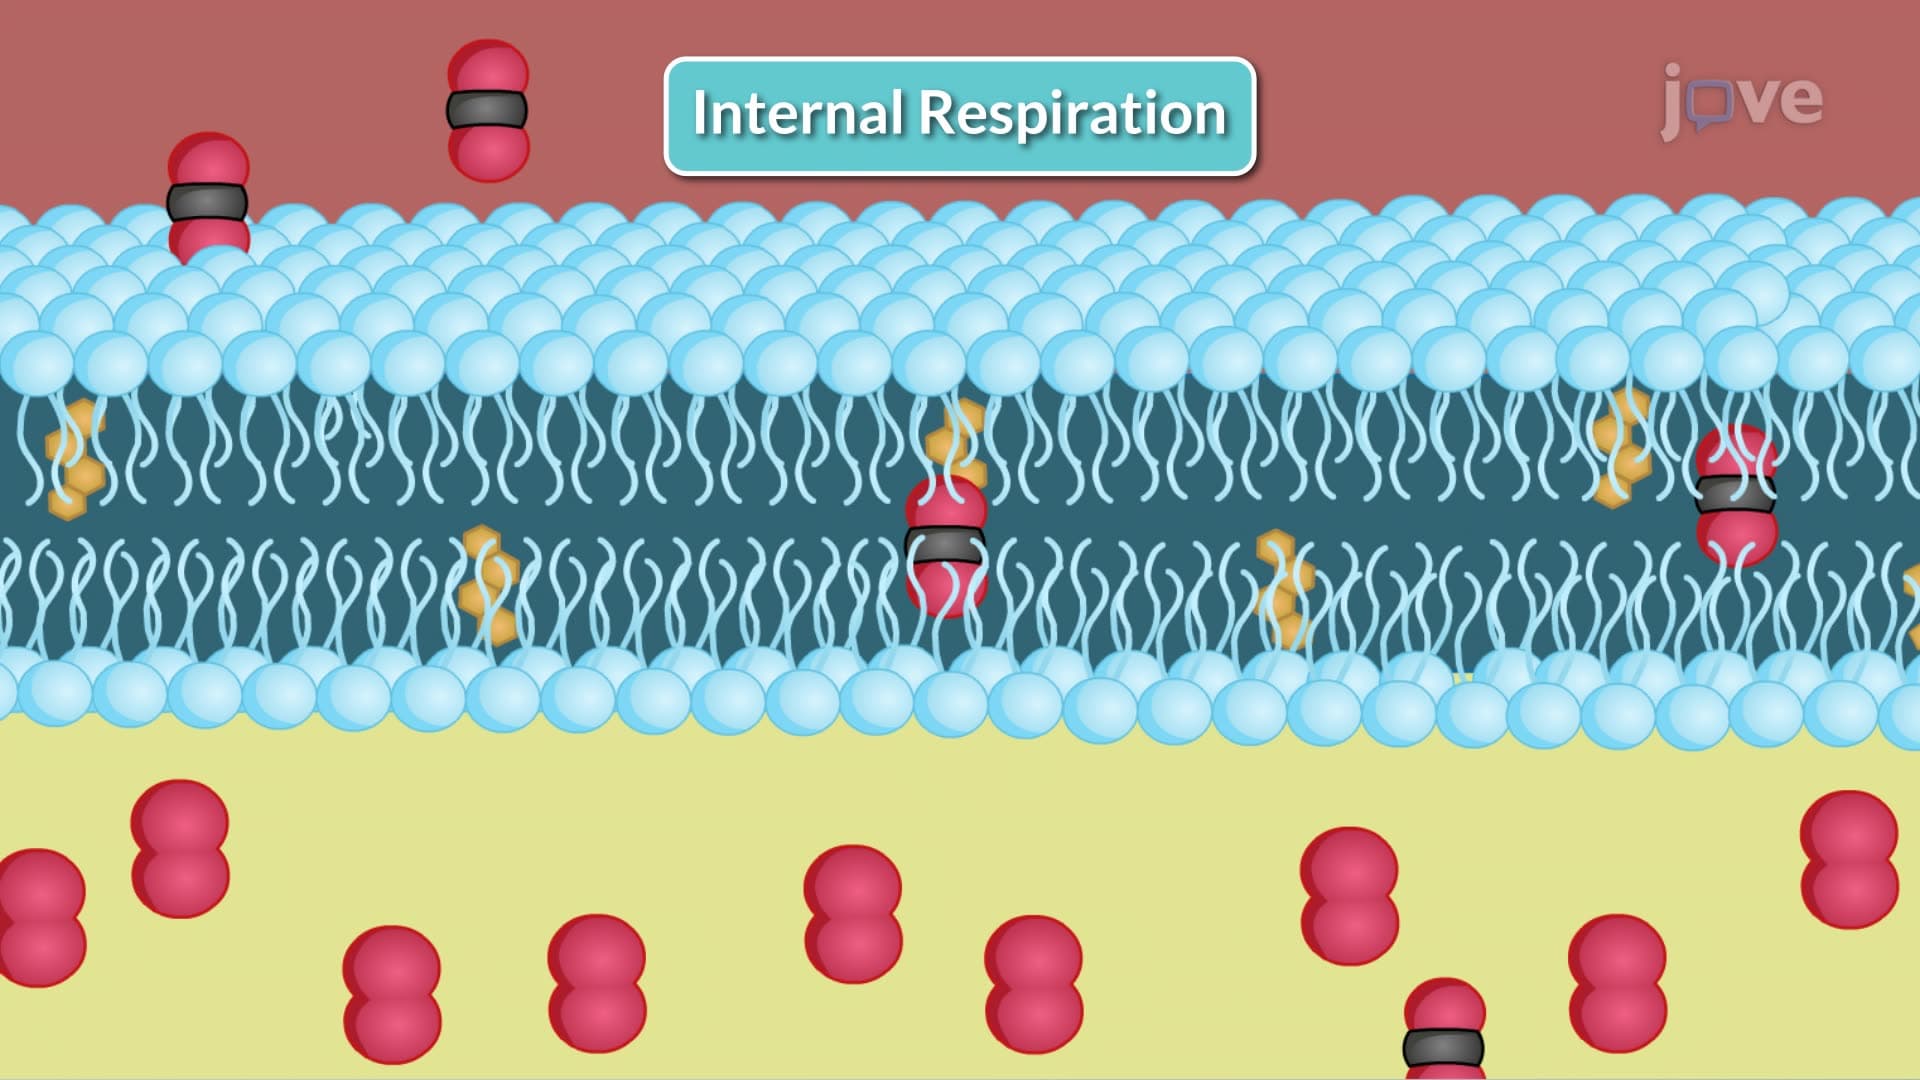
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...