Related Experiment Video
Updated: Sep 27, 2026

A Retrograde Implantation Approach for Peritoneal Dialysis Catheter Placement in Mice
Published on: July 20, 2022
Dialysis for everybody? At any cost?
1Nephrology, Dialysis and Renal Transplant Unit, Niguarda Ca' Granda Hospital, Milano, Italy. ehbpgr@tin.it

Abstract:
During the last fifty years medicine has made enormous progress. However the "mechanical disease model" has introduced the concept of disease as a biological disorder and, at the same time, has shifted the objective of the doctor's action: the patient is identified with the disease and the latter being curable, there are no limits to the doctor's action. This behaviour has two different implications: one is referred to the tremendous increase of the expenditure and the second is related to the changes in death's physiognomy. Today death is no longer a moment, but a process whose practical outcome is the dilution (from hours to months) of the boundary between life and death. Equity is one of the main principles of every health systems: all the members of a community should have equal opportunities to receive medical treatment. Every year approximately 1250 million Euros (2% of the total health expenditure) are spent in Italy for nearly 41,000 patients on chronic dialysis. In terms of macro economy and of balanced health policy, no ethical principles can justify the absorption of such a huge quantity of resources by such a small number of patients. We must establish some rules, but it is obvious that such rules cannot be based on the identification of criteria that exclude patient groups based on statistical parameters, and on the sum of risk factors. Viceversa, the exclusion and/or withdrawal from RRT must depend on the possibilities of individual patients to maintain the essential characteristics of human beings or on the patient's opinion that there is a lack of proportion between means and results. Doctors cannot presume that the best solution coincides with the extension of patients' life. Their assistance must not aim at mere survival neglecting the quality of life. In order to start an in depth discussion, solid ethical and methodological references can be found in the "Clinical Practice Guidelines on Shared Decision-Making in the Appropriate Initiation of and Withdrawal from Dialysis". This topic can no longer be postponed. Should the nephrological community be unable to find a shared basis for discussion beyond hypocrisy, the valuable doctor-patient relationship (which is vital for all medical procedures) will be replaced by the "taxpayer-mediated" approach. In this case, following the principles of social good, the political community will compel doctors to mediate a conflict between collective interests and individual interests, and doctors will no longer be able to act in compliance with the ethical principles of "avoiding harm".
Related Concept Videos
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:25
Hemodialysis I: Introduction
 01:30
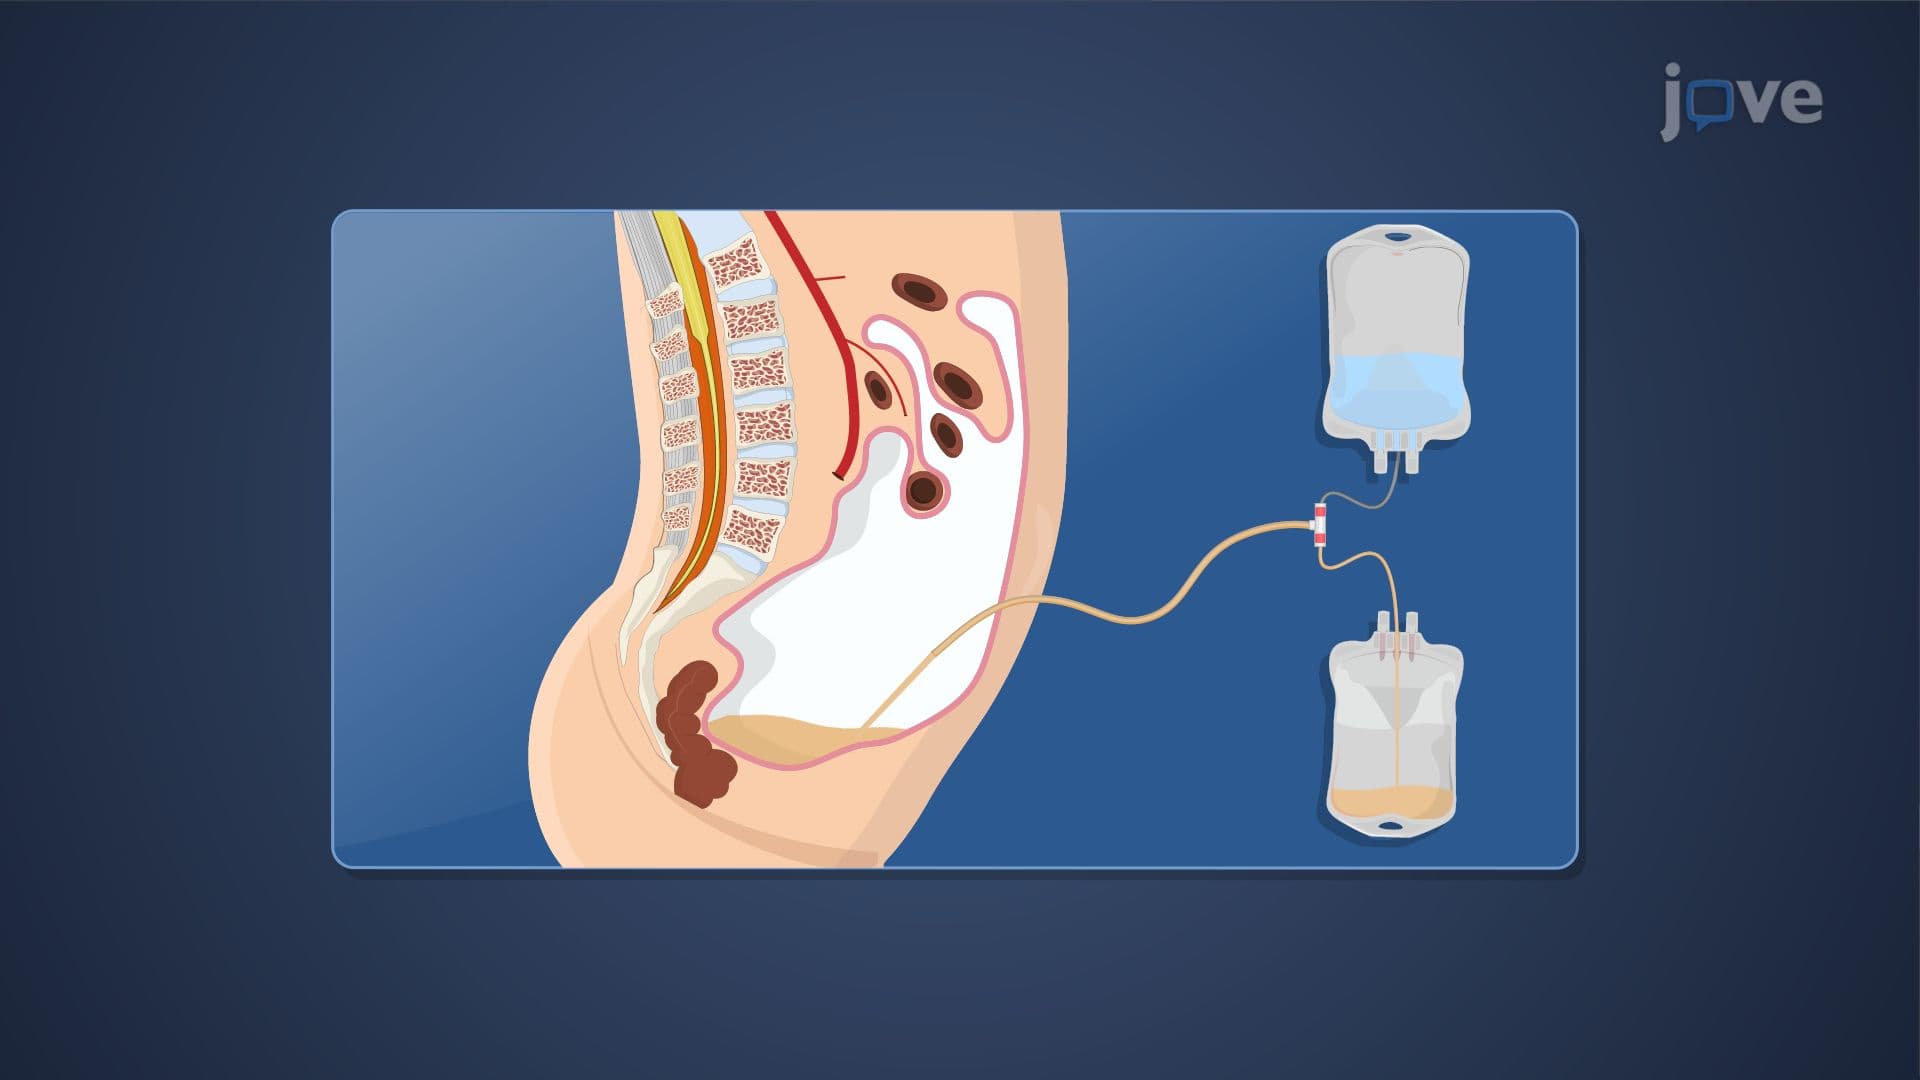
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:24
Hemodialysis II: Procedure and Complications
 01:20
Acute Kidney Injury V: Interprofessional Care