Related Experiment Video
Updated: Sep 27, 2026
Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
Effects of common polymorphisms in the alpha1A-, alpha2B-, beta1- and beta2-adrenoreceptors on haemodynamic responses
Amir Snapir1, Juha Koskenvuo, Jyri Toikka
1Department of Pharmacology and Clinical Pharmacology, University of Turku, Itäinen Pitkäkatu 4, Finland. snapir@utu.fi

Abstract:
Common naturally occurring polymorphisms have been identified in the coding regions of the alpha(1A)-, alpha(2B)-, beta(1)- and beta(2)-adrenoceptor (AR) genes [alpha(1A)-AR R492C, alpha(2B)-AR insertion/deletion (I/D), beta(1)-AR R389G, beta(2)-AR G16R and beta(2)-AR Q27E] and are associated with modified in vivo and in vitro functionality. We tested their possible effects on the haemodynamic responses to intravenous adrenaline (20, 40, 80 and 160 ng/kg of body weight per min; 5 min for each infusion rate) before and after beta-blockade (propranolol) in 16 young healthy men. We monitored changes in heart rate, blood pressure (BP), ECG, coronary flow velocity and plasma adrenaline and noradrenaline. The Cys/Cys (CC) genotype of the alpha(1A)-AR R492C polymorphism was associated with a longer ECG PR interval before and during the adrenaline infusions. The deletion/deletion (D/D) genotype of the alpha(2B)-AR I/D polymorphism was associated with blunted coronary blood flow increases during the adrenaline infusion before beta-blockade. The beta(1)-AR R389G polymorphism was not associated with modified responses to infused adrenaline. Subjects carrying the Gly/Gly (GG) genotype of the beta(2)-AR G16R polymorphism demonstrated increases in diastolic BP upon adrenaline infusion, whereas diastolic BP was decreased in the other genotype groups. These results suggest that, upon acute adrenaline infusion, the alpha(2B)-AR D/D genotype confers increased vasoconstriction and that the beta(2)-AR GG genotype confers reduced vasodilatation.

Related Concept Videos
 01:26
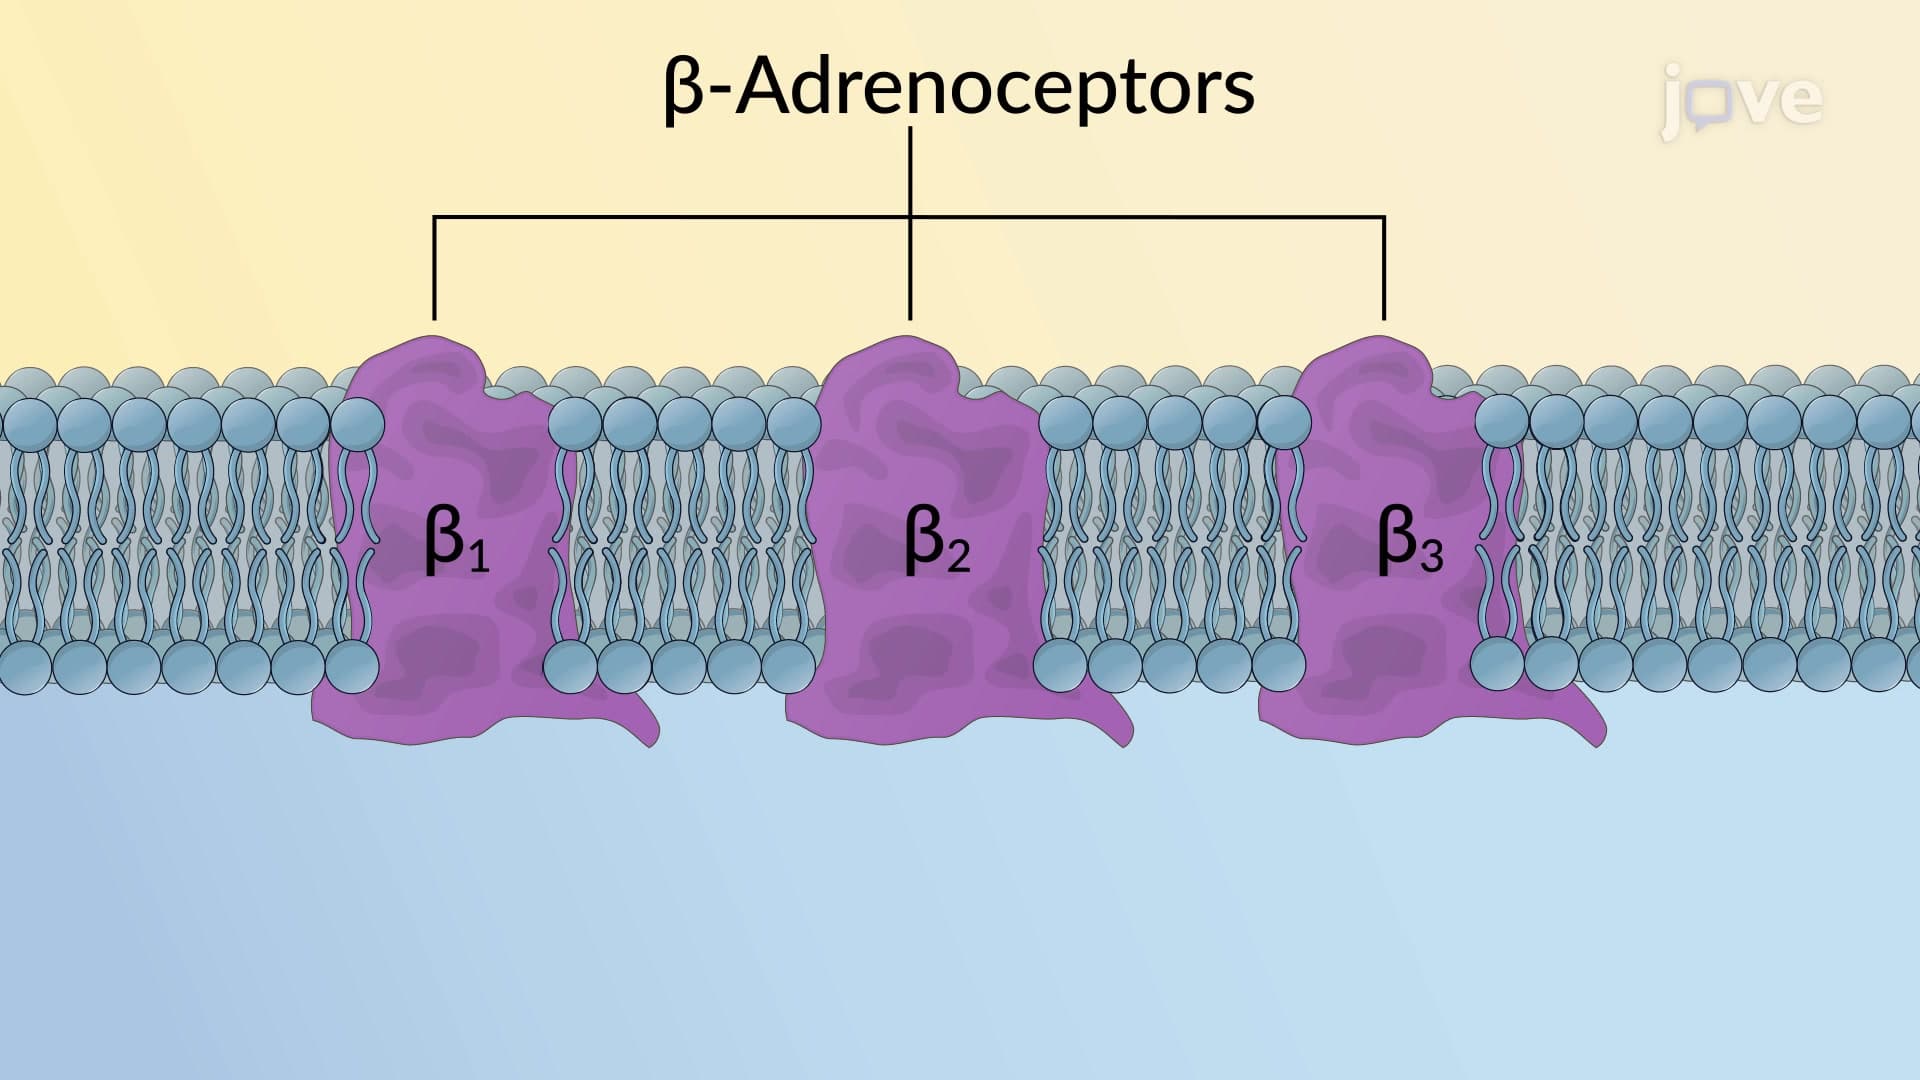
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:27
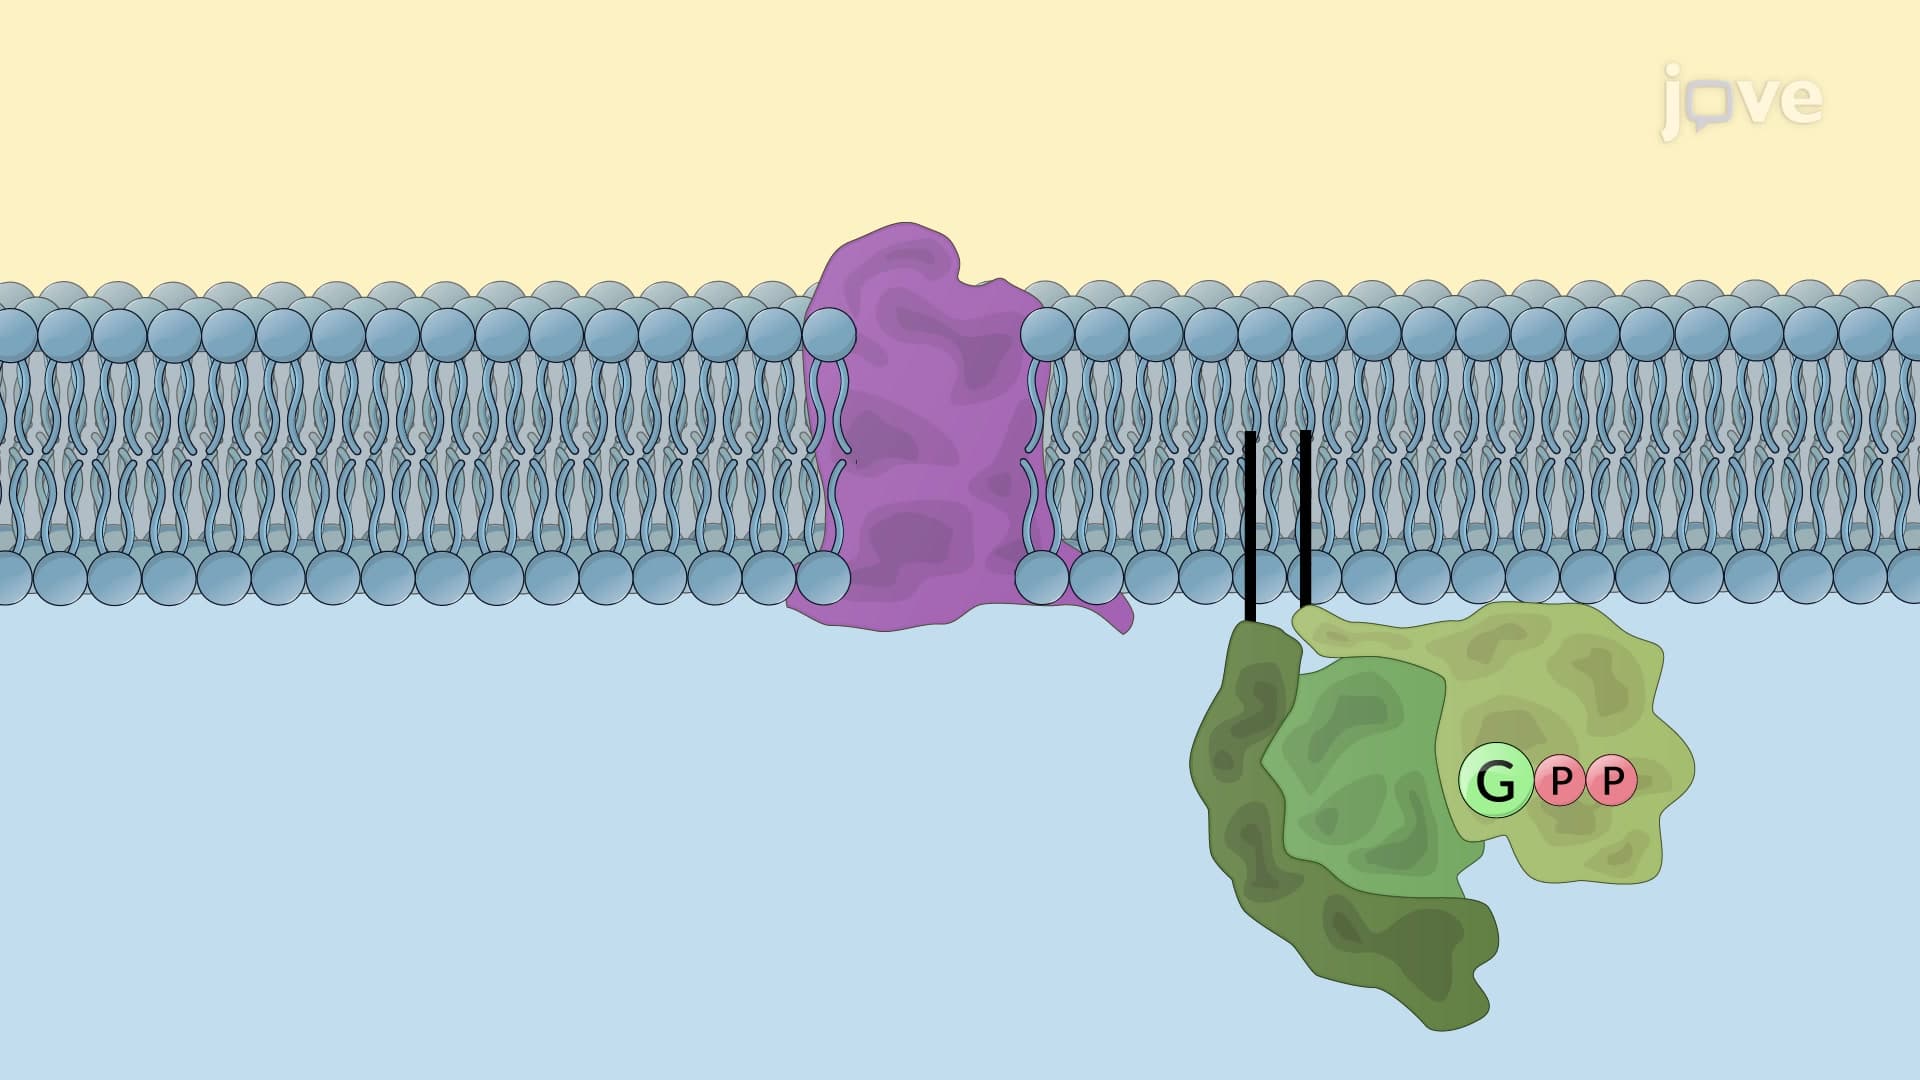
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
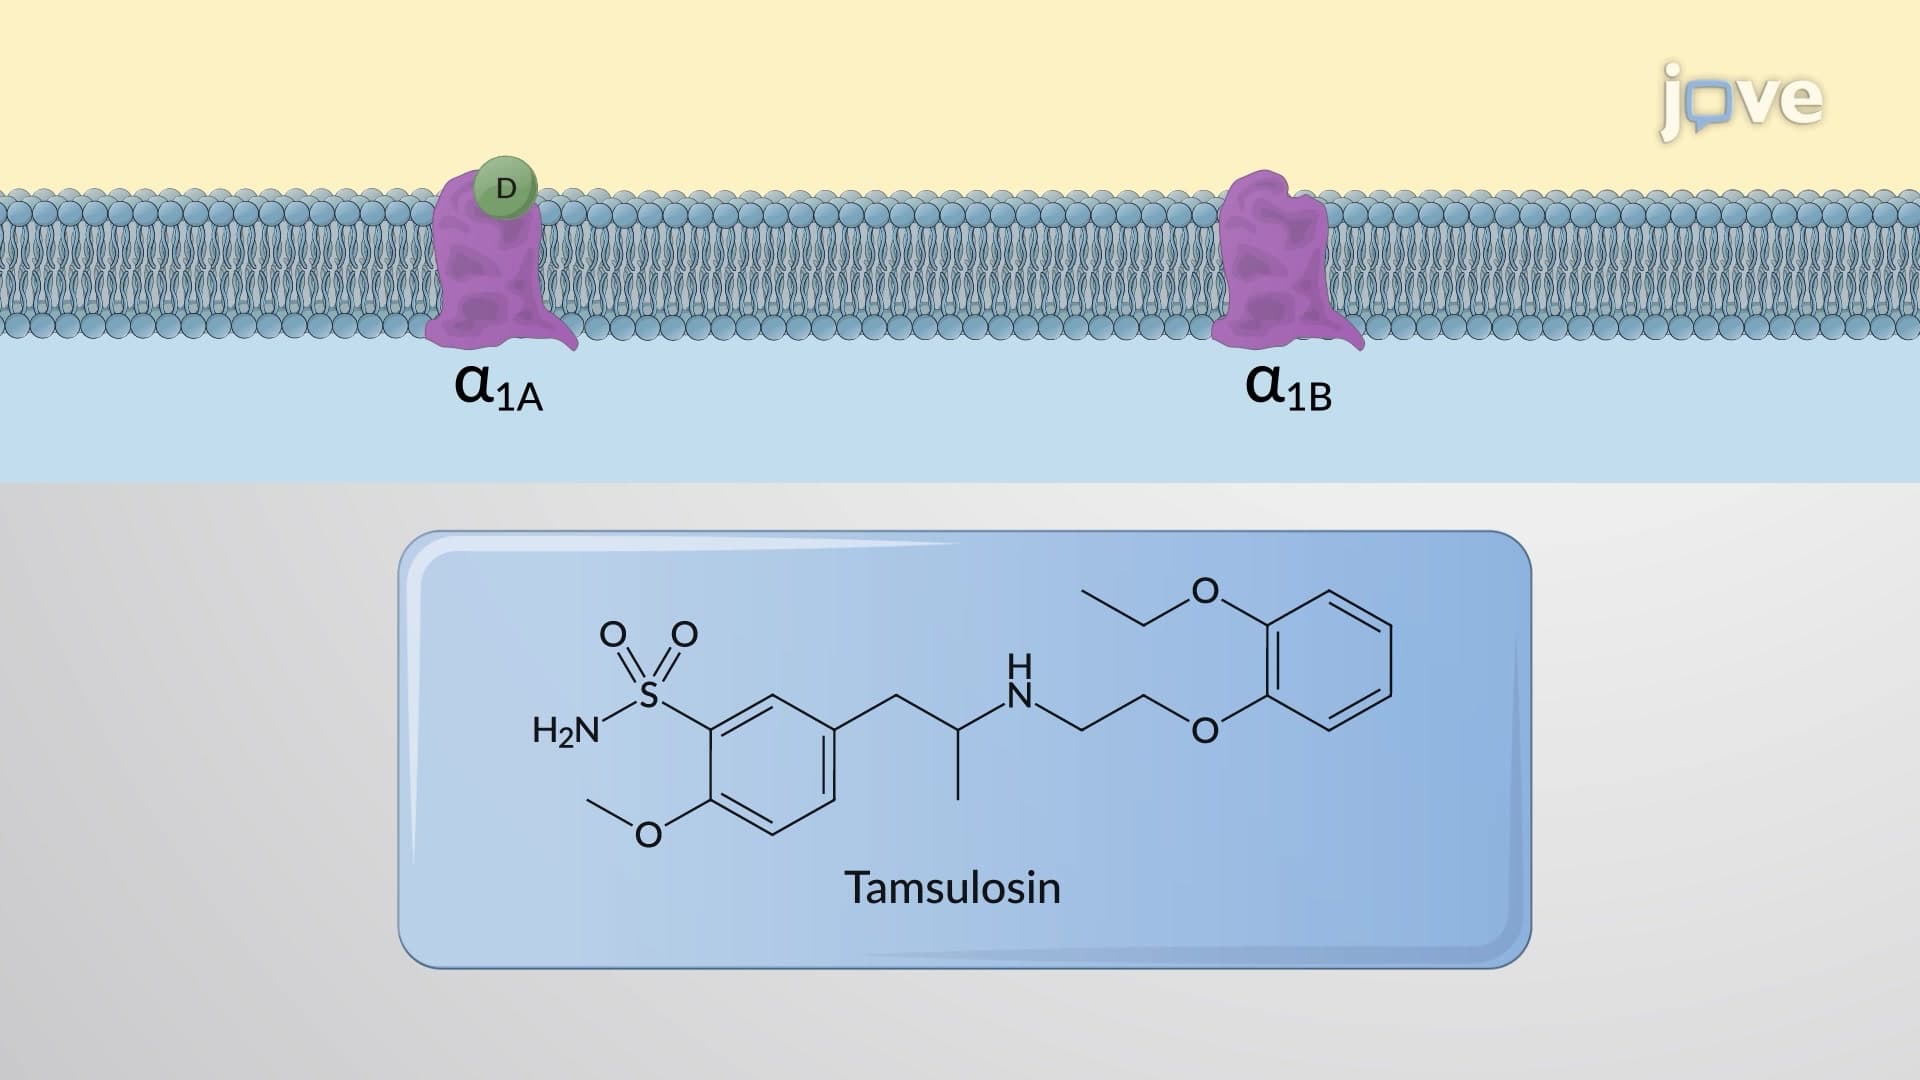
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:22
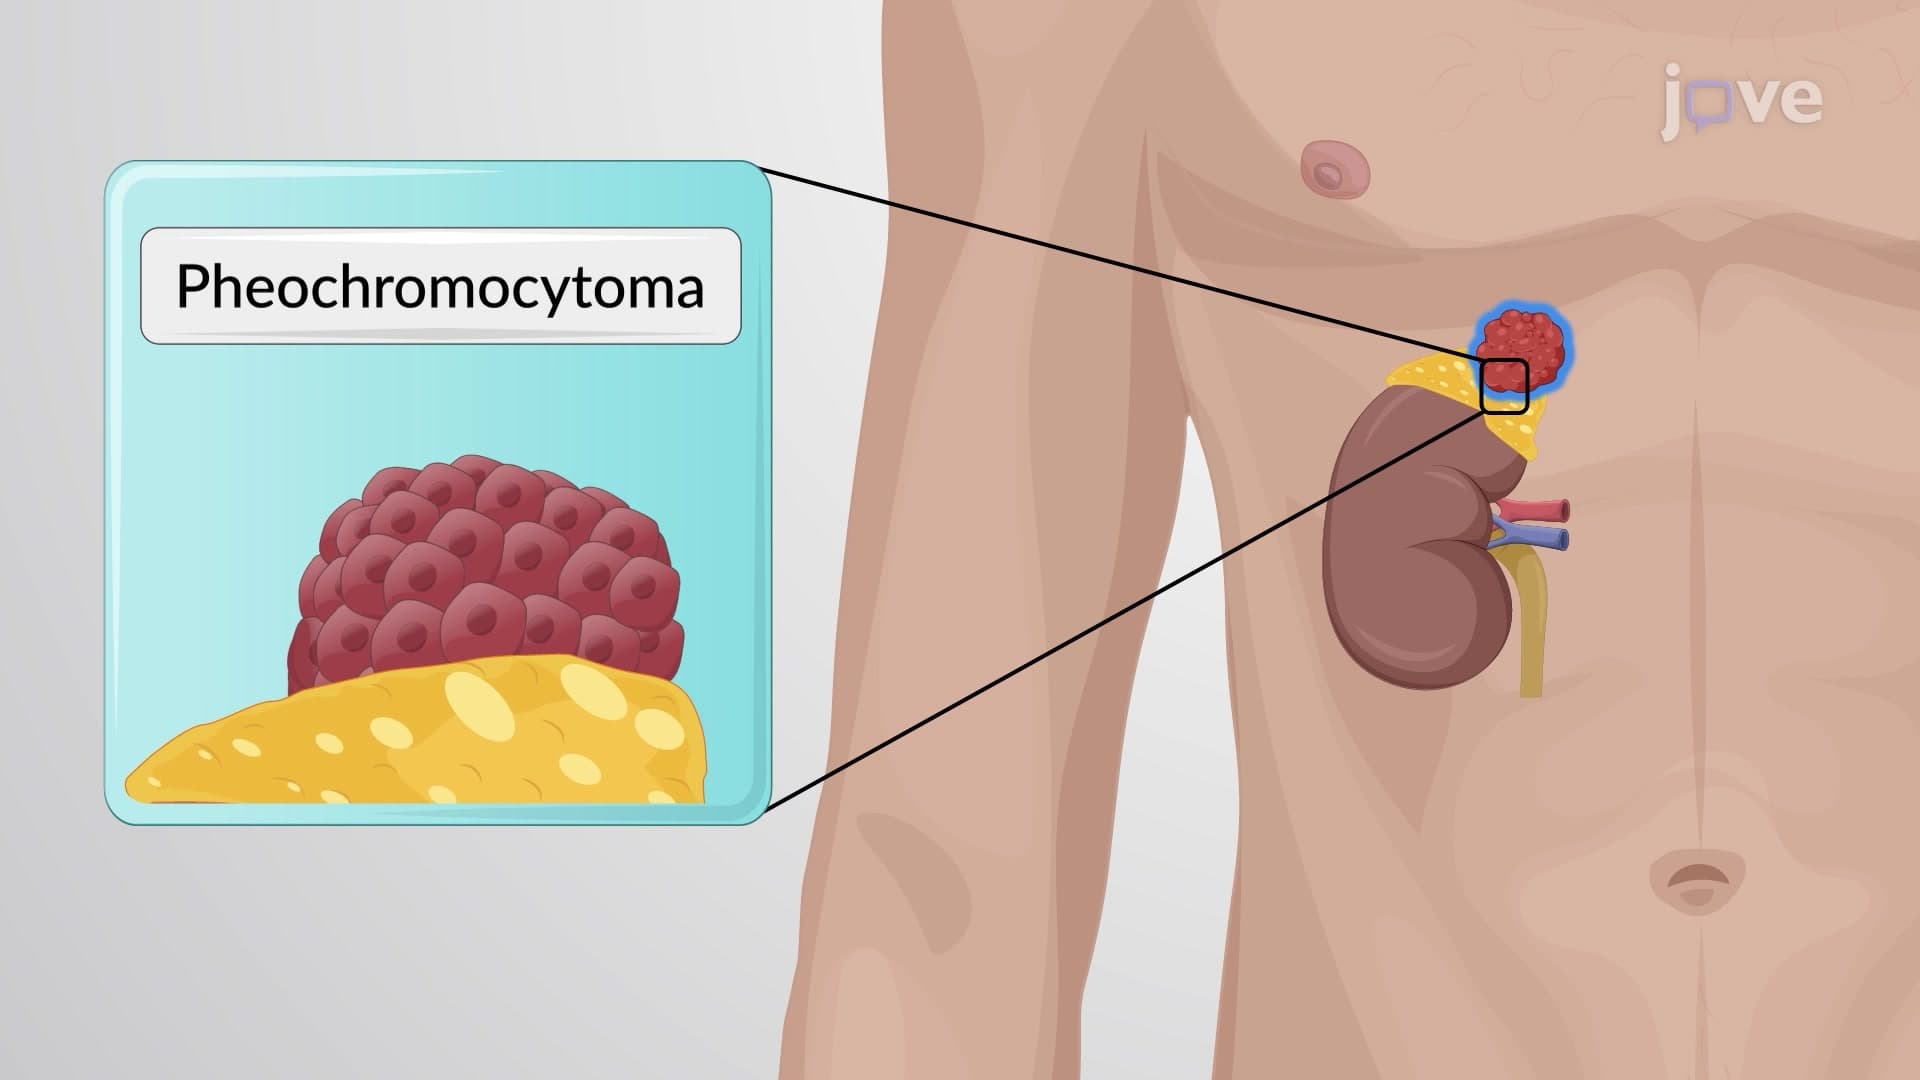
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...