Related Experiment Video
Updated: Aug 12, 2026


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse (POP) Quantification System
Published on: September 20, 2018
Study of the levator ani muscle in the multipara: role of levator dysfunction in defecation disorders
1Department of Surgery and Experimental Research, Faculty of Medicine, Cairo University, 2 Talaat Harb Street, Cairo, Egypt. ashafik@ahmedshafik.org

Abstract:
The levator ani muscle (LAM) shares in the mechanism of defecation and urination as well as in visceral support. Levator dysfunction occurs in conditions of chronic straining or increased intra-abdominal pressure. Studies have shown that the gravid uterus, by virtue of its weight and associated increased intraabdominal pressure, might disturb the levator function. It is postulated that this effect is augmented with repeated pregnancies. The current study investigated the functional activity of the LAM in 50 multipara, 30 primipara and 20 nullipara (controls). The 50 multipara (age 46.4 years, 4-7 deliveries) were divided into group A (28 women with normal deliveries) and group B (22 women with a prolonged 2nd stage of labour). Of the 30 primipara (age 44.2 years) 18 had normal delivery (group A) and 12 prolonged 2nd stage of labour (group B). The mean age of the nullipara was 45.3+/-7.6. The LAM activity at rest and on contraction was recorded. The rectal and anal canal pressure response to LAM stimulation was also registered. In group A of the multipara, the LAM EMG activity at rest was similar to (P>0.05), and on contraction lower (P<0.05) than the LAM EMG of the controls (nullipara). Group B exhibited a lower activity at rest and on contraction (P<0.01, both). Primipara group A had a resting and contractile EMG activity similar to the controls, while group B showed diminished activity in both conditions (P<0.05, both) which was significantly higher (P<0.05, P<0.01, respectively) than that of group B multipara. The rectal pressure in the multipara and primipara did not differ from the nullipara (P>0.05, both). In groups A and B of multiparous women, the anal canal pressure at rest was significantly lower and on LAM contraction significantly higher than that of nullipara. Group A of the primipara showed no significant difference against the controls, while group B exhibited a decline at rest (P<0.05) and no difference on LAM contraction (P>0.05). In conclusion, levator dysfunction might occur in the parous women. It was more common in the multipara than the primipara and in particular those with a history of a prolonged 2nd stage of labour. Levator dysfunction may lead to constipation and faecal or urinary incontinence as a result of pudendal neuropathy and the development of pudendal canal syndrome.

Related Concept Videos
 01:26
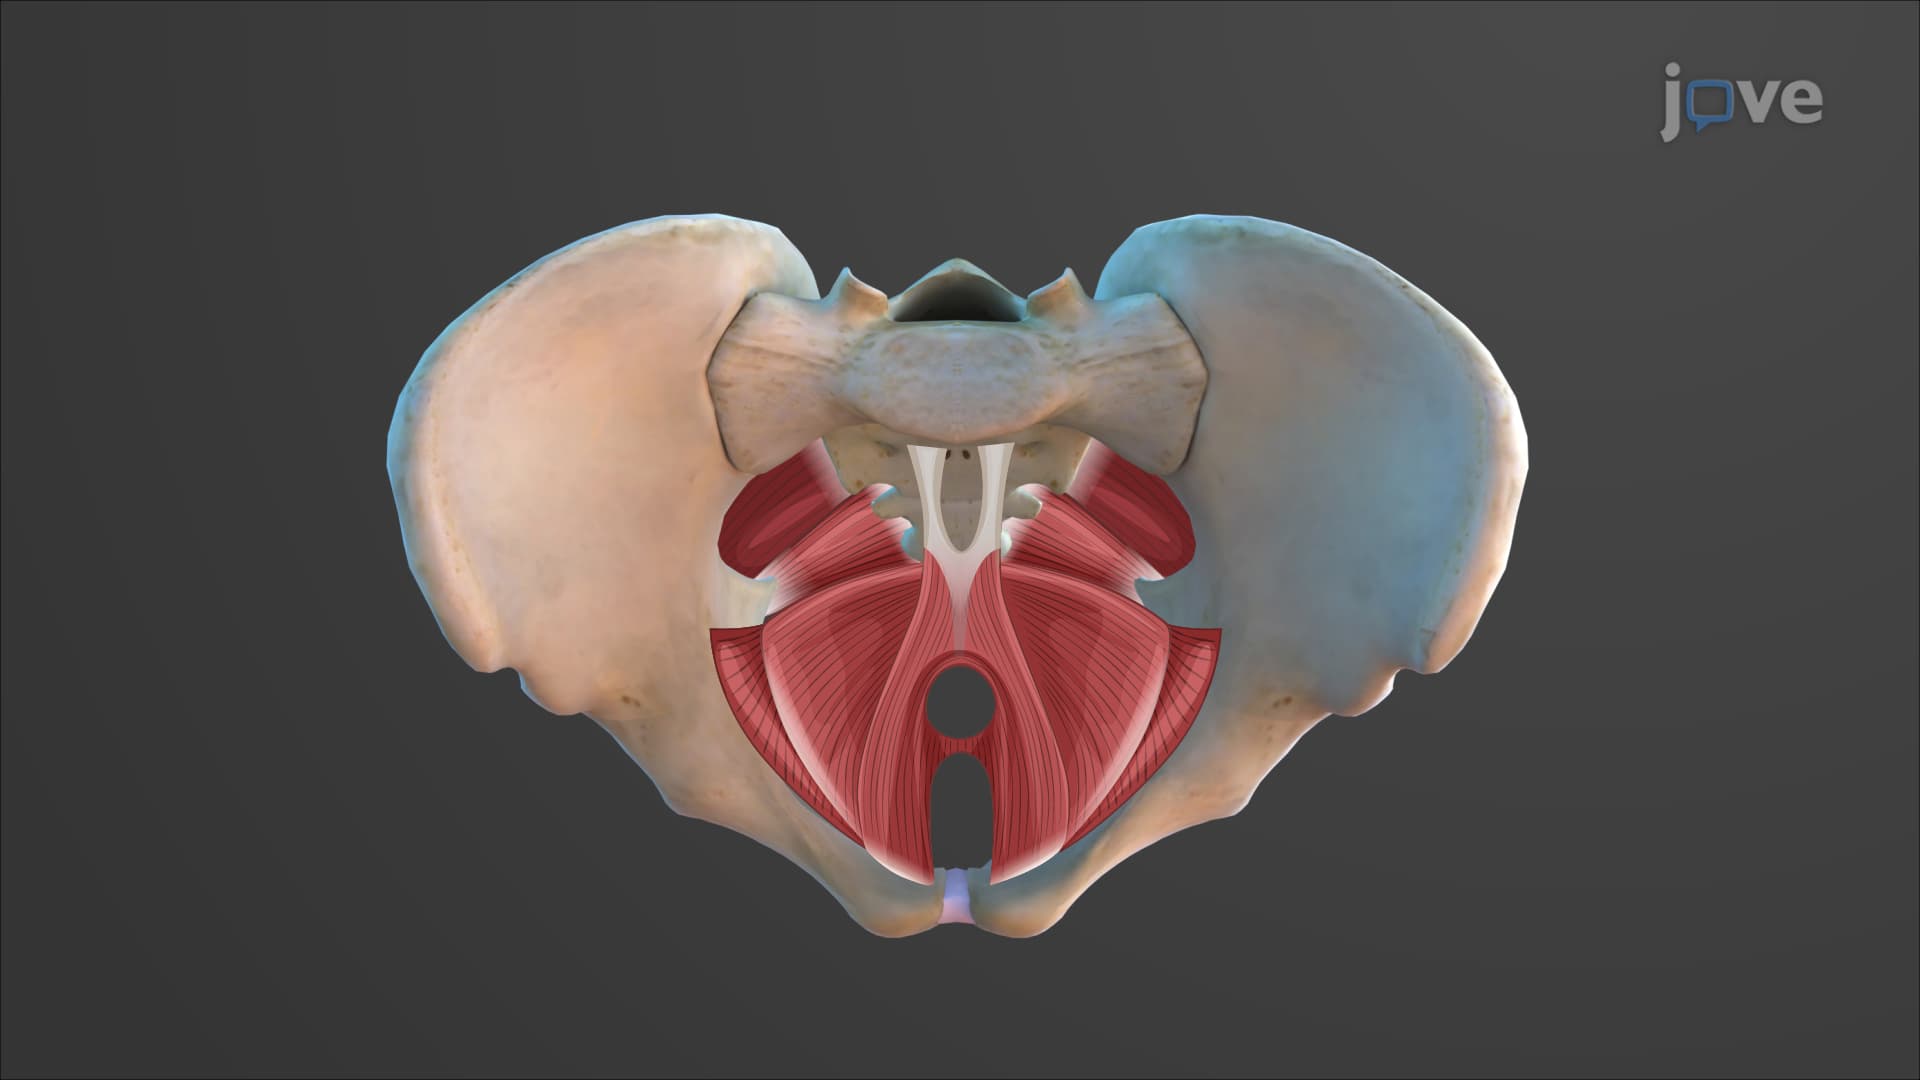
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:22
Drugs Affecting GI Tract Motility: Bulk-Forming and Stimulant Laxatives
Bulk-forming laxatives, such as psyllium, methylcellulose, and polycarbophil, absorb water in the intestine, increasing stool bulk and promoting bowel movement. This makes...
 01:26
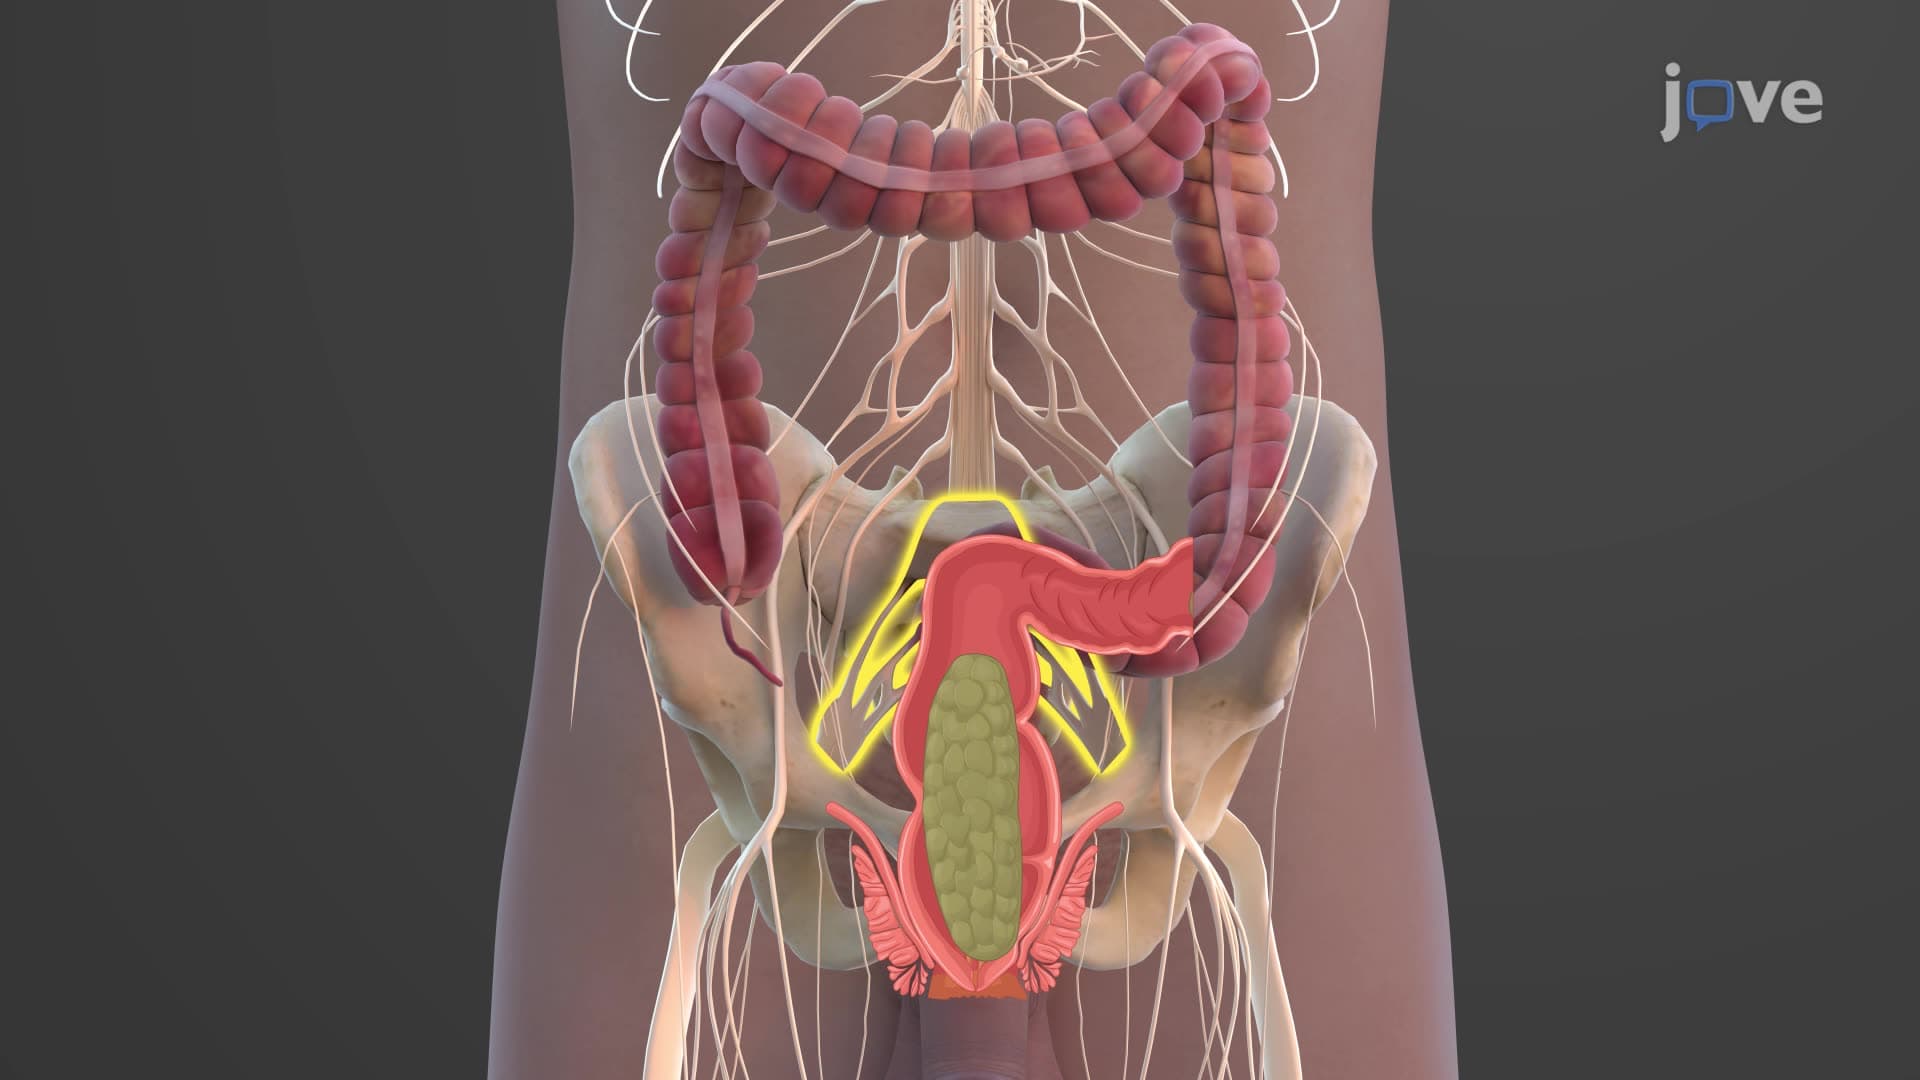
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:26
Physiology of the Gastrointestinal System III: Elimination
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:27
Diverticular Disease of the Colon