Related Experiment Video
Updated: Aug 10, 2026

Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Preliminary experience with the use of insulin lispro in pregnant diabetic women
T O Idama1, S W Lindow, M French
1Department of Obstetrics and Gynaecology, Royal Hull Hospital, UK.

Insulin lispro (IL) possesses characteristics (decreased hypoglycaemia, greater convenience in timing of administration and better post-prandial glucose control) which may favour its use in women with diabetes. We report pregnancy outcomes in seven women with Type I diabetes treated with IL. Mean age was 30 years (2241), duration of diabetes from 3 to 21 years. Two were using IL pre-conception; others transferred at various stages of pregnancy. Mean daily dose of IL within the last month of pregnancy ranged from 0.59 to 1.13 U/kg. Mean HbA1C from 4.4 to 8.5%. Babies were delivered at 3438 weeks' gestation, birth weights from 2900 to 4125 g (mean 3434 g). There were no congenital abnormalities. All patients elected to continue with IL after pregnancy. Our experience suggests that IL is convenient and practical therapy for women with Type I diabetes in pregnancy.
Insulin lispro (IL) possesses characteristics (decreased hypoglycaemia, greater convenience in timing of administration and better post-prandial glucose control) which may favour its use in women with diabetes. We report pregnancy outcomes in seven women with Type I diabetes treated with IL. Mean age was 30 years (2241), duration of diabetes from 3 to 21 years. Two were using IL pre-conception; others transferred at various stages of pregnancy. Mean daily dose of IL within the last month of pregnancy ranged from 0.59 to 1.13 U/kg. Mean HbA1C from 4.4 to 8.5%. Babies were delivered at 3438 weeks' gestation, birth weights from 2900 to 4125 g (mean 3434 g). There were no congenital abnormalities. All patients elected to continue with IL after pregnancy. Our experience suggests that IL is convenient and practical therapy for women with Type I diabetes in pregnancy.
Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:25
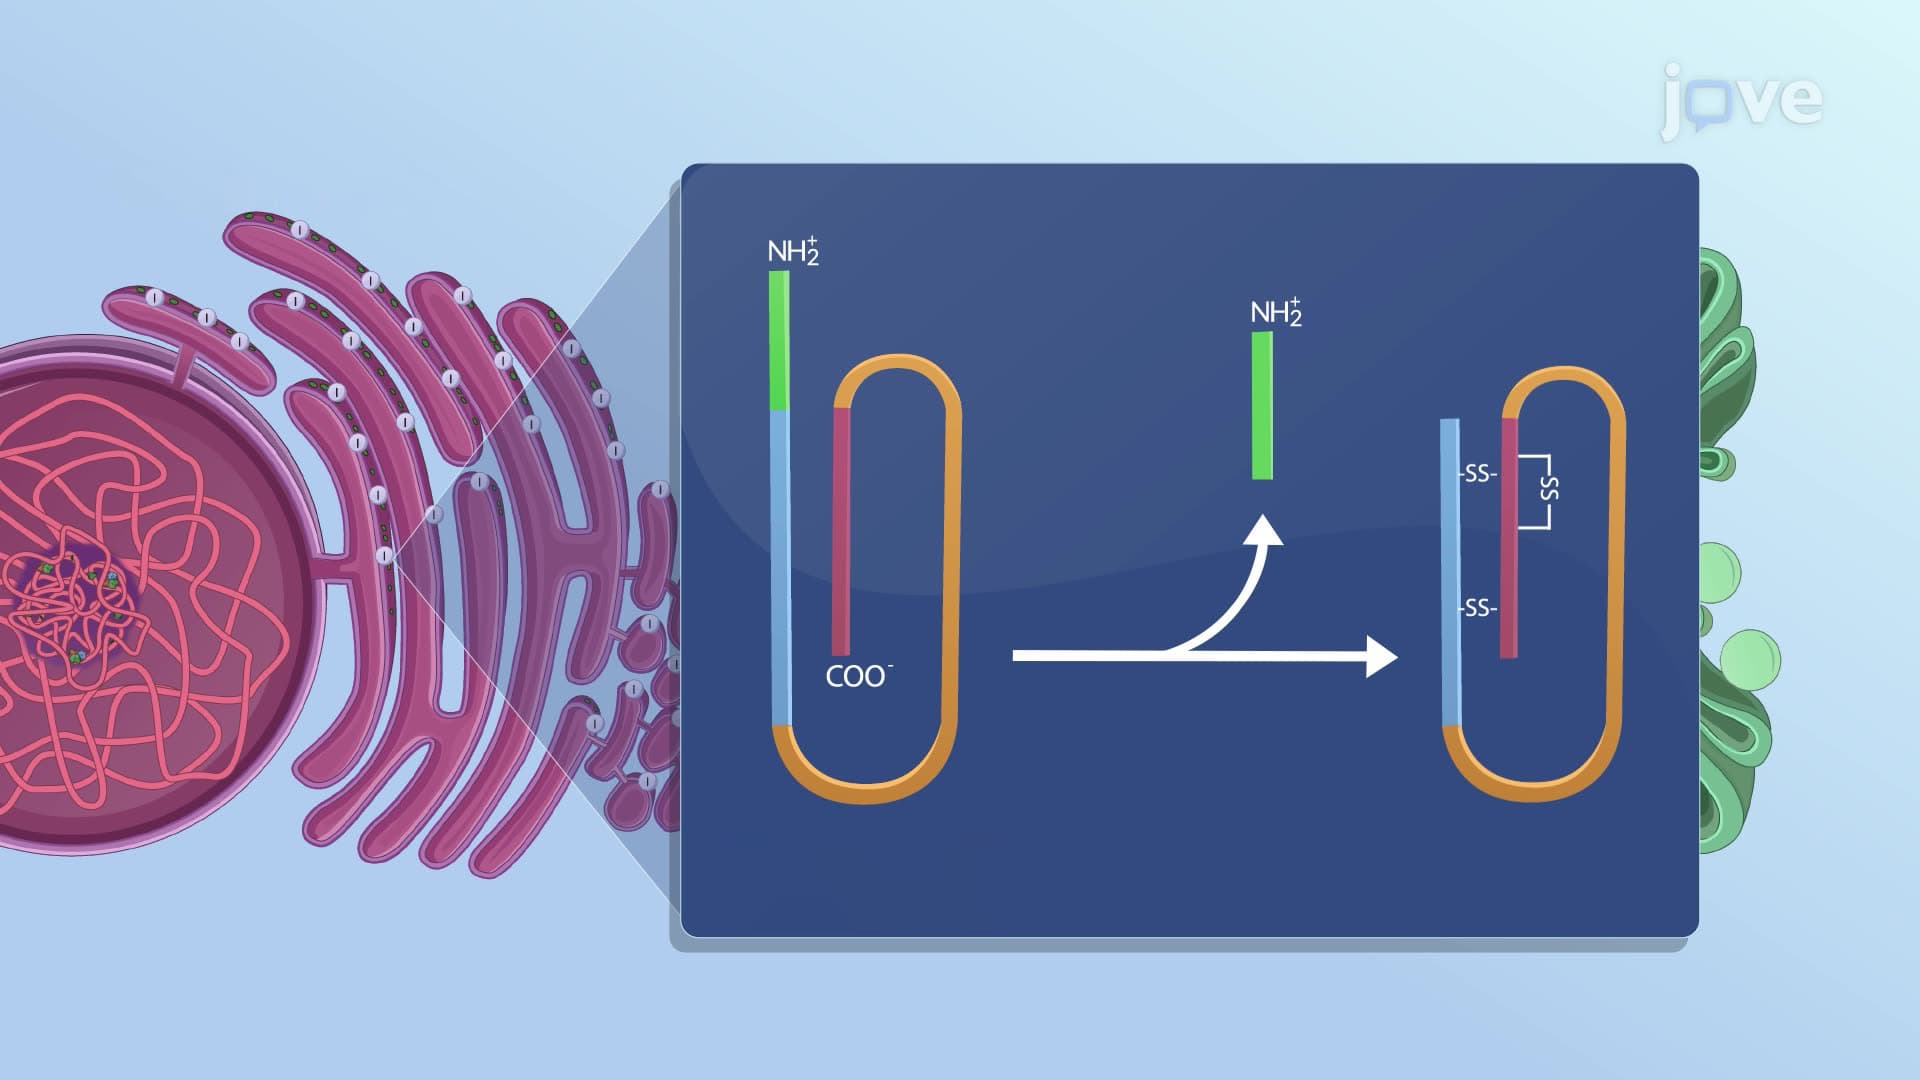
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:06
Oral Hypoglycemic Agents: Glinides
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...