Celecoxib in human milk: a case report

David C Knoppert1, Diana Stempak, Sylvain Baruchel

  • 1Department of Pharmacy, St Joseph's Hospital, Department of Paediatrics, University of Western Ontario, London, Ontario, Canada. dave.knoppert@sjhc.london.on.ca

Pharmacotherapy
|January 14, 2003
PubMed

Many women of reproductive age take the nonsteroidal antiinflammatory drug celecoxib. No data exist, however, regarding its transfer into human breast milk and safety for breastfed infants. We had the opportunity to obtain such data when a woman who was breastfeeding her infant daughter underwent emergency surgery to remove a gangrenous appendix. She received four doses of oral celecoxib 100 mg and did not breastfeed her daughter for 48 hours after taking the last dose. We analyzed samples of her breast milk and found a concentration of 133 ng/ml at approximately 5 hours after a 100-mg dose and an elimination half-life of 4.0-6.5 hours. This initial report, which should be substantiated and expanded, provides information that can help counsel parents about breastfeeding and celecoxib.

Related Concept Videos

Teratogenicity01:07

Teratogenicity

The ability of a drug to produce structural deformations and functional abnormalities in the developing embryo or the fetus is called teratogenicity, and the drug producing this effect is known as a teratogen. Teratogenic effects include stillbirth, miscarriage, intrauterine growth restriction, and neurocognitive delay. A teratogen may affect the embryo at different stages of development, which is important in determining the type and extent of the damage. During blastocyst formation, the early...
Drug Toxicity: Risk factors01:24

Drug Toxicity: Risk factors

Adverse Drug Reactions (ADRs) are potential complications that arise during pharmacotherapy, influenced by multiple risk factors. Age plays a significant role; both neonates and the elderly are at heightened risk due to their respective immature and diminished metabolic and elimination processes. Gender also impacts ADRs, with females experiencing a 1.5 to 1.7-fold greater risk than males, which may be linked to pharmacokinetic, pharmacodynamic, and hormonal differences. Notably, neonates, the...
Drug Dosing: Infants and Children01:29

Drug Dosing: Infants and Children

Pediatric patient dosages diverge from adults due to disparities in body surface area, total body water, and extracellular fluid per kilogram of body weight. The dosing regimen considers the variations in pharmacokinetics and pharmacology across distinct age groups, encompassing preterm newborns, infants, young children, older children, and adolescents. Calculation of pediatric patient doses is predicated on determining body surface area, which exhibits a superior correlation with the child's...
Pharmacokinetics in Pediatric Patients: Drug Metabolism01:24

Pharmacokinetics in Pediatric Patients: Drug Metabolism
In pediatric care, understanding the nuances of hepatic drug metabolism is crucial, as it significantly differs from that of adults. This divergence is primarily due to the developmental stage of drug-metabolizing enzymes, which affects how medications are processed in the body. In neonates, for instance, the activity of Phase I enzymes—critical for the initial breakdown of drugs—is markedly reduced, functioning at just 20–40% of the levels seen in adults. This reduction poses a challenge in...
Drug Toxicity: Allergic Reactions01:30

Drug Toxicity: Allergic Reactions

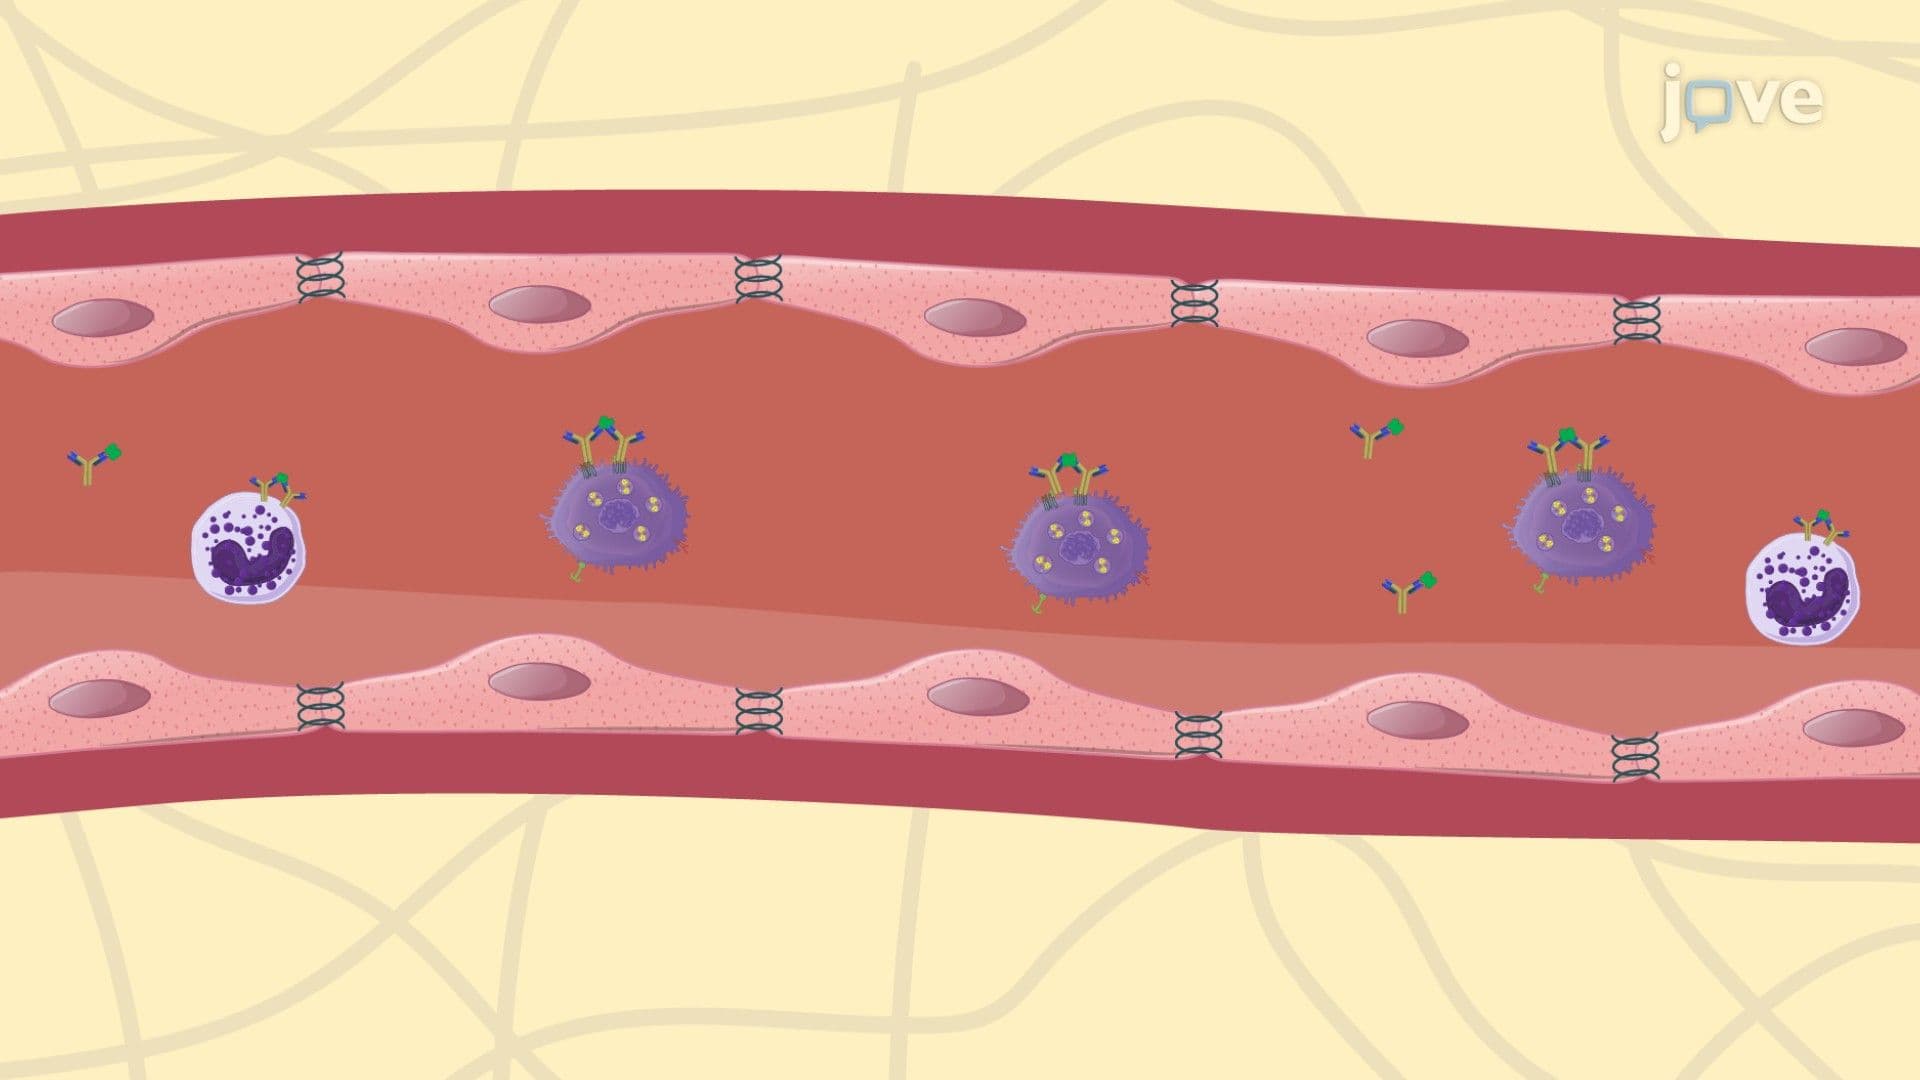
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
Pharmacokinetics in Pediatric Patients: Drug Excretion01:26

Pharmacokinetics in Pediatric Patients: Drug Excretion

In pediatric medicine, understanding the renal function and drug elimination nuances is crucial for administering safe and effective treatments. Newborns, in particular, display markedly slower renal functions than adults, profoundly affecting how drugs are cleared from their bodies. This slower drug clearance requires clinicians to extend the dosing intervals for many medications to prevent drug accumulation and toxicity while ensuring therapeutic efficacy.One key area where these adjustments...
