Related Experiment Video
Updated: Sep 27, 2026
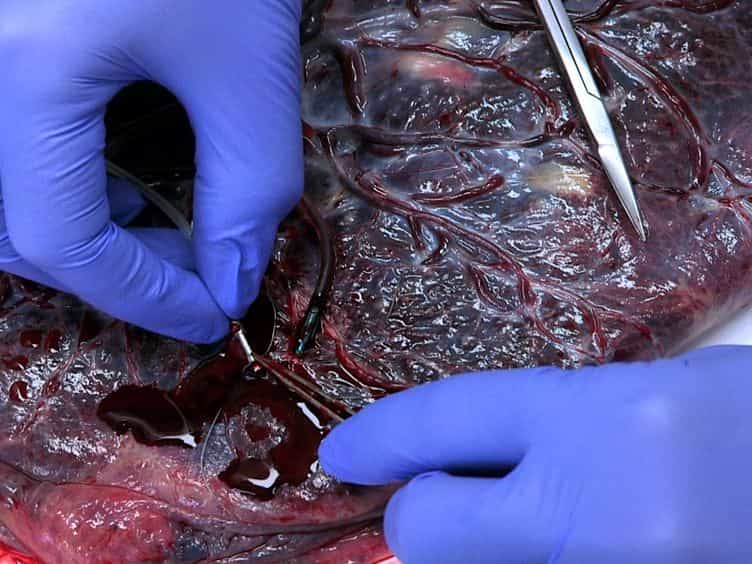

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
The presence of xenobiotic transporters in rat placenta
Tyra M Leazer1, Curtis D Klaassen
1Department of Pharmacology, Toxicology and Therapeutics, University of Kansas Medical Center, Kansas City, KS 66160-7417, USA.

Understanding the role of transporters in placental handling of xenobiotics across the maternal-fetal interface is essential to evaluate the pharmacological and toxicological potential of therapeutic agents, drugs of abuse, and other xenobiotics to which the mother is exposed during pregnancy. Therefore, the purpose of this study was to assess mRNA levels of various transporters in placenta and to compare these to levels in maternal liver and kidney, predominant organs of excretion, to determine which transporters are likely to have a role in xenobiotic transfer within the placenta. During late stage pregnancy, relative amounts of mRNA levels of 40 genes representing 11 families/group of transporters were assessed in placenta with respect to relative maternal liver and kidney mRNA levels. Members of the following transporter families were assessed: three multidrug resistance (Mdr), six multidrug resistance-associated protein (Mrp), eight organic anion-transporting polypeptide (Oatp), three organic anion transporters (Oat), five organic cation transporters (Oct), two bile acid transporters (Na(+)/taurocholate-cotransporting polypeptide and bile salt export protein), four metal (ZnT1, divalent metal transporter 1, Menkes and Wilsons), a prostaglandin, two peptide, two sterolin, and four nucleoside transporters. Of the 40 genes evaluated, 16 [Mdr1a and 1b, Mrp1 and 5, Oct3 and Octn1, Oatp3 and 12, four metal, a prostaglandin, AbcG8, equilibrative nucleoside transporter 1 (ENT1), and ENT2] were expressed in placenta at concentrations similar to or higher than in maternal liver and kidney. The abundance of these mRNA transcripts in placenta suggests a role for these transporters in placental transport of xenobiotics and supports their role in the transport of endogenous substances.
Understanding the role of transporters in placental handling of xenobiotics across the maternal-fetal interface is essential to evaluate the pharmacological and toxicological potential of therapeutic agents, drugs of abuse, and other xenobiotics to which the mother is exposed during pregnancy. Therefore, the purpose of this study was to assess mRNA levels of various transporters in placenta and to compare these to levels in maternal liver and kidney, predominant organs of excretion, to determine which transporters are likely to have a role in xenobiotic transfer within the placenta. During late stage pregnancy, relative amounts of mRNA levels of 40 genes representing 11 families/group of transporters were assessed in placenta with respect to relative maternal liver and kidney mRNA levels. Members of the following transporter families were assessed: three multidrug resistance (Mdr), six multidrug resistance-associated protein (Mrp), eight organic anion-transporting polypeptide (Oatp), three organic anion transporters (Oat), five organic cation transporters (Oct), two bile acid transporters (Na(+)/taurocholate-cotransporting polypeptide and bile salt export protein), four metal (ZnT1, divalent metal transporter 1, Menkes and Wilsons), a prostaglandin, two peptide, two sterolin, and four nucleoside transporters. Of the 40 genes evaluated, 16 [Mdr1a and 1b, Mrp1 and 5, Oct3 and Octn1, Oatp3 and 12, four metal, a prostaglandin, AbcG8, equilibrative nucleoside transporter 1 (ENT1), and ENT2] were expressed in placenta at concentrations similar to or higher than in maternal liver and kidney. The abundance of these mRNA transcripts in placenta suggests a role for these transporters in placental transport of xenobiotics and supports their role in the transport of endogenous substances.


Related Concept Videos
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:14
Hepatic Drug Clearance: Role of Transporters
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion, mediated...
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:06
Carrier-Mediated Transport
Active transport involves two types of membrane-spanning transporters: uptake and efflux. Uptake transporters are expressed in the small...