Related Experiment Video
Updated: Sep 27, 2026
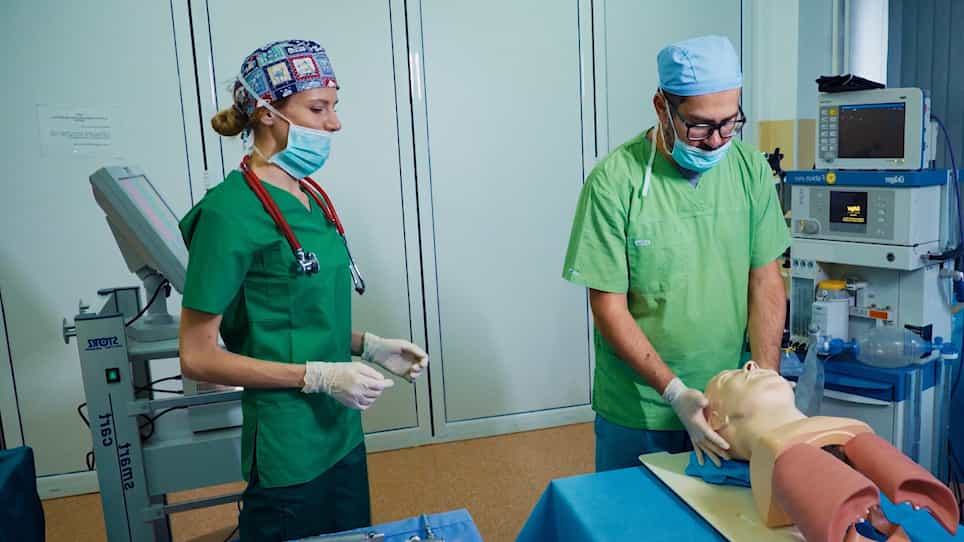
The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
Rapid sequence intubation in Scottish urban emergency departments
C A Graham1, D Beard, A J Oglesby
1Department of Accident and Emergency Medicine, Southern General Hospital, Glasgow, UK. colingrahamlt@ukonline.co.uk

Objective:
Airway care is the cornerstone of resuscitation. In UK emergency department practice, this care is provided by anaesthetists and emergency physicians. The aim of this study was to determine current practice for rapid sequence intubation (RSI) in a sample of emergency departments in Scotland.
Methods:
Two year, multicentre, prospective observational study of endotracheal intubation in the emergency departments of seven Scottish urban teaching hospitals.
Results:
1631 patients underwent an intubation attempt in the emergency department and 735 patients satisfied the criteria for RSI. Emergency physicians intubated 377 patients and anaesthetists intubated 355 patients. There was no difference in median age between the groups but there was a significantly greater proportion of men (73.2% versus 65.3%, p=0.024) and trauma patients (48.5% versus 37.4%, p=0.003) in the anaesthetic group. Anaesthetists had a higher initial success rate (91.8% versus 83.8%, p=0.001) and achieved more good (Cormack-Lehane Grade I and II) views at laryngoscopy (94.0% versus 89.3%, p=0.039). There was a non-significant trend to more complications in the group of patients intubated by emergency physicians (8.7% versus 12.7%, p=0.104). Emergency physicians intubated a higher proportion of patients with physiological compromise (91.8% versus 86.1%, p=0.027) and a higher proportion of patients within 15 minutes of arrival (32.6% versus 11.3%, p<0.0001).
Conclusion:
Anaesthetists achieve more good views at laryngoscopy with higher initial success rates during RSI. Emergency physicians perform RSI on a higher proportion of critically ill patients and a higher proportion of patients within 15 minutes of arrival. Complications may be fewer in the anaesthetists' group, but this could be related to differences in patient populations. Training issues for RSI and emergency airway care are discussed. Complication rates for both groups are in keeping with previous studies.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.