Related Experiment Video
Updated: Aug 19, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Elective high frequency oscillatory ventilation versus conventional ventilation for acute pulmonary dysfunction in
D J Henderson-Smart1, T Bhuta, F Cools
1NSW Centre for Perinatal Health Services Research, Queen Elizabeth II Institute for Mothers and Infants, Building DO2, University of Sydney, Sydney, NSW, Australia, 2006. dhs@perinatal.usyd.edu.au

Background:
Respiratory failure due to lung immaturity is a major cause of mortality in preterm infants. Although intermittent positive pressure ventilation (IPPV) saves lives, lung distortion during its use is associated with lung injury and chronic lung disease (CLD). Conventional IPPV is provided at 30-80 breaths per minute while a newer form of ventilation called high frequency oscillatory ventilation (HFOV) provides 'breaths' at 10-15 cycles per second. This has been shown to result in less lung injury in experimental studies.
Objectives:
The objective of this review is to determine whether the elective use of high frequency oscillatory ventilation as compared to conventional ventilation (CV) in preterm infants who are mechanically ventilated for the respiratory distress syndrome decreases the incidence of chronic lung disease, without adverse effects.
Search Strategy:
Searches were made of the Oxford Database of Perinatal Trials, MEDLINE, EMBASE, previous reviews including cross references, abstracts, conferences and symposia proceedings, expert informants, journal hand searching by the Cochrane Collaboration, mainly in the English language. The search was updated in October 2002.
Selection Criteria:
Randomized controlled trials comparing HFOV and CV in preterm or low birth weight infants with pulmonary dysfunction, mainly due to RDS, who are to be given IPPV. Randomization and commencement of treatment should have been as soon as possible after the start of IPPV and usually in the first 12 hours of life.
Data Collection And Analysis:
The methodological quality of each trial was independently reviewed by the various authors. Each author extracted data separately; they were compared and differences were resolved. Treatment effects were expressed using relative risk (RR) and risk difference (RD). From 1/RD the number needed to treat (NNT) for benefits, and number needed to harm (NNH) for adverse effects, were calculated. 95% confidence intervals were used.
Main Results:
Meta-analysis of the ten eligible studies comparing HFOV with CV revealed no evidence of effect on mortality at 28-30 days of age or at approximately term equivalent age. These results were consistent across studies. HFOV caused a significant reduction in CLD in survivors at term equivalent GA. However, the effect was not large in absolute terms [NNT 17 (10, 50)], and was inconsistent across studies. HFOV caused a significant reduction in the aggregated outcome, death or CLD at term equivalent GA. Again, however, the effect was not large [(NNT 20 (11, 100)] and was not consistent across studies. Pre-specified subgroup analyses according to use of a high volume strategy, or use of surfactant, did not identify subgroups in which there was evidence of effect on death, or in which the size of effect on CLD was substantially increased, or in which heterogeneity of treatment effect on CLD was removed. Short term neurological morbidity caused by HFOV was found in some studies, but this effect was not statistically significant overall. The subgroup of two trials not using a high volume strategy with HFOV found increased rates of Grade 3 or 4 IVH and of periventricular leukomalacia. An adverse effect of HFOV on longer term neurodevelopment was found in one large trial but not in two other small trials which reported this outcome.
Reviewer'S Conclusions:
There is strong evidence that HFOV had no significant effect on death as this result was consistent across trials. Although HFOV caused a modest reduction in CLD, this evidence is weaker, because of inconsistencies across trials in this effect. In general, subgroup analyses according to use of high volume strategy, or surfactant, did not remove this heterogeneity, which therefore remains largely unexplained. Any future trials on elective HFOV should target those infants who are at most risk of CLD (extremely preterm), compare different strategies for generating HFOV and report important long term pulmonary and neurodevelopmental outcomes. Economic analysis should also be incorporated.
More Related Videos
 08:58
Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
 07:15
Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:29
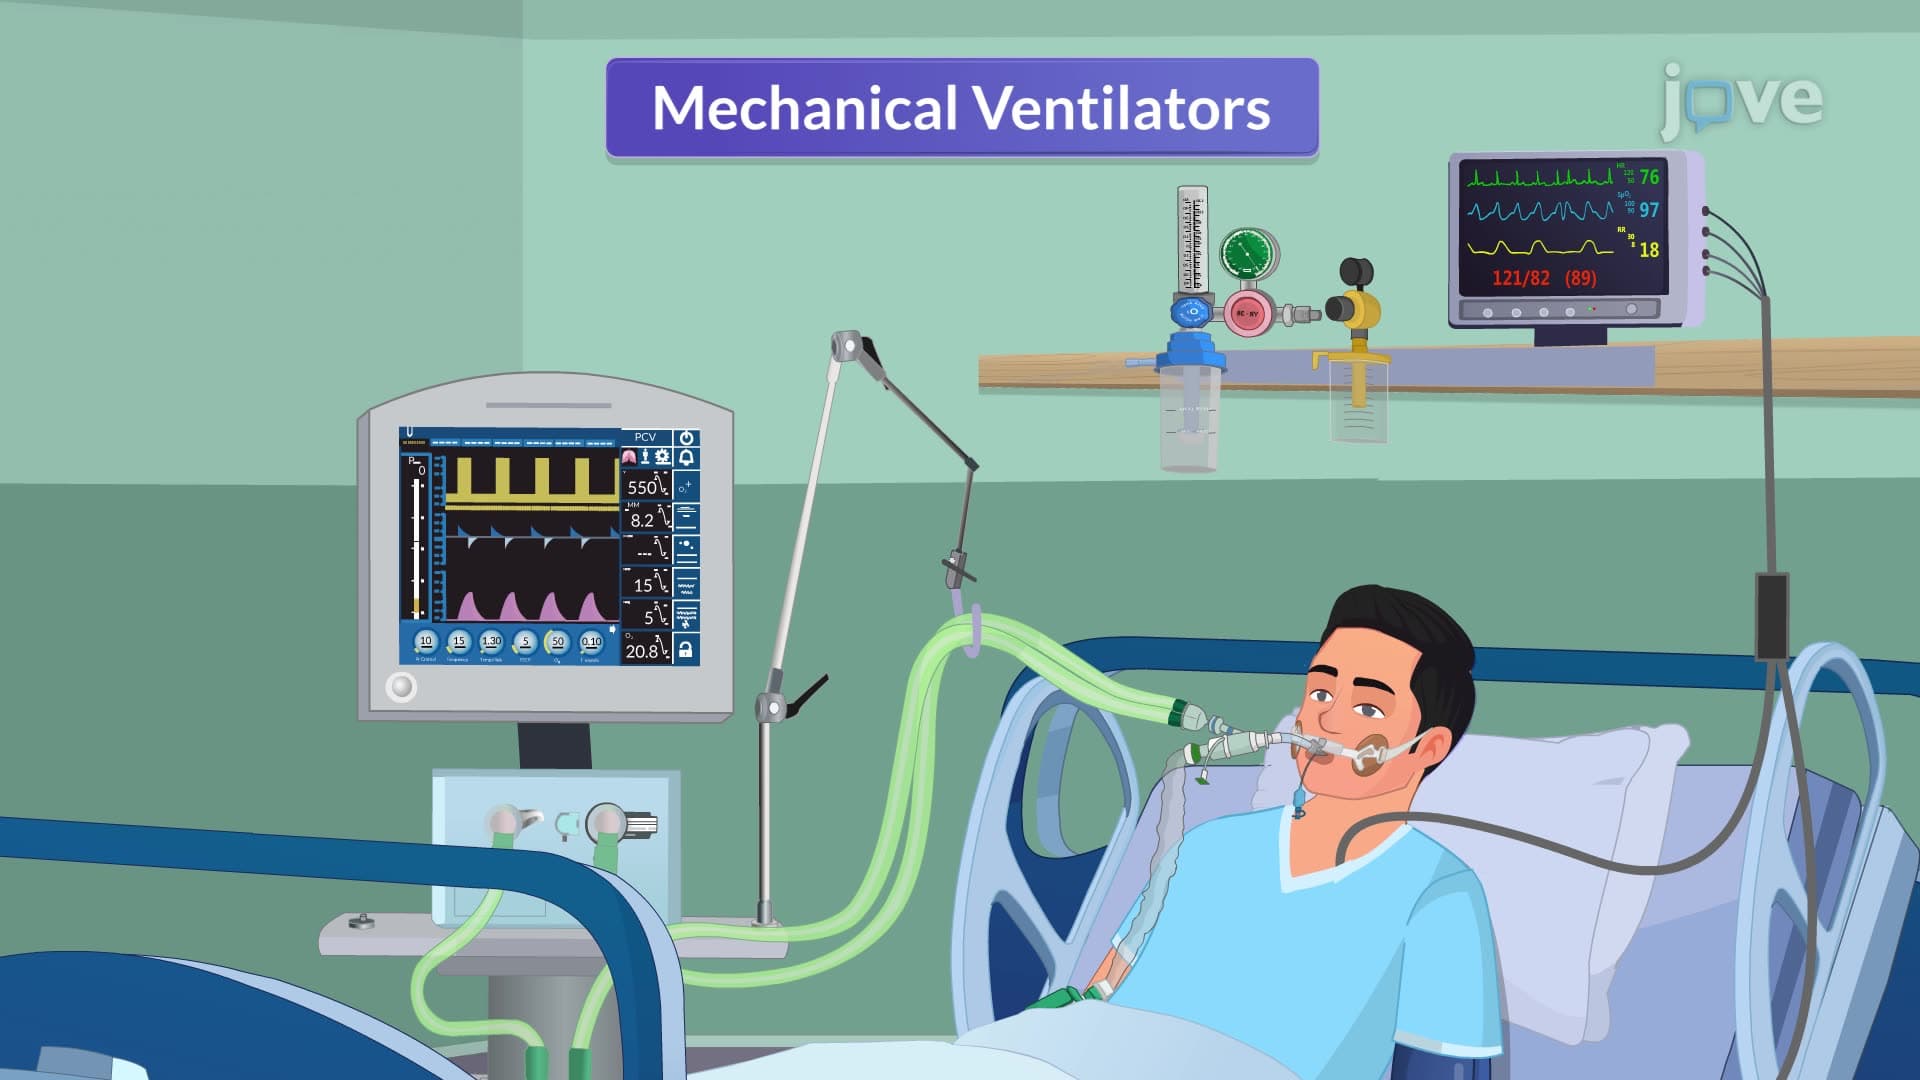
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...