Surviving intensive care: a report from the 2002 Brussels Roundtable
Related Experiment Video
Updated: Aug 4, 2026
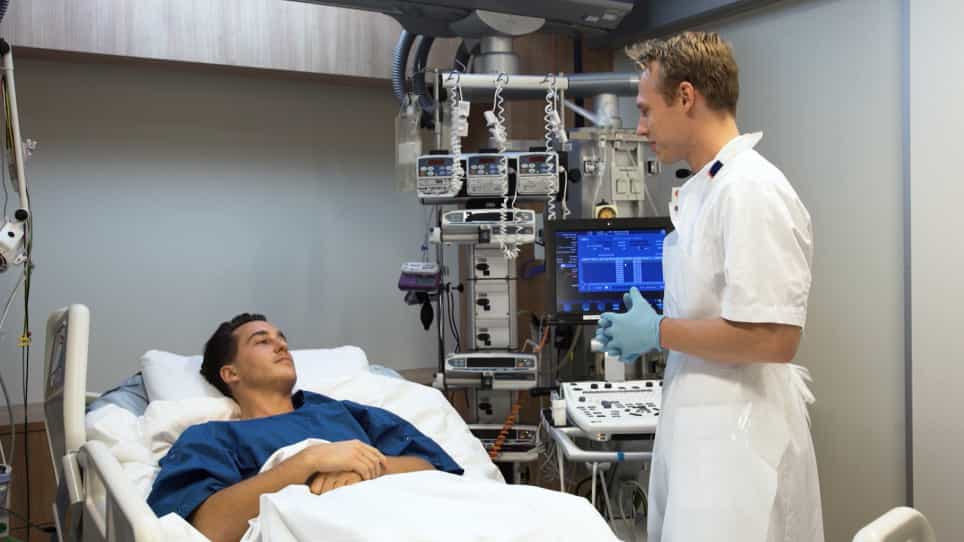
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
1CRISMA, Laboratory, Department of Critical Care Medicine, School of Medicine, University of Pittsburgh, 3550 Terrace Street, Pittsburgh, PA 15261, USA. angusdc@ccm.upmc.edu

Abstract:
The traditional goal of intensive care has been to decrease short-term mortality. While worthy, this goal fails to address the issue of what it means to survive intensive care. Key questions include whether intensive care survivors have optimal long-term outcomes and whether ICU care decisions would change if we knew more about these outcomes. The 2002 Brussels Roundtable, "Surviving Intensive care", highlighted these issues, summarizing the available evidence on natural history and risk factors for critical illness and outlining future directions for care and research. Critical illness is associated with a wide array of serious and concerning long-term sequelae that interfere with optimal patient-centered outcomes. Although traditional short-term outcomes, such as hospital mortality, remain extremely important, they are not likely to be adequate surrogates for subsequent patient-centered outcomes. As such, it is important to focus specifically on how critical illness and intensive care affects a patient's and relatives' long-term health and well-being. There are a large number of potential pre-, intra-, and post-ICU factors that may improve or worsen these outcomes, and these factors are subjects for future research. In addition, future clinical trials of ICU therapies should include long-term follow-up of survival, quality of life, morbidity, functional status, and costs of care. Follow-up ought to be for at least six months. The SF-36 and EuroQOL EQ-5D are the best-suited instruments for measuring quality of life in multicenter critical care trials though further methodologic research and instrument design is encouraged. There are also opportunities today to improve care. Key to taking advantage of such opportunities is the need for a global awareness of critical illness as an entity that begins and ends outside the ICU 'box'. Specific interventions that show promise for improving care include ICU discharge screening tools and ICU follow-up clinics.
Related Concept Videos
 01:21
Interdisciplinary Care: The Health Care Team-I
Physicians
The physician's primary responsibility is to diagnose illness and direct the medical or surgical treatment of the condition. The authority to admit patients to a healthcare agency or institution and practice care within that setting is granted to physicians by the healthcare agency or institution itself.
 01:18
Interdisciplinary Care: The Health Care Team-II
Physical Therapist
A physical therapist (PT) aims to restore function or prevent additional impairment in a patient following an injury or disease. Massage, heat, cold, water, sonar waves, exercises, and electrical stimulation are some treatments used by PTs to treat...
 01:19
Standards of Care II
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Aneurysm III: Interprofessional Care
 01:20
Acute Kidney Injury V: Interprofessional Care