Functional significance of hepatic arterial flow reserve in patients with cirrhosis
Related Experiment Video
Updated: Sep 27, 2026
Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
Alexander Zipprich1, Norbert Steudel, Curd Behrmann
1First Department of Medicine, Martin-Luther-University Halle-Wittenberg, Germany.

Abstract:
In cirrhosis, hepatic arterial vasodilatation occurs in response to reduced portal venous blood flow. However, although the hepatic arterial flow reserve is high in patients with cirrhosis, its impact on hepatic function is unknown. This study investigated the effect of adenosine-induced hepatic arterial vasodilatation on different markers of liver function. In 20 patients with cirrhosis (Child-Pugh class A/B/C: n = 2/7/11) adenosine (2-30 microg x min(-1) x kg body wt(-1)) was infused into the hepatic artery and hepatic arterial average peak flow velocities (APV), pulsatility indices (PI), and blood flow volumes (HABF) were measured using digital angiography and intravascular Doppler sonography. Indocyanine green (ICG), lidocaine, and galactose were administered intravenously in doses of 0.5, 1.0, and 500 mg/kg body weight in the presence of adenosine-induced hepatic arterial vasodilatation and, on a separate study day, without adenosine. ICG disappearance, galactose elimination capacity (GEC), and formation of the lidocaine metabolite monoethylglycinxylidide (MEGX) were assessed. Adenosine markedly increased APV and HABF and markedly decreased PI. Serum MEGX concentrations were 63.7 +/- 18.2 (median, 62; range, 36-107) and 99.0 +/- 46.3 (82.5; 49-198) ng/mL in the absence and presence of adenosine infusion, respectively (P =.001). Adenosine-induced changes in MEGX concentrations were correlated inversely to changes in APV (r = -0.5, P =.02) and PI (r = -0.55, P =.01) and were more marked in Child-Pugh class C compared with Child-Pugh class A patients (57.4 +/- 49.9 [44; -14 to 140] vs. 8.4 +/- 16.5 [13; -11 to 35] ng/mL, P <.01). In conclusion, hepatic arterial vasodilatation provides substantial functional benefit in patients with cirrhosis. The effect does not depend directly on hepatic arterial macroperfusion and is observed preferentially in patients with decompensated disease.


Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:24
Cirrhosis II: Pathophysiology
 01:22
Portal Hypertension
 01:20
Vascular Resistance
The primary determinants of vascular resistance are vessel diameter, blood viscosity, and vessel length. Among these, vessel diameter plays the most significant role due to the fourth power relationship described by...
 01:09
Hepatic Drug Clearance: Restrictive and Nonrestrictive Clearance
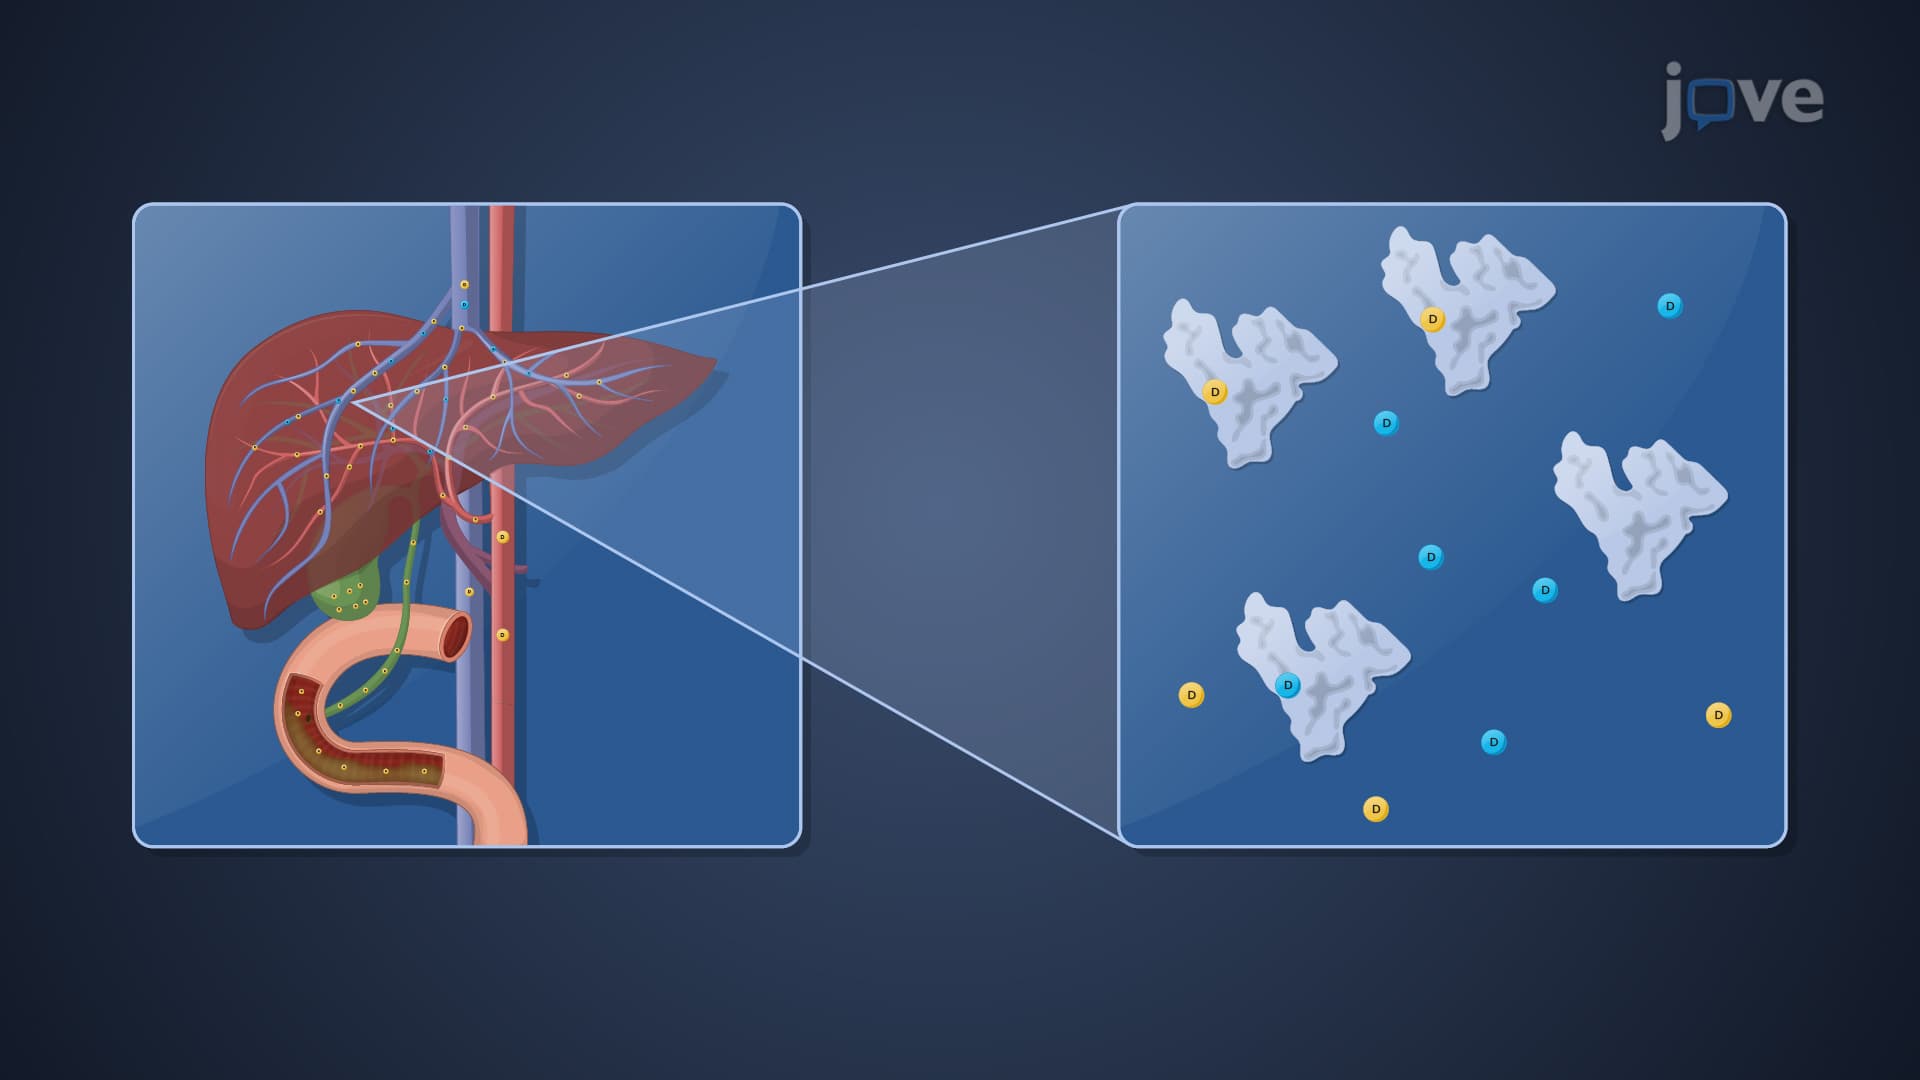
Most drugs undergo restrictive clearance, which is proportional to the...