Prognostic factors in allogeneic transplantation for patients with high-risk multiple myeloma after reduced intensity conditioning
Related Experiment Video
Updated: Sep 25, 2026
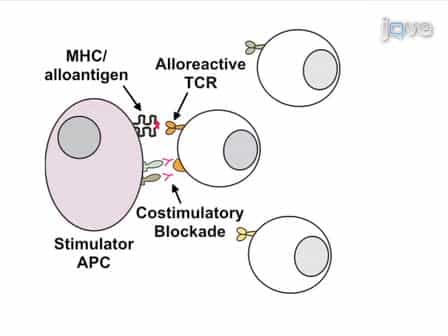
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Choon Kee Lee1, Ashraf Badros, Bart Barlogie
1The Myeloma Institute for Research and Therapy, The University of Arkansas for Medical Sciences, Little Rock, AR, USA. leehoonkee@uams.edu

Objectives:
The aim of this study was to identify prognostic factors for outcome of high-risk patients with multiple myeloma after allogeneic transplantation prepared by reduced intensity conditioning (RIC).
Materials And Methods:
Data from 45 consecutive patients (median age 52 years, range 38-68), who received grafts from a sibling (n = 34) or unrelated donor (n = 11) were analyzed. Fourteen patients received an RIC allotransplant while chemosensitive (>/=partial remission [PR]), whereas 31 chemoresistant patients (
Results:
Twenty-nine (64%) were in a complete remission (CR) or near CR, 5 were in PR, and 5 had progressive disease. Twenty-five patients died, 17 of transplant-related complications, 7 of progressive disease, and 1 of a nontransplant-related cause. With a median follow-up of 15 months, the following factors were significantly associated with a better event-free survival (EFS) probability at 3 years: chemosensitive disease (64% vs 12%), pretransplant performance score (PS, Zubrod)
Conclusions:
Our data suggest that although RIC allotransplant induces high rates of CR and near CR, even in refractory disease, it appears to result in a durable response only if it is applied early in the disease in high-risk patients, when they still are chemosensitive and have an adequate PS.