Related Experiment Video
Updated: Mar 25, 2026
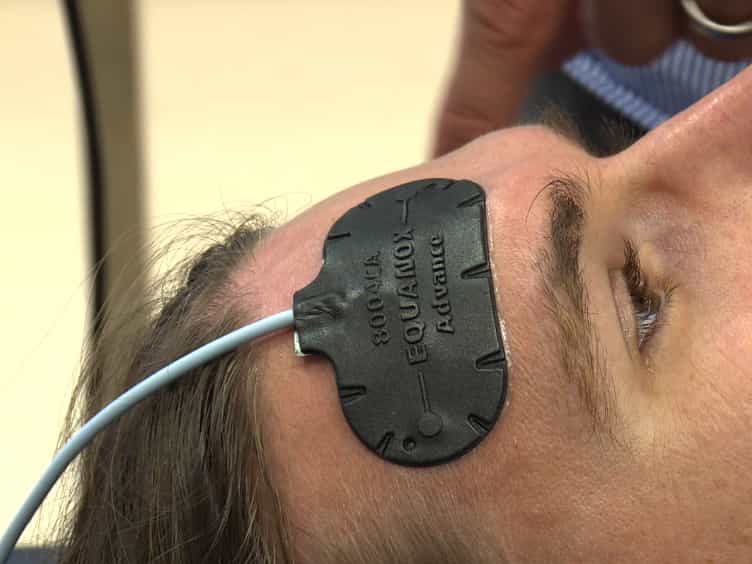
A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
Mechanisms of the cerebrovascular response to apnoea in humans
Tadeusz Przybyłowski1, Muhammad-Fuad Bangash, Kevin Reichmuth
1Department of Population Health Sciences, University of Wisconsin-Madison, the John Rankin Laboratory of Pulmonary Medicine, and the Middleton Veterans Administration Hospital, 53705, USA. przyb@amwaw.edu.pl

Abstract:
We measured ventilation, arterial O2 saturation, end-tidal CO2 (PET,CO2), blood pressure (intra-arterial catheter or photoelectric plethysmograph), and flow velocity in the middle cerebral artery (CFV) (pulsed Doppler ultrasound) in 17 healthy awake subjects while they performed 20 s breath holds under control conditions and during ganglionic blockade (intravenous trimethaphan, 4.4 +/- 1.1 mg min-1 (mean +/- S.D.)). Under control conditions, breath holding caused increases in PET,CO2 (7 +/- 1 mmHg) and in mean arterial pressure (MAP) (15 +/- 2 mmHg). A transient hyperventilation (PET,CO2 -7 +/- 1 mmHg vs. baseline) occurred post-apnoea. CFV increased during apnoeas (by 42 +/- 3 %) and decreased below baseline (by 20 +/- 2 %) during post-apnoea hyperventilation. In the post-apnoea recovery period, CFV returned to baseline in 45 +/- 4 s. The post-apnoea decrease in CFV did not occur when hyperventilation was prevented. During ganglionic blockade, which abolished the increase in MAP, apnoea-induced increases in CFV were partially attenuated (by 26 +/- 2 %). Increases in PET,CO2 and decreases in oxyhaemoglobin saturation (Sa,O2) (by 2 +/- 1 %) during breath holds were identical in the intact and blocked conditions. Ganglionic blockade had no effect on the slope of the CFV response to hypocapnia but it reduced the CFV response to hypercapnia (by 17 +/- 5 %). We attribute this effect to abolition of the hypercapnia-induced increase in MAP. Peak increases in CFV during 20 s Mueller manoeuvres (40 +/- 3 %) were the same as control breath holds, despite a 15 mmHg initial, transient decrease in MAP. Hyperoxia also had no effect on the apnoea-induced increase in CFV (40 +/- 4 %). We conclude that apnoea-induced fluctuations in CFV were caused primarily by increases and decreases in arterial partial pressure of CO2 (Pa,CO2) and that sympathetic nervous system activity was not required for either the initiation or the maintenance of the cerebrovascular response to hyper- and hypocapnia. Increased MAP or other unknown influences of autonomic activation on the cerebral circulation played a smaller but significant role in the apnoea-induced increase in CFV; however, negative intrathoracic pressure and the small amount of oxyhaemoglobin desaturation caused by 20 s apnoea did not affect CFV.


Related Concept Videos
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical...
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:22
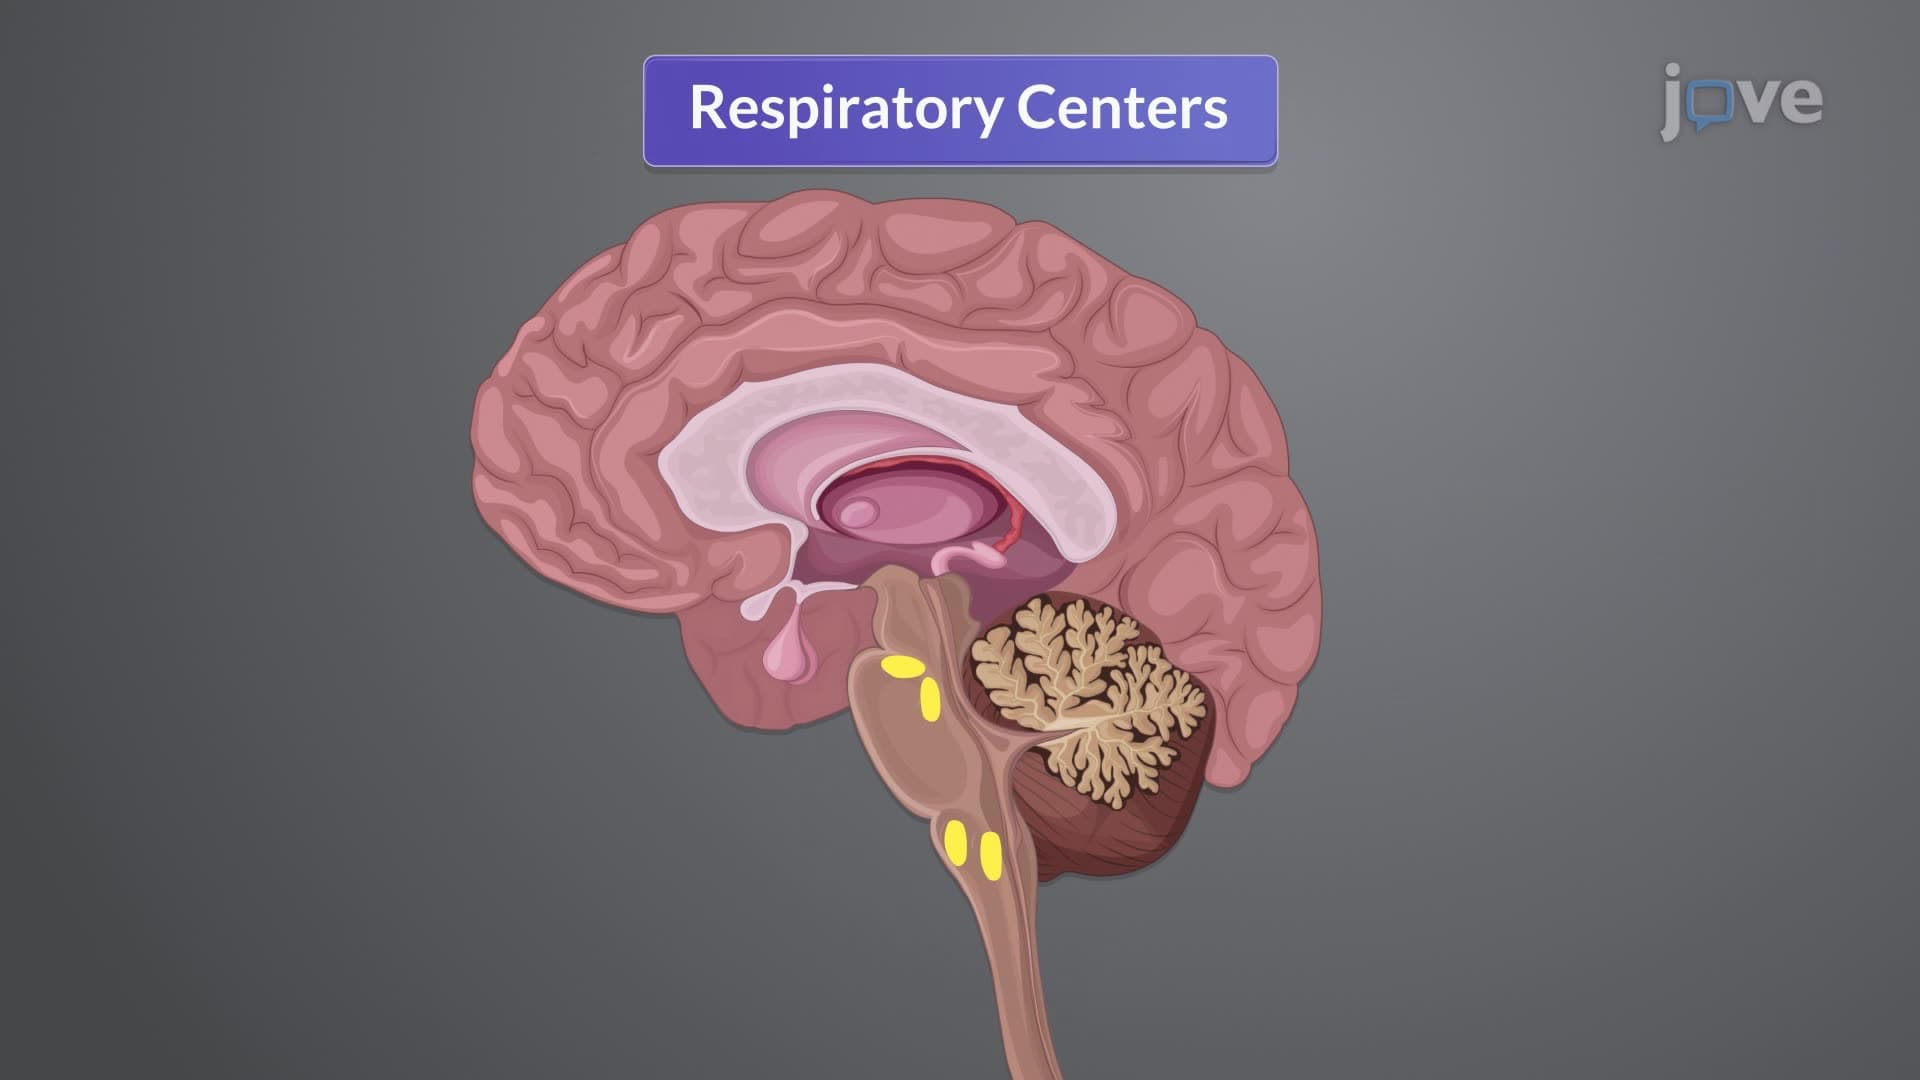
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:31
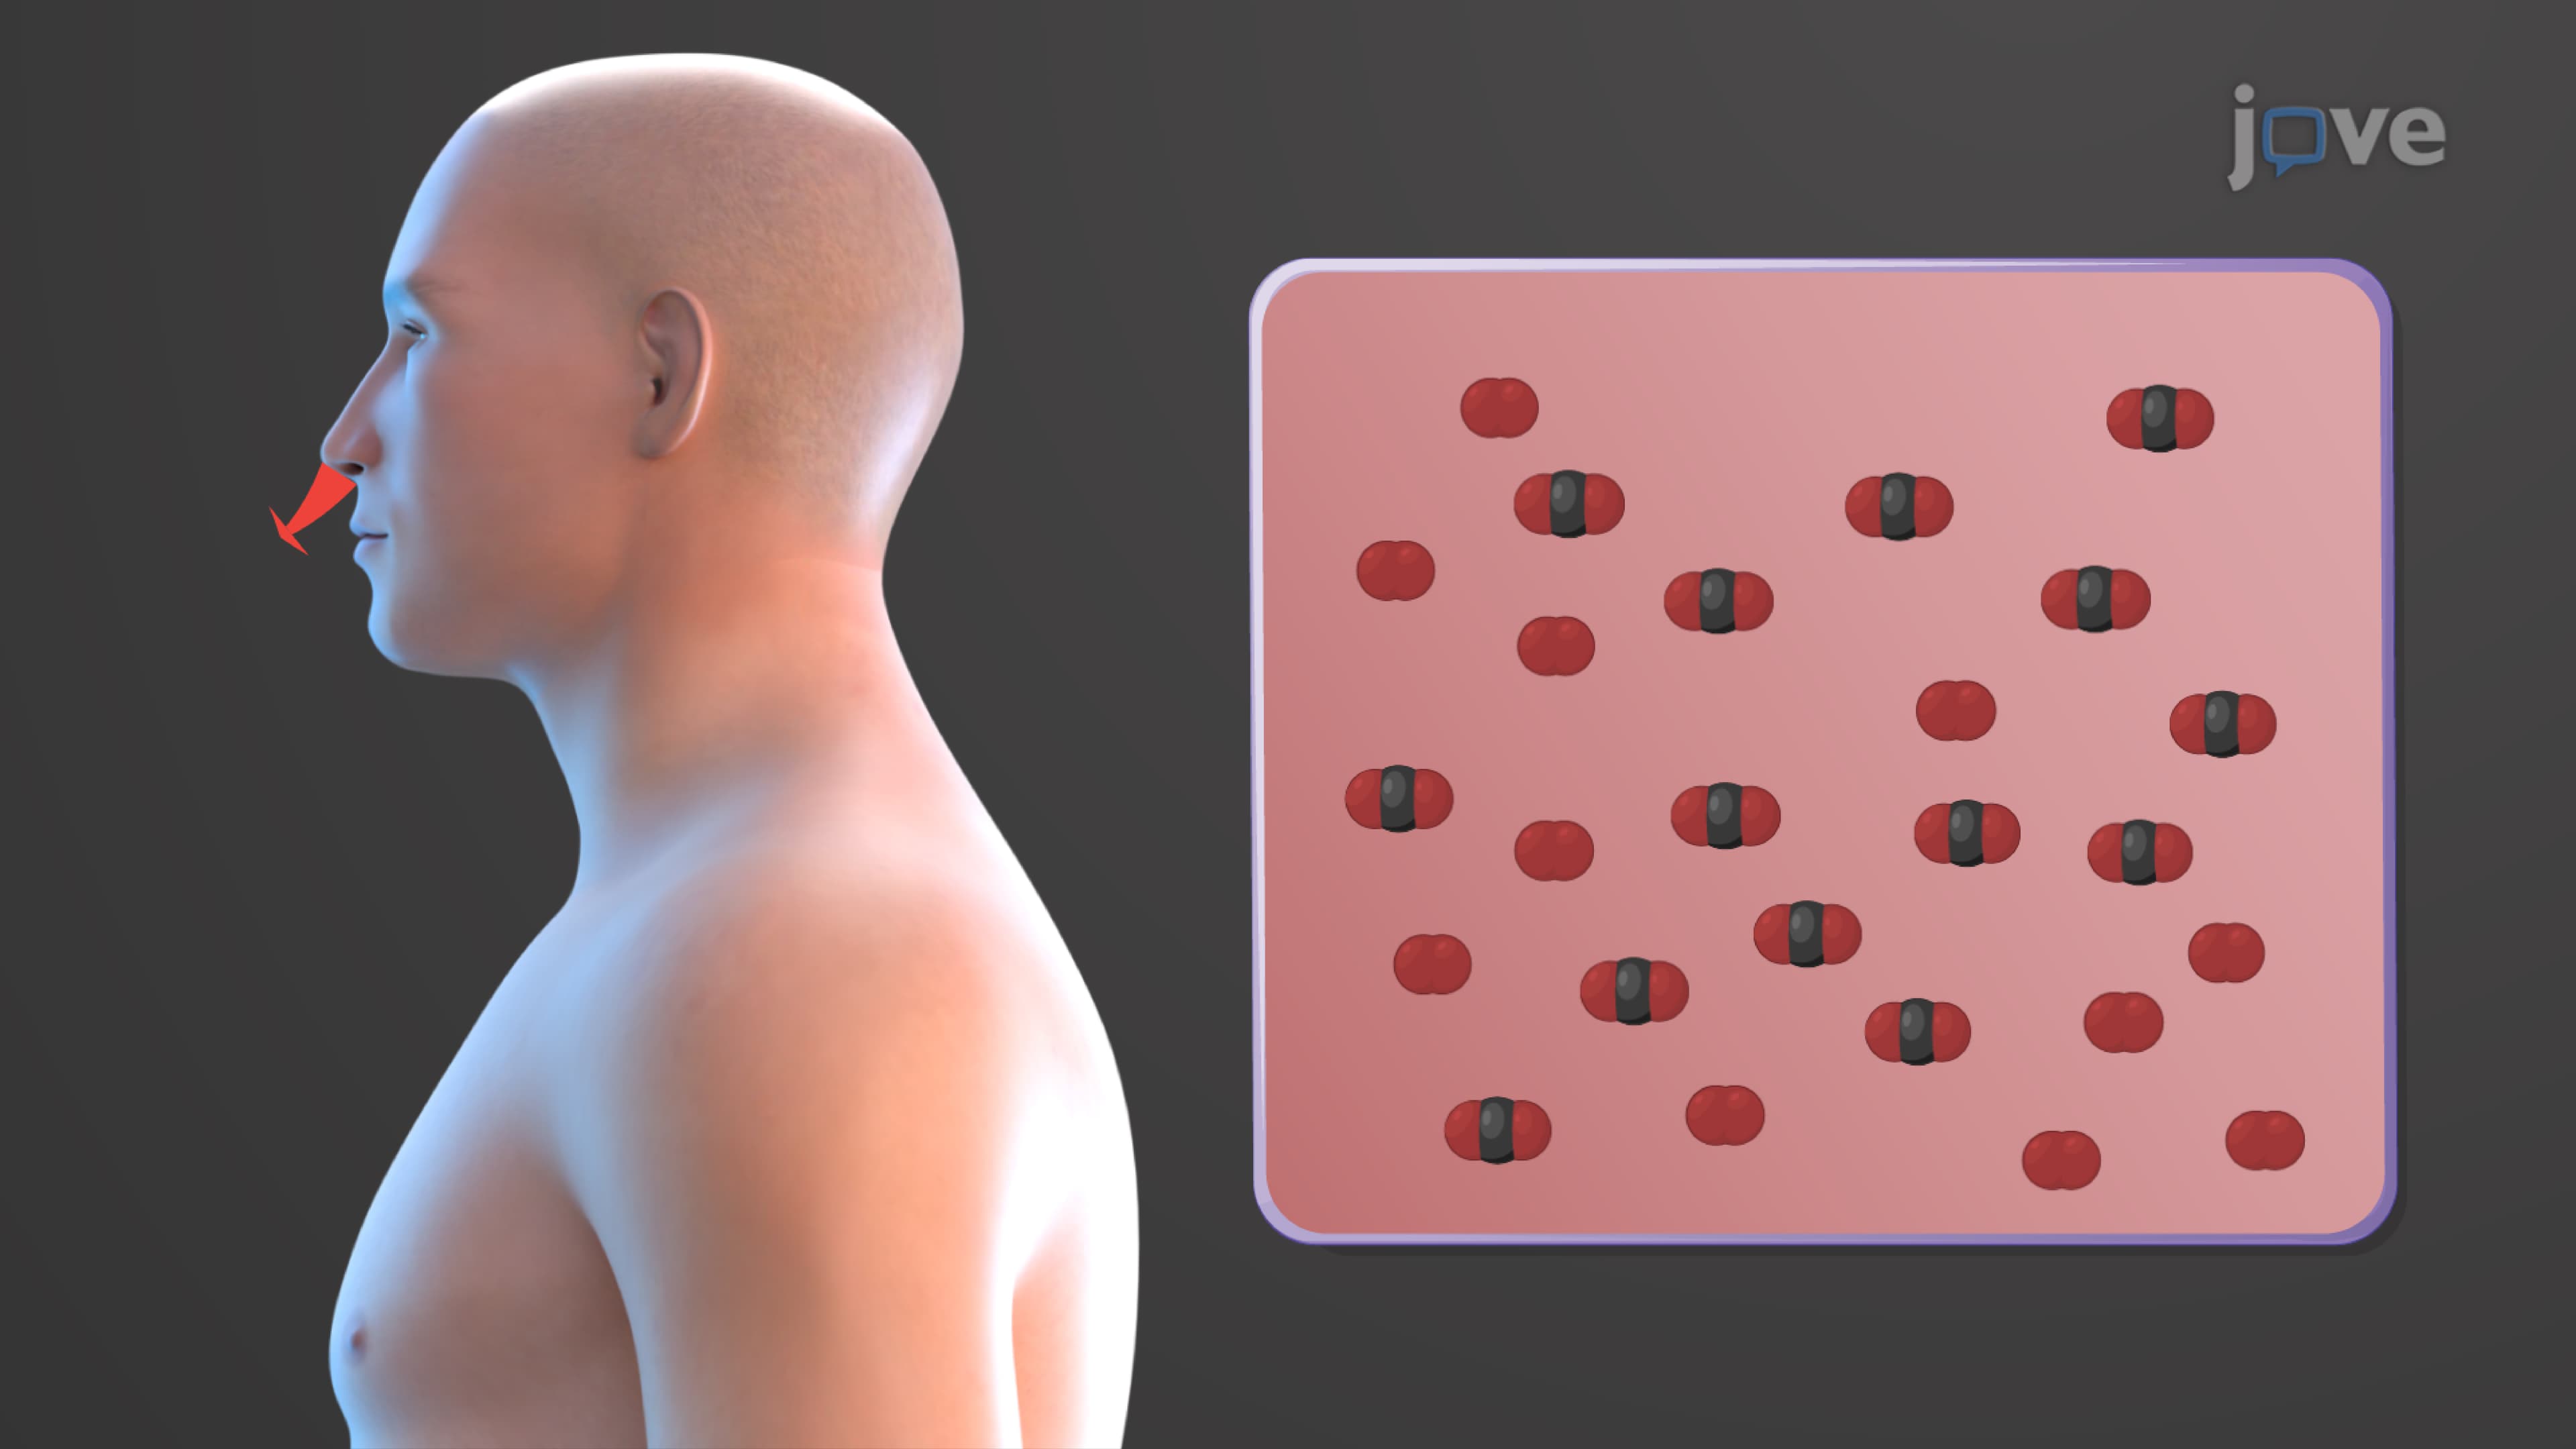
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:18
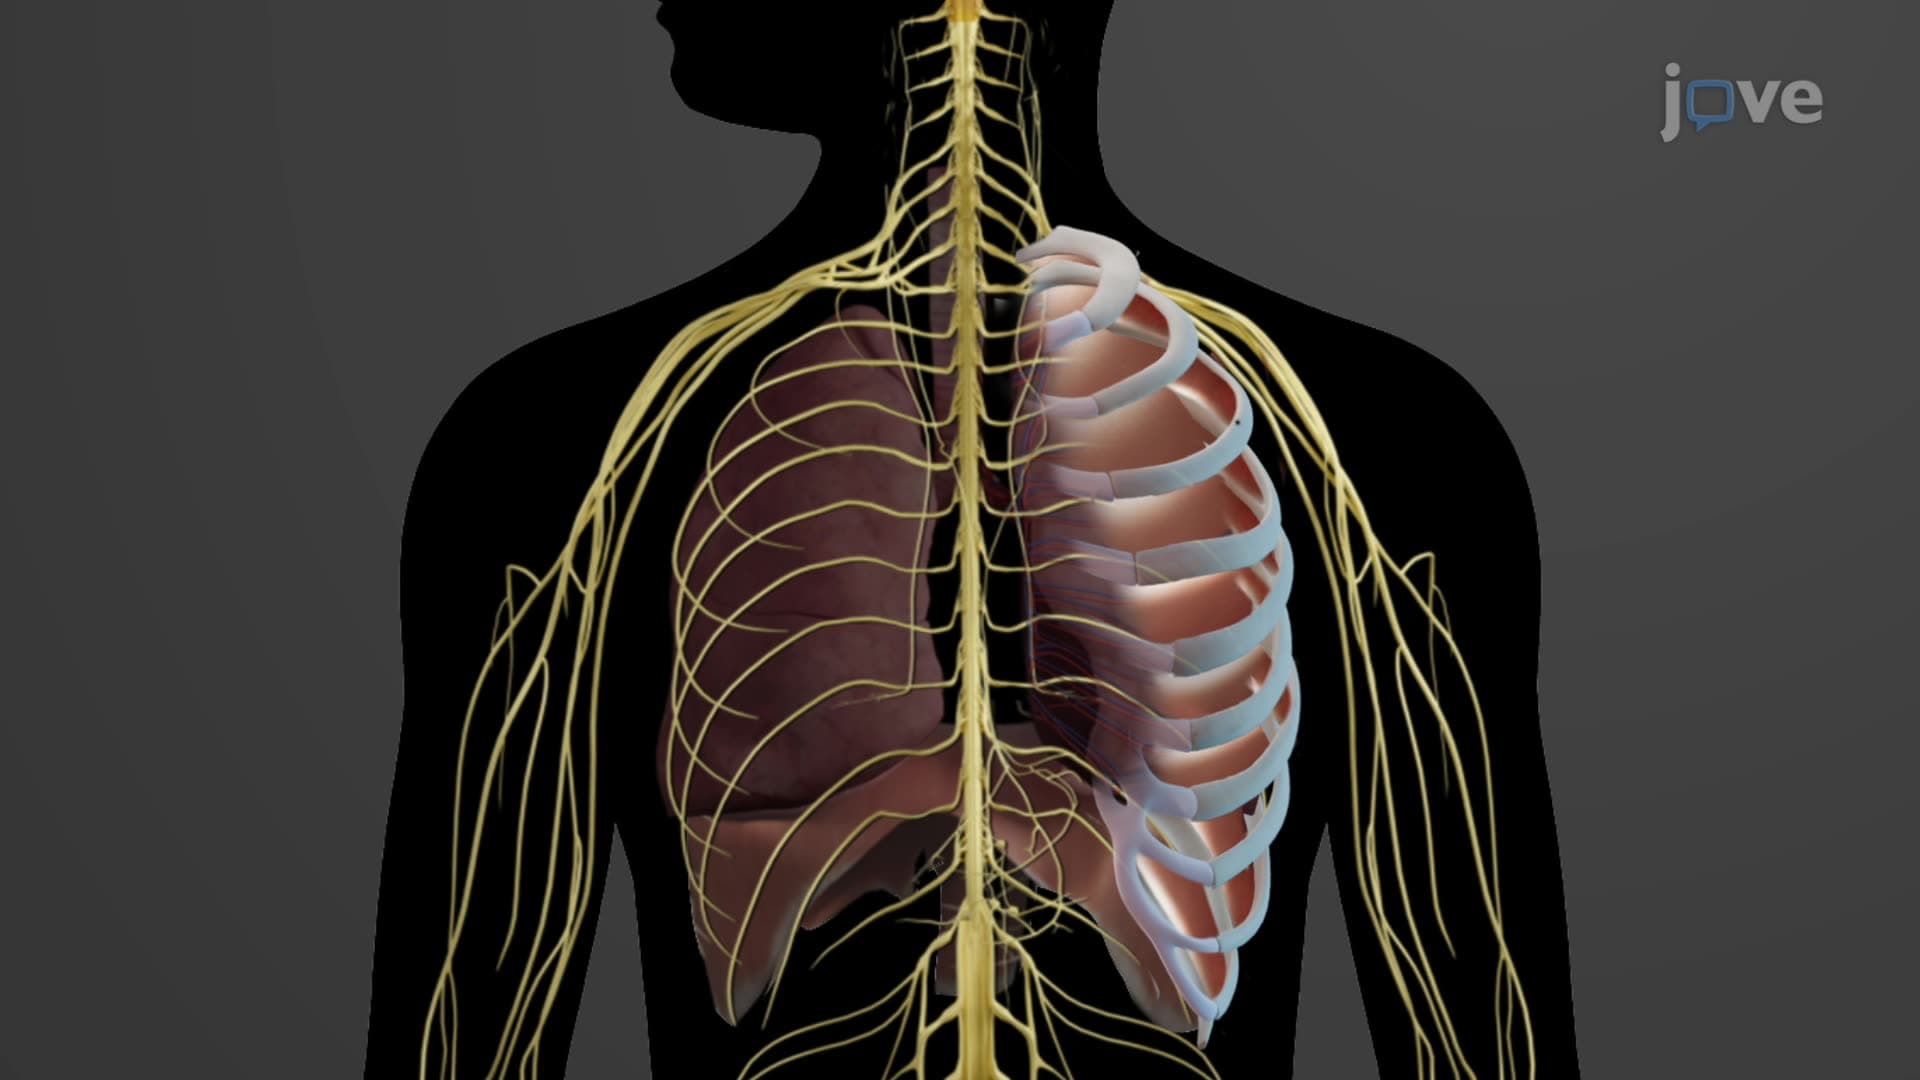
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...