Fractures in patients with primary hyperparathyroidism: nationwide follow-up study of 1201 patients
Related Experiment Video
Updated: Sep 27, 2026

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Peter Vestergaard1, Leif Mosekilde
1Department of Endocrinology and Metabolism C, Aarhus Amtssygehus, Tage Hansens Gade 2, Aarhus University Hospital, DK-8000, Aarhus C, Denmark. p-vest@post4.tele.dk

Abstract:
Parathyroid hormone (PTH) increases bone turnover and may thus increase fracture risk. As PTH secretion is increased in primary hyperparathyroidism, surgical cure may prevent fractures. We studied fracture risk before and after diagnosis in patients treated surgically and conservatively for primary hyperparathyroidism. All 1201 patients with newly diagnosed primary hyperparathyroidism (PHPT) between 1982 and 1996 in Denmark were identified through the Danish Hospital Discharge Register. Each patient was compared with three age- and gender-matched controls randomly drawn from the background population. Those who were treated surgically ( n = 841; mean age 58.6 +/- 14.6 years) were significantly younger than those who were not ( n = 360; 65.5 +/- 16.8 years; 2 p < 0.01); they had higher plasma ionized calcium (1.58 +/- 0.16 vs. 1.50 +/- 0.10 mmol/L; 2 p = 0.03) and tended to have lower lumbar spine bone mineral Z-scores (-0.72 +/- 1.35 vs. 0.05 +/- 1.05; 2 p = 0.06). Before diagnosis, fracture risk was elevated in both those who subsequently underwent surgery [incidence rate ratio (IRR) 1.45, 95% CI 1.05-1.99] and in those who did not (IRR 1.59, 95% CI 1.10-2.29). After diagnosis, no difference in fracture risk was present between surgically and nonsurgically treated patients. The risk of death was significantly lower in the operated patients than in those who did not have surgery (RR 0.58, 95% CI 0.47-0.73). No differences in fracture risk could be demonstrated between those who had and those who did not have surgery, taking age, gender, and previous fractures into account.
Related Concept Videos
 00:59
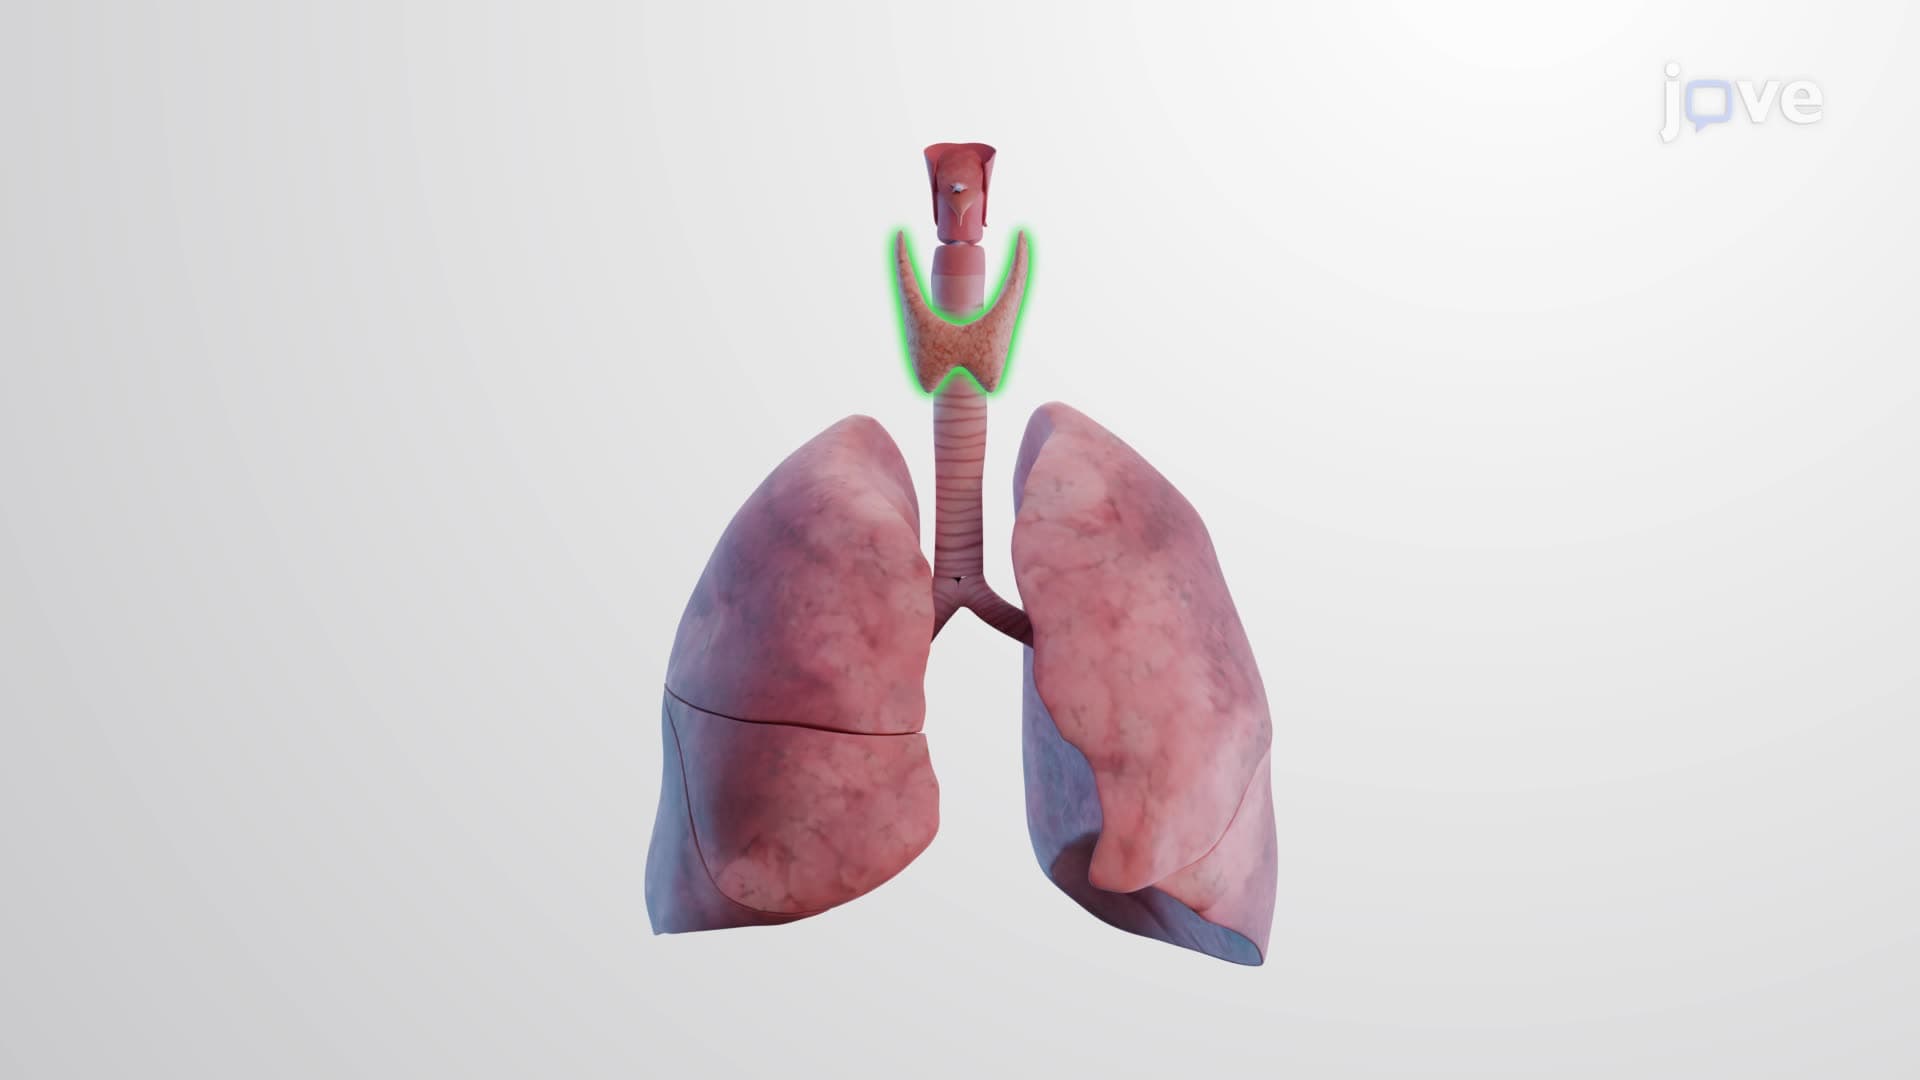
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:40
Bone Remodeling
 01:21
Skeleton and Calcium Homeostasis
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...