Related Experiment Video
Updated: Sep 27, 2026

In Vivo Functional Study of Disease-associated Rare Human Variants Using Drosophila
Published on: August 20, 2019
[Asphyxiating thoracic dysplasia (Jeune's Syndrome) in 15-years-old boy--6 years of observation]
Onufry Torbus1, Magdalena Jachimowicz, Henryk Grzybek
1Kliniki Gastroenterologii, Alergologii i Zaburzeń Rozwojowych Wieku Dzieciecego, Slaskiej Akademii Medycznej w Katowicach.

Abstract:
Asphyxiating thoracic dysplasia (Jeune's Syndrome) is a genetically determined dysplasia of thoracic bones usually leading to death during intrauterine life or in early childhood. Other osseous dysplasias as well as renal, hepatic and pancreatic failure may coexist with Jeune's syndrome. About one hundred cases of the syndrome were reported till now. The aim of the study is to describe the disease in a 15-year-old boy observed till the age of 20. The disease started in the second year of life and was manifested by limitation of thorax development and respiratory tract infections. At the age of 15 he was hospitalized due to dyspnoea. Short stature, weight deficiency and long, flat chest with significant stenothorax as well hypoxemia, pulmonary restriction and obstruction were found on admission. Moreover symmetrical decline in isoptic marker uptake without regional ventilatory disturbances were detected by ventilation--perfusion scintigraphy. The lack of bronchial epithelium and basement membrane thickening with present in and under the membrane numerous collagen fibres and fibroblasts were revealed in electron microscopy. As it is the first in literature description of bronchial mucosa electronogram in Jeune's syndrome we cannot have an unequivocal attitude to the described microscopic changes. The increase of body weight, height and some anthropometric parameters of the thorax as well as the maintenance of pulmonary restriction and obstruction, respiratory failure stagnation and circulatory failure deterioration were observed after 6 years of follow-up.

Related Concept Videos
 01:08
Pneumothorax II: Pathophysiology
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:10
Atelectasis II: Pathophysiology
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:15
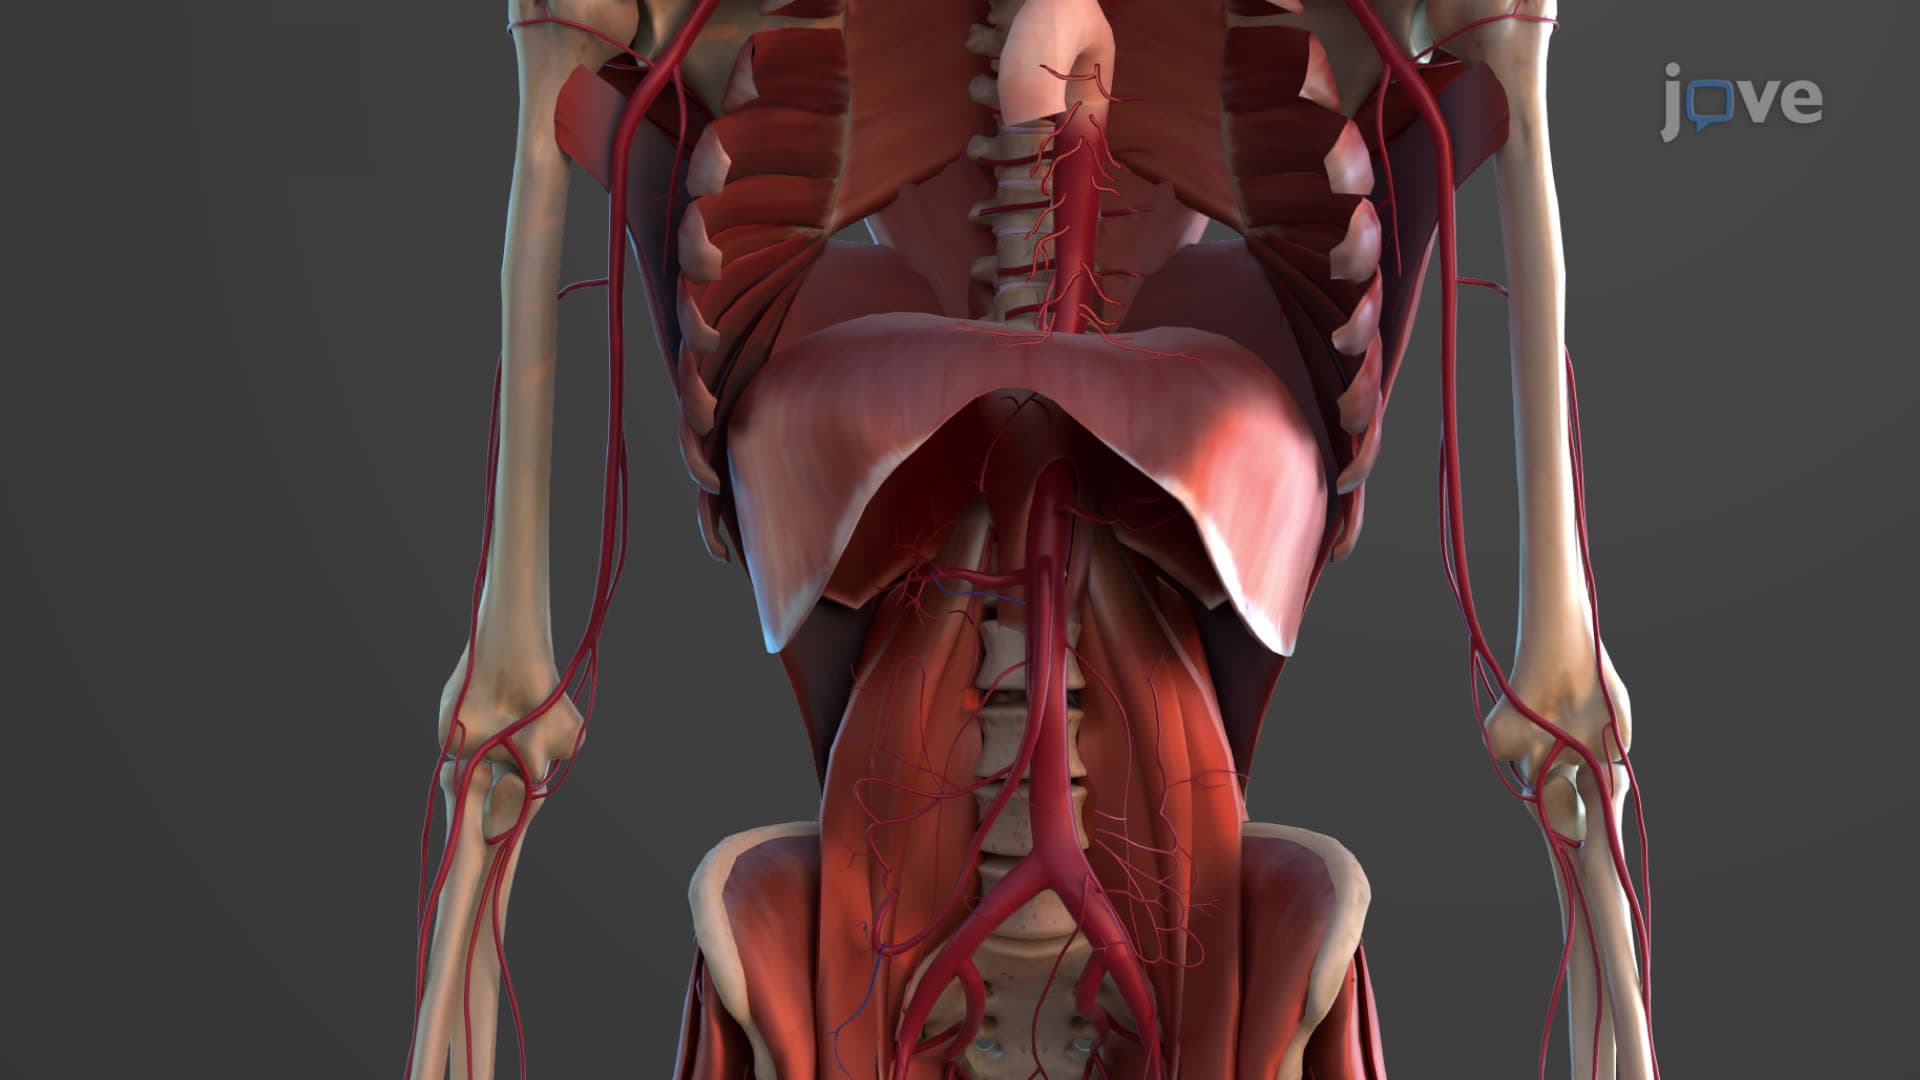
Thoracic Aorta