Related Experiment Video
Updated: Sep 27, 2026


Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Metaplasia of the duodenum shows a Helicobacter pylori-correlated differentiation into gastric-type protein
Jeroen H B Van De Bovenkamp1, Anita M Korteland-Van Male, Hans A Büller
1Laboratory of Pediatrics, Erasmus MC/Sophia Children's Hospital, Rotterdam, The Netherlands.

Abstract:
The origin of gastric metaplasia of the duodenum (GMD) remains enigmatic. We studied expression of mucins and trefoil peptides in GMD to gain insight into its phenotype and origin. We examined duodenal tissue of 95 patients (0 to 83 years old, 26 with gastric Helicobacter pylori infection) for the presence of GMD. Expression was examined immunohistochemically of secretory mucins (MUC2, MUC5AC, MUC5B, and MUC6), trefoil peptides (TFF1, TFF2, and TFF3), and sucrase-isomaltase (SI). GMD, found in 37 patients, correlated positively to gastric H. pylori infection, age, and villus atrophy. MUC2 and TFF3, expressed in normal goblet cells, were absent from 100% and 87% of GMD, respectively. GMD ubiquitously expressed MUC5AC, whereas MUC5AC expression in adjacent goblet cells was closely correlated with the extent of GMD. TFF1, TFF2, and MUC6 were found in 84%, 92%, and 65% of GMD, respectively. MUC5B was absent from epithelium and GMD. SI, expressed by villus enterocytes, was absent from GMD. Brunner's glands ubiquitously expressed MUC5B, MUC6, and TFF2. GMD was characterized by the expression of gastric-type proteins MUC5AC, MUC6, TFF1, and TFF2 and the absence of intestinal markers MUC2, TFF3, and SI. In terms of the location of metaplastic cells, our results suggest that epithelial cells migrating toward villus tips switch to gastric-type secretory cells. Positive correlation with infection suggests an inductive role H. pylori in the development of GMD.
Insights
Gastric metaplasia of the duodenum (GMD) involves cells switching to a gastric-like phenotype, potentially induced by Helicobacter pylori infection. This study identified key protein markers associated with GMD development.
Area of Science:
- Gastroenterology
- Cell Biology
- Pathology
Background:
- Gastric metaplasia of the duodenum (GMD) is a poorly understood condition.
- Understanding GMD's cellular origins and molecular phenotype is crucial for diagnosis and treatment.
Purpose of the Study:
- To investigate the expression of mucins and trefoil peptides in GMD.
- To elucidate the cellular phenotype and potential origin of GMD.
Main Methods:
- Immunohistochemical analysis of duodenal tissue from 95 patients.
- Examined expression of secretory mucins (MUC2, MUC5AC, MUC5B, MUC6), trefoil peptides (TFF1, TFF2, TFF3), and sucrase-isomaltase (SI).
- Correlated findings with Helicobacter pylori infection, age, and villus atrophy.
Main Results:
- GMD was present in 37 patients and correlated with H. pylori infection, age, and villus atrophy.
- GMD expressed gastric-type proteins (MUC5AC, MUC6, TFF1, TFF2) and lacked intestinal markers (MUC2, TFF3, SI).
- Results suggest migrating duodenal epithelial cells differentiate into gastric-type secretory cells, possibly influenced by H. pylori.
Conclusions:
- GMD exhibits a distinct phenotype characterized by gastric-associated protein expression.
- Helicobacter pylori infection may play an inductive role in the development of GMD.
- The study suggests a model of epithelial cell differentiation in GMD development.

Related Concept Videos
 01:26
Gastritis II: Pathophysiology
 01:24
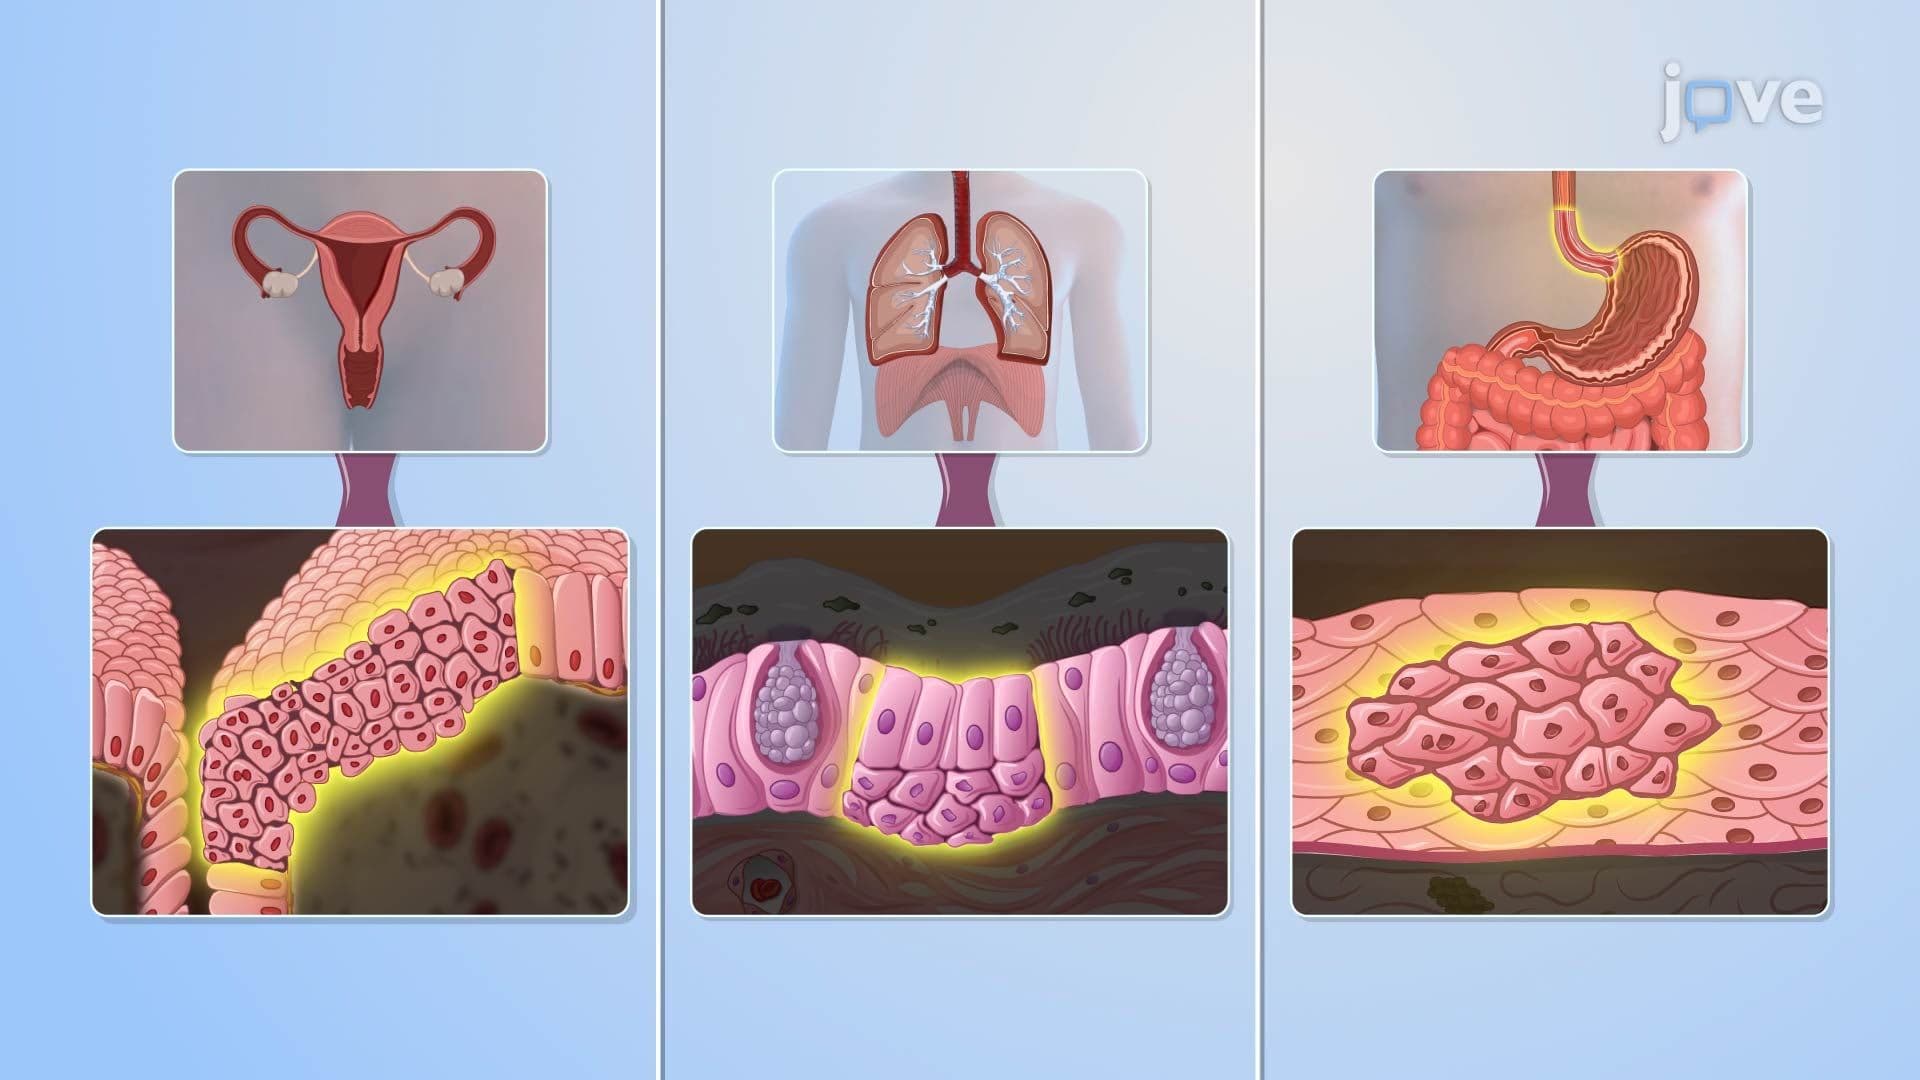
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:27
Peptic Ulcer
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...