Related Experiment Video
Updated: Aug 19, 2026
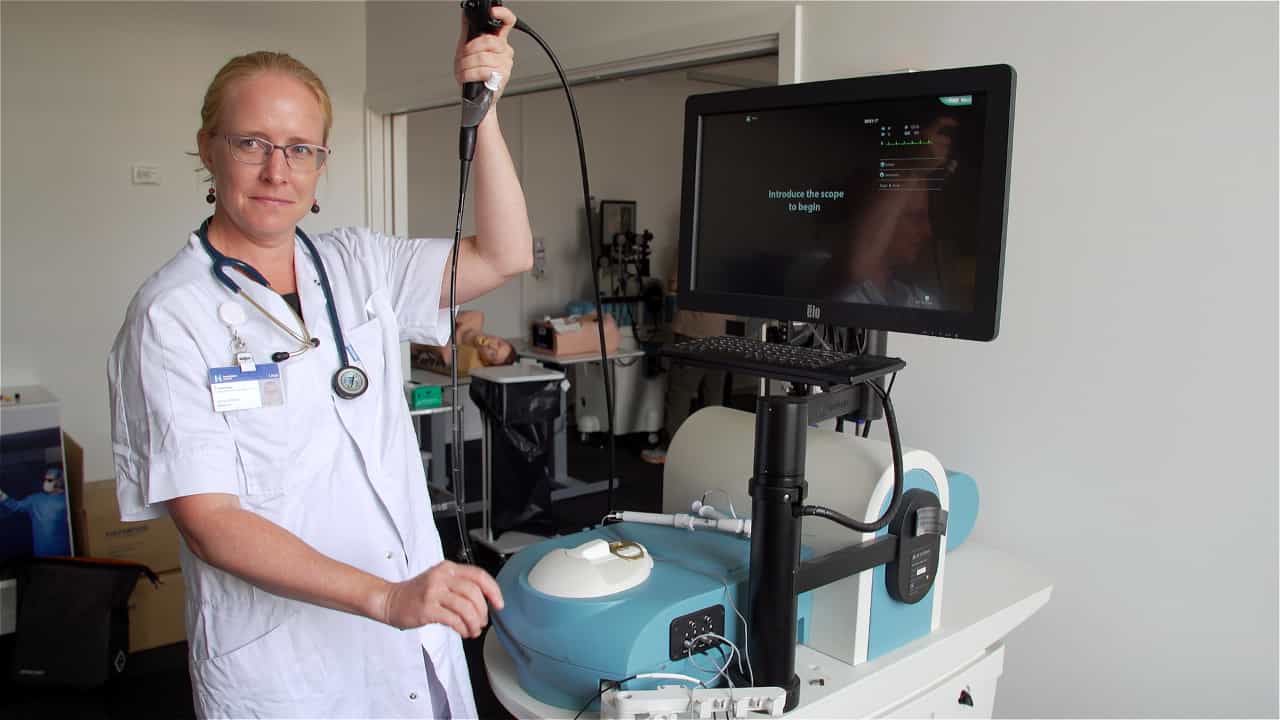

Systematic Endobronchial Ultrasound - The Six Landmarks Approach
Published on: August 11, 2023
Comparison of computed tomography and systematic lymph node dissection in determining TNM and stage in non-small cell
Thanos Sioris1, Ritva Järvenpää, Pekka Kuukasjärvi
1Department of Cardiothoracic Surgery, Tampere University Hospital, Tampere, Finland. sioris@saunalahti.fi

Objective:
To compare computed tomography (CT)-based clinical TNM and staging to surgical-pathological staging with systematic lymph node dissection in primary non-small cell lung cancer.
Methods:
The study included 49 non-small cell lung cancer patients that underwent lung resection and systematic lymph node dissection between 1997 and 2001. Preoperative clinical and CT findings were compared with surgical-pathological findings. Lymph nodes with a shortest diameter of over 1 cm on CT were considered abnormal, but did not contraindicate surgery. Patients with CT indicating an invasive T4 tumor, pleural carcinosis, or bulky N2 disease were excluded.
Results:
Sixty-five percent (32/49) had epidermoid carcinoma, and 25% (12/49) had adenocarcinoma. N2 metastases were found in 12% (6/49). The clinical T category was correct in 71% (35/49), and the N category in 55% (27/49). The sensitivity for detecting N2 disease was 67% (4/6), and the specificity was 81% (35/43). The positive predictive value for N2 disease was 33% (4/12), and the negative predictive value was 95% (35/37). Node-by-node agreement on N2 metastatic location was 17% (1/6). Skip N2 metastases without any N1 involvement were found in 4% (2/49), or 33% (2/6) of all N2 cases. The clinical stage was correct in 45% (22/49), and complete TNM agreement was 37% (18/49).
Conclusions:
The clinical TNM and staging based on CT are inaccurate. The sensitivity for detecting N2 disease is poor, especially on node-by node basis. Preoperative exclusion of N2 metastases is quite reliable, but a positive finding should always be verified. Systematic mediastinal lymph node dissection is necessary to detect N2 metastases inaccessible to cervical mediastinoscopy, and skip N2 metastases without N1 involvement.
More Related Videos
 07:13
Comparison of Predictive Performance of Three Lymph Node Staging Systems in Colorectal Signet Ring Cell Carcinoma Based on Machine Learning Model
Published on: April 18, 2025
 11:49
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
