Related Experiment Video
Updated: Sep 27, 2026

Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Bone mass at final height in precocious puberty after gonadotropin-releasing hormone agonist with and without calcium
Franco Antoniazzi1, Giorgio Zamboni, Francesco Bertoldo
1Pediatric Clinic, University of Verona I-37134, Italy. franco.antoniazzi@univr.it

Abstract:
The aim of our longitudinal study was to evaluate bone mass in girls affected by central precocious puberty (CPP) that have reached final height, treated with GnRH agonist triptorelin (GnRHa), with or without calcium supplementation. We studied 48 Caucasian females affected by CPP (age at diagnosis, 7.19 +/- 0.96 yr), randomly assigned to two groups: group A (n = 21) treated with GnRHa and group B (n = 27) treated with GnRHa plus calcium gluconolactate and carbonate (1 g calcium/day in two doses) for at least 2 yr. Auxological parameters (standing height, weight, body mass index) and bone mineral density (BMD) at the lumbar spine [L2-L4, anteroposterior (AP)-BMD; lateral BMD; volumetric (v)BMD)] by dual-energy x-ray absorptiometry were evaluated at the beginning [chronological age (CA), 7.29 +/- 0.91 yr; bone age (BA), 8.80 +/- 1.24 yr] and end of treatment (CA, 11.27 +/- 0.97 yr; BA, 12.35 +/- 0.43 yr) and at final height (CA, 16.17 +/- 1.9 yr; BA, 16.93 +/- 0.98 yr, in each case >15 yr). Total bone mineral content, total BMD, and fat percentage were evaluated at the end of the study period using dual-energy x-ray absorptiometry. Final height was significantly higher than predicted height at diagnosis (159.9 +/- 6.3 cm vs. 152.9 +/- 9.6 cm; P < 0.05). Body mass index and fat percentage were not statistically different from control values. Densitometric values at final evaluation in groups A and B together were lower than in controls, but the differences were not statistically significant. The vBMD was significantly higher in group B than in group A at the end of treatment period (0.213 +/- 0.022 g/cm(3) vs. 0.192 +/- 0.021 g/cm(3); P < 0.01) and at final evaluation (0.246 +/- 0.023 g/cm(3) vs. 0.227 +/- 0.024 g/cm(3); P < 0.05). The percentage change (Delta%) between the start and end of treatment period in AP-BMD and vBMD was significantly higher in group B than in group A (Delta% AP-BMD: 20.36% +/- 1.10% vs. 16.16% +/- 1.90%, P < 0.01; Delta% vBMD: 19.08% +/- 3.52% vs. 9.26% +/- 5.15%; P < 0.01) and also between the start of treatment and final evaluation (Delta% AP-BMD: 61.23% +/- 1.61% vs. 56.97% +/- 1.45%, P < 0.01; Delta% vBMD: 36.69% +/- 5.01% vs. 28.01% +/- 5.76%, P < 0.01). In all our females with CPP treated with GnRHa, bone densitometric parameters were in the normal range for age and sex. However, bone mass achievement seemed to be better preserved in the group of patients supplemented with calcium.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:21
Skeleton and Calcium Homeostasis
 01:40
Bone Remodeling
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:24
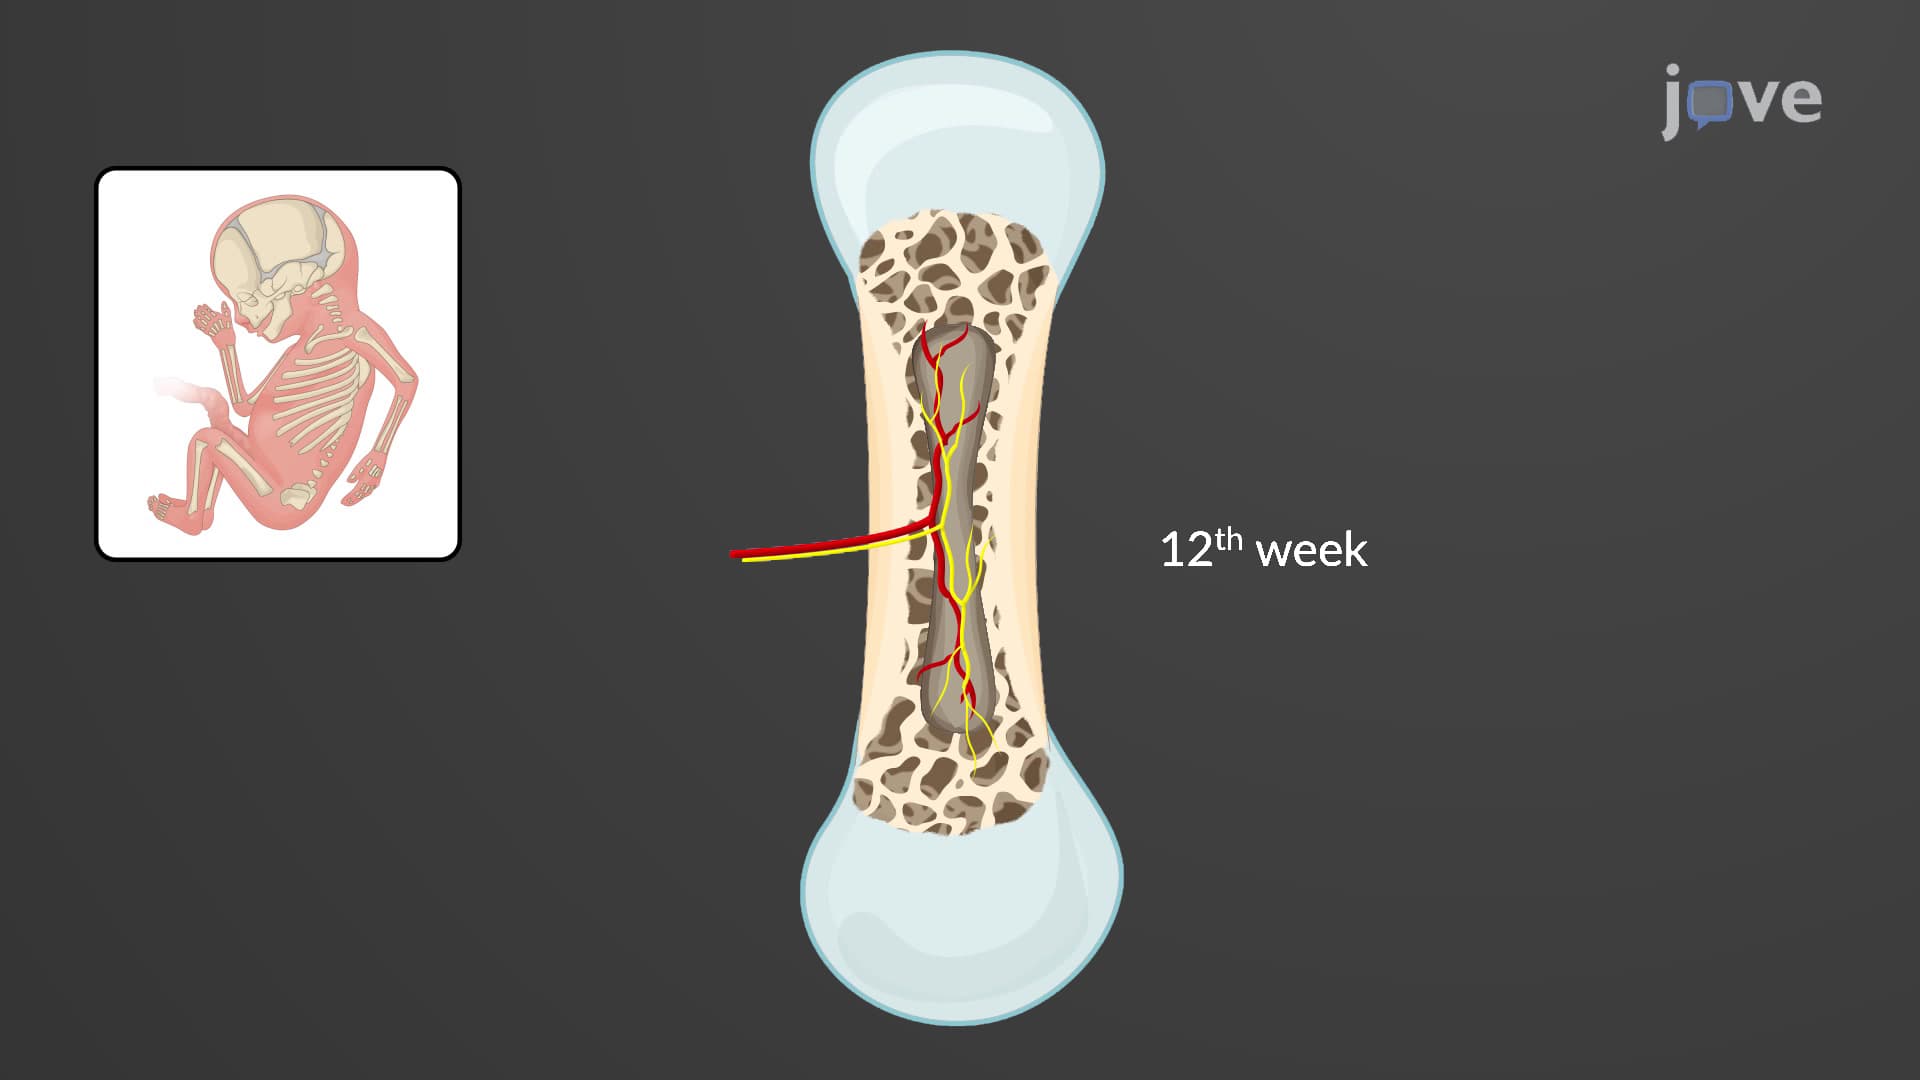
Bone Formation by Endochondral Ossification