Related Experiment Video
Updated: Sep 21, 2026


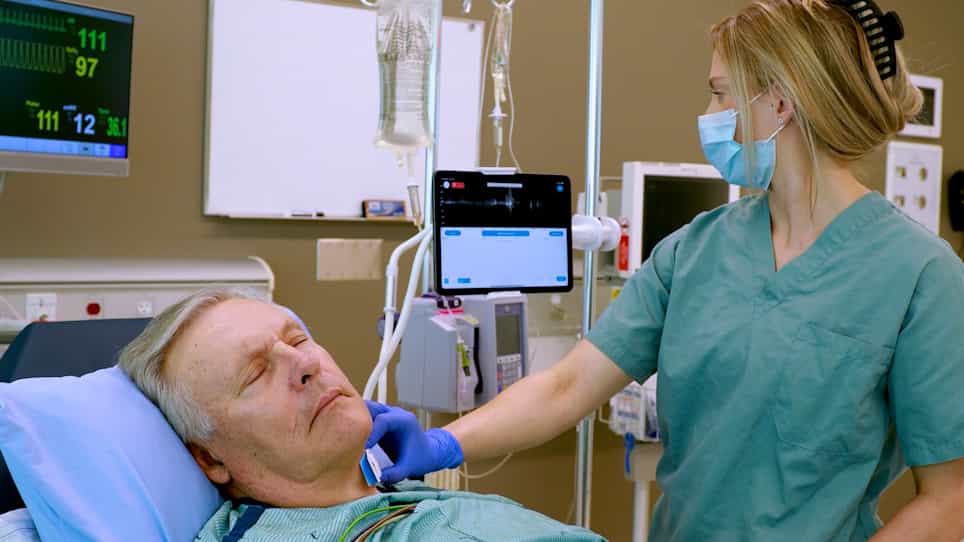
Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
[The influence of increased preload on left ventricular systolic function in infants with congenital heart disease]
Zbigniew Kordon1, Andrzej Rudziński, Marta Czubaj-Kowal
1Klinika Kardiologii Polsko-Amerykańskiego Instytutu Pediatrii Wydziału Lekarskiego Uniwersytetu Jagiellońskiego, Kraków.

Insights
In infants with congenital heart disease, the overloaded left ventricle maintains normal systolic function despite varying preload responses. Newborns show adrenergic responses, while older infants exhibit increased ventricular volume and mass.
Area of Science:
- Pediatric Cardiology
- Echocardiography
- Congenital Heart Disease
Background:
- Volume overload of the left ventricle (LV) is common in infants with congenital heart disease.
- Assessing LV systolic function in this population is crucial for management.
Purpose of the Study:
- To evaluate the systolic function of the volume-overloaded LV in infants diagnosed with congenital heart disease.
Main Methods:
- Echocardiographic assessment of LV parameters including end-diastolic volume (LVedv), end-diastolic muscle mass (LVedm), shortening fraction (FS), ejection fraction (EF), and fractional area changes (FAC).
- Hemodynamic parameters such as pulmonary blood flow (Qp), systemic blood flow (Qs), Qp/Qs ratio, and Qp-Qs (left-to-right shunt) were analyzed.
- Data were indexed for body surface area (BSA) and age, and statistical analysis was performed.
Main Results:
- Left ventricular end-diastolic volume (LVedv) increased with age, BSA, and Qp, but was only within normal limits for age in newborns.
- Left ventricular end-diastolic muscle mass (LVedm) correlated with BSA and exceeded age-appropriate limits in newborns.
- Despite hemodynamic variations and preload changes, LV systolic function indicators (FS, EF, FAC) remained diminished in only two patients and showed no significant correlation with age, BSA, or hemodynamics.
Conclusions:
- Infants exhibit distinct responses to increased LV preload, with newborns showing a predominant adrenergic response and older infants demonstrating increased end-diastolic volume and muscle mass.
- The systolic function of the overloaded left ventricle in infants with congenital heart disease is preserved, irrespective of age, BSA, or the severity of hemodynamic disturbances.
Unlabelled:
The aim of the study was to assess the systolic function of the volume overloaded left ventricle (LV) in infants with congenital heart disease.
Material:
Seventy five consecutive patients (36 males, 39 females) with following breakdown were examined: 14 (18.7%) newborns, 24 (32%) infants under 3 months, 16 (21.3%) between 4 and 6, and 21 (28%) infants above 6 months of age. VSD was recognized in 60 (80%), PDA--6(8%), DORV--7 (9.3%), and CT (type I) in 2 (2.7%) of the patients.
Methods:
Based on ECHO studies LV end diastolic volume (LVedv), end diastolic muscle mass (LVedm), LV shortening fraction (FS), ejection fraction (EF), LV fractional area changes (FAC), and heart rate (HR) versus pulmonary blood flow (Qp), which reflected the LV preload systemic blood flow (Qs), Qp/Qs, Qp-Qs (left-to-right shunt) and indexed for body surface area (BSA) and age, were assessed by statistical analysis.
Results:
With a gradual increase of BSA with age (cc = 0.82, p < 0.001), a significant decrease in Qp-Qs (cc = -0.27, p = 0.035) and Qp/Qs (cc = -0.31, p = 0.013) were noted. Qp for the whole group ranged from 3.3 to 21.7 l/min/m2 (m = 8.9, x = 9.7, SD = 4.1), significantly increased with the rise of Qp-Qs (cc = 0.9, p < 0.0001) and influenced the increment of Qp/Qs (cc = 0.59, p < 0.001). Qs for the whole group ranged from 2.1 to 11.7 l/min/m2 (m = 4.3, x = 4.6, SD = 1.7) correlating with the rise of Qs (cc = 0.45, p < 0.001), and being lower than 2.5 l/min/m2 in only 5 (6.7%) patients but in only 5 (6.7%) patients (all newborns). The heart rate gradually decreased with age (r = -0.26, p = 0.04), from mean 145/min in newborns to 123/min in infants over 6 months, and with BSA (cc = -0.34, p = 0.006). Heart rate also correlated well with Qp (cc = 0.31, p = 0.014). The increase of LVedv was related to age (cc = 0.37, p = 0.003), BSA (cc = 0.43, p = 0.0004) and Qp (cc = 0.33, p = 0.009). However, only in newborns was the mean LVedv within normal limits for age. LVedm only correlated with BSA (cc = 0.26, p = 0.04), except in newborns where its mean values exceeded the upper limits for age in other subgroups of patients. LV systolic function indicators (FS, EF, FAC) were diminished in only 2 cases and did not correlate either with age, BSA, nor with hemodynamic parameters.
Conclusions:
1. The reactions to increased preload of the systemic ventricle in children below one year of age were different. In newborns, the adrenergic response predominated, while infants manifested increased end-diastolic volume and left ventricular muscle mass. 2. The systolic function of the overloaded left ventricle in infants was normal regardless of age, body surface area and intensity of hemodynamic disturbances.

Related Concept Videos
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:29
Heart Failure II: Pathophysiology