Related Experiment Video
Updated: Sep 21, 2026
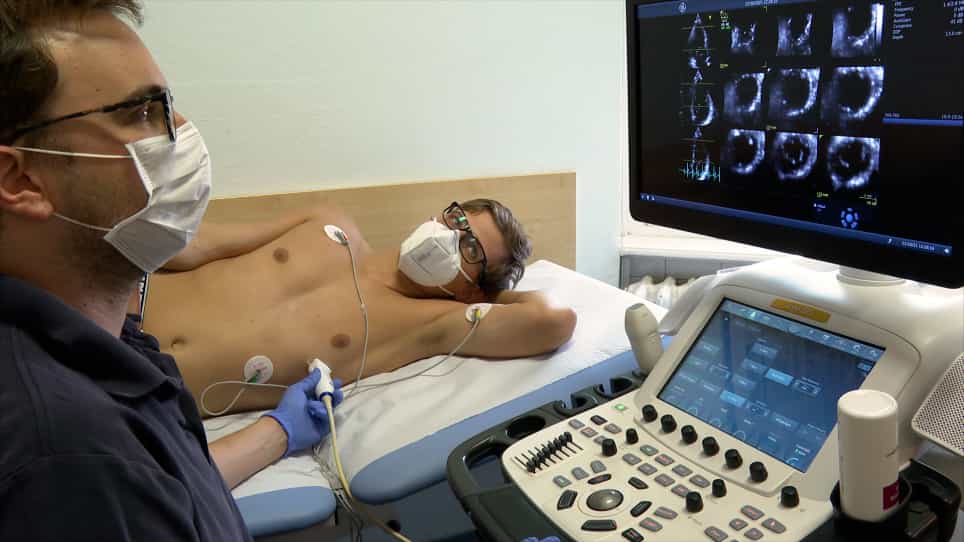
Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Unusual left ventricular dilatation without functional or biochemical impairment in normotensive extremely overweight
Norimitsu Kinoshita1, Shohei Onishi, Satoshi Yamamoto
1Sports Medicine Research Center, Keio University, Yokohama, Japan. kinoshit@hc.cc.keio.ac.jp <kinoshit@hc.cc.keio.ac.jp>

Abstract:
To explore the physiologic limit of left ventricular (LV) enlargement, we performed echocardiography and air displacement plethysmography to respectively assess LV dimension and function and the body composition of Japanese professional sumo wrestlers. After excluding subjects with cardiovascular disease, hypertension, plasma brain natriuretic peptide (BNP) > or =17.9 pg/ml, diabetes mellitus, or asthma, 331 subjects (mean +/- SD age, 21.6 +/- 3.7 years; height 179.2 +/- 5.3 cm; weight 1,17.9 +/- 21.5 kg; percent fat, 29.6 +/- 6.6%) were analyzed. LV end-diastolic dimension averaged 58.4 +/- 3.7 mm and was within the generally regarded normal limit (< or =54 mm) in 14.5% of subjects, but was > or =60 mm in 41.1% of subjects. LV septal and posterior wall thicknesses were 10.3 +/- 0.9 and 10.2 +/- 0.9 mm, respectively. Peak E- and A-wave velocities, E/A ratio, LV fractional shortening, and BNP were 96 +/- 16 and 51 +/- 13 cm/s, 2.0 +/- 0.7, 33.5 +/- 4.5%, and 3.1 +/- 3.7 pg/ml, respectively. LV end-diastolic dimension was not correlated with these indexes of LV function or with plasma BNP levels, but was significantly correlated with height, weight, body surface area, fat-free mass, and fat mass. These results show that among very large, highly trained, professional athletes, LV end-diastolic dimension frequently exceeds the traditionally accepted upper limit of normal for the general population. This increase in LV end-diastolic dimension may thus represent an extreme example of the physiologic adaptation of the athlete's heart.

Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Heart Failure II: Pathophysiology
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy