Related Experiment Video
Updated: Sep 27, 2026


Legionella pneumophila Outer Membrane Vesicles: Isolation and Analysis of Their Pro-inflammatory Potential on Macrophages
Published on: February 22, 2017
Chlamydia pneumoniae survival in macrophages is regulated by free Ca2+ dependent reactive nitrogen and oxygen species
1Department of Health Sciences, University of Wisconsin, Milwaukee, WI 53211, USA. aazenabo@uwm.edu

Objectives:
Despite an efficient macrophage immune capability, Chlamydia pneumoniae infects host cells and causes chronic diseases. To gain better insights into C. pneumoniae survival mechanisms in macrophages, its growth in regular RAW-264.7 cells (nitric oxide sufficient NO (+)) and RAW-264.7 cells (nitric oxide insufficient NO (-)) were studied.
Methods:
Role of Ca(2+), NO and reactive oxygen species (ROS) during C. pneumoniae infection in macrophages were determined.
Results:
RAW-264.7 NO (-) cells supported significantly Chlamydia growth, showing an upregulation of ROS, superoxide dismutase (SOD) and catalase activities as compared with RAW-264.7 NO (+) cell. Ascorbic acid, inducible nitric oxide synthase inhibitor and glutathione significantly prompted Chlamydia inclusion formation. Cytosolic Ca(2+) had regulatory effect on organism growth, NO generation, SOD and catalase activities in both cell types.
Conclusions:
These findings suggest that minimal Ca(2+) signaling in macrophages at early stages of infection, NO and ROS release have modulatory effects onC. pneumoniae survival, onset of persistence and chronicity, processes which are needed for the initiation of diseases in which C. pneumoniae has been implicated as a possible etiologic agent.
Insights
Chlamydia pneumoniae survives better in macrophages lacking nitric oxide (NO), with increased reactive oxygen species (ROS). Calcium (Ca2+) and NO signaling influence bacterial growth and persistence, impacting chronic disease development.
Area of Science:
- Immunology
- Microbiology
- Cell Biology
Background:
- Chlamydia pneumoniae infections can lead to chronic diseases despite macrophage immune defenses.
- Understanding C. pneumoniae survival mechanisms within host macrophages is crucial for disease intervention.
Purpose of the Study:
- To investigate the growth of C. pneumoniae in macrophages with varying nitric oxide (NO) levels.
- To determine the roles of calcium (Ca2+), NO, and reactive oxygen species (ROS) in C. pneumoniae infection.
Main Methods:
- Culturing RAW-264.7 macrophages with sufficient (NO+) and insufficient (NO-) nitric oxide.
- Assessing C. pneumoniae growth and inclusion formation.
- Measuring ROS, superoxide dismutase (SOD), and catalase activities.
- Evaluating the effects of ascorbic acid, an NO synthase inhibitor, and glutathione.
Main Results:
- RAW-264.7 NO(-) cells showed significantly higher C. pneumoniae growth, increased ROS, SOD, and catalase activity compared to NO(+) cells.
- Ascorbic acid, an inducible nitric oxide synthase inhibitor, and glutathione enhanced Chlamydia inclusion formation.
- Cytosolic Ca(2+) regulated bacterial growth, NO generation, and antioxidant enzyme activities in both cell types.
Conclusions:
- Minimal Ca(2+) signaling, alongside NO and ROS release, modulates C. pneumoniae survival, persistence, and chronicity in macrophages.
- These factors are critical for initiating diseases where C. pneumoniae is a suspected etiological agent.

Related Concept Videos
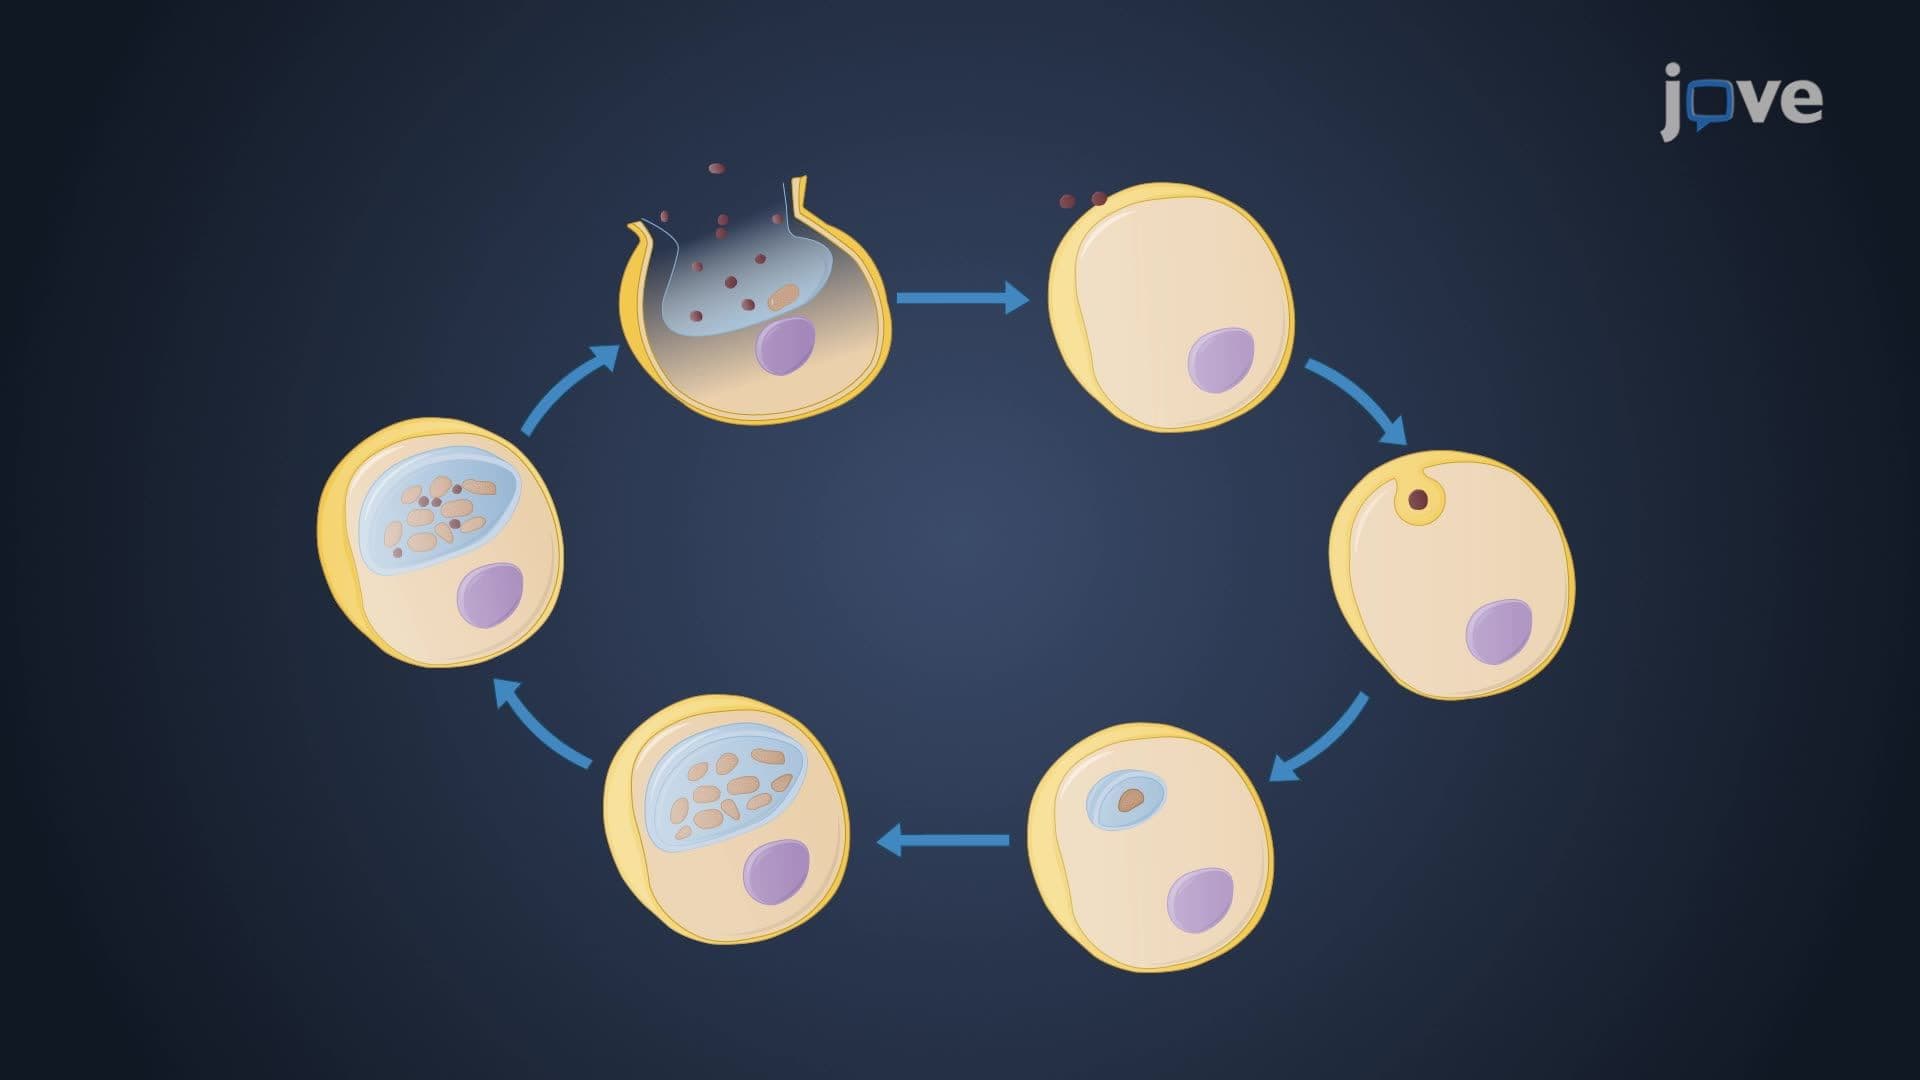 01:29
Bacterial Phylum Chlamydiae
 01:14
Atypical Pneumonia
 01:27
Immune Surveillance by NK Cells and Phagocytes
Natural Killer Cells: The Fast Responders
NK cells are large granular lymphocytes found in the blood and lymphatic system. These...
 01:29
Pneumonia II: Pathophysiology
 01:29
Pneumonia I: Introduction