Related Experiment Video
Updated: Sep 26, 2026


Pulsed Wave Doppler Assessment of Diastolic Dysfunction in the ZSF-1 Rat Model of Pulmonary Hypertension Due to Left Heart Disease
Published on: May 22, 2026
Clinical and echocardiographic features in patients with dilated cardiomyopathy: wave intensity and diastolic
Henryk Siniawski1, Axel Unbehaun, Hans Lehmkuhl
1Department of Cardiothoracic and Vascular Surgery, Deutsches Herzzentrum Berlin, Augustenburger Platz 1, 13353 Germany. siniawski@dhzb.de

Insights
Wave intensity (WI) analysis reveals distinct arterial system stiffening in dilated cardiomyopathy (DCM) patients, indicating reduced tolerance to orthostatic stress compared to heart transplant recipients and healthy individuals.
Area of Science:
- Cardiology
- Biomedical Engineering
- Physiology
Background:
- Dilated cardiomyopathy (DCM) pathophysiology and patient stratification remain challenging.
- Current prognostic markers for end-stage DCM are insufficient.
- Wave intensity (WI) offers a novel approach to assess cardiovascular function.
Purpose of the Study:
- To investigate the utility of wave intensity (WI) in evaluating patients with end-stage dilated cardiomyopathy (DCM).
- To compare WI parameters in DCM patients, heart transplant (HTx) recipients, and healthy volunteers.
- To assess the impact of postural changes (supine to upright) on cardiovascular parameters using WI.
Main Methods:
- Noninvasive real-time wave intensity (WI) measurements were performed on the right common carotid artery.
- Doppler mitral filling and noninvasive cardiac output were recorded.
- Participants included ambulatory DCM patients, HTx recipients, and healthy volunteers, studied in both supine and upright positions.
Main Results:
- DCM patients exhibited significantly lower WI peaks in the supine position, which increased in the upright position, unlike HTx patients and controls.
- Cardiac output was reduced in DCM patients when changing from supine to upright posture.
- Diastolic dysfunction, indicated by restrictive mitral filling patterns, was more pronounced in DCM patients upon assuming the upright position.
Conclusions:
- Wave intensity (WI) effectively differentiates DCM patients from HTx recipients and healthy individuals.
- DCM patients show impaired arterial elasticity and autonomic vascular control, contributing to orthostatic intolerance.
- WI provides valuable insights into both systolic and mechanoelastic properties of the arterial system and myocardium.
Objective:
The pathophysiology of dilated cardiomyopathy is not fully understood, and among the problems which need to be solved is the lack of an adequate classification which could help to predict the survival of patients in the end stage of the disease. The criteria used today, based on clinical symptoms and invasive and noninvasive assessment of the heart function, are far from satisfactory. Estimation of maximal oxygen consumption is a time-consuming procedure and more descriptive of the global cardiopulmonary situation rather than being able to provide specific answers. Loading conditions seem to be the key to the problem. The state of vascular resistance and systolic performance of the heart can be defined using the method known as "wave intensity" (WI), which represents the relation of the pressure estimated noninvasively to the flow inside the vessel. This study presents first experiences with wave intensity in the Deutsches Herzzentrum Berlin in patients suffering from end-stage dilated cardiomyopathy (DCM), a group of ambulatory patients after heart transplantation (HTx), and in healthy volunteers. The study was performed in supine and upright position.
Patients:
Out of 182 patients waiting for transplantation, thirty-one (17%) ambulatory patients suffering from dilated cardiomyopathy comprised the first group (Group A). Their mean age was 53 +/- 14.2 years and 16 were men. Maximum MV O2 was 16.1 (+/- 4.57) mg/kg. Mean PAP and capillary pressure were 26.1 (+/- 11.91) and 16.8 (+/- 9.81) mmHg, respectively. Cardiac index was 2.3 (+/- 0.58) l/min/m2. The second group (Group B) consisted of 56 ambulatory patients after heart transplantation (mean 3.8 +/- 3.35 years) who did not suffer from rejection. Their mean age was 49.9 +/- 15.18 years and 47 were men. Normal sinus rhythm was an inclusion criterion for the study. The control group consisted of 15 healthy volunteers with a mean age of 35 +/- 12 years and 2 were men.
Method:
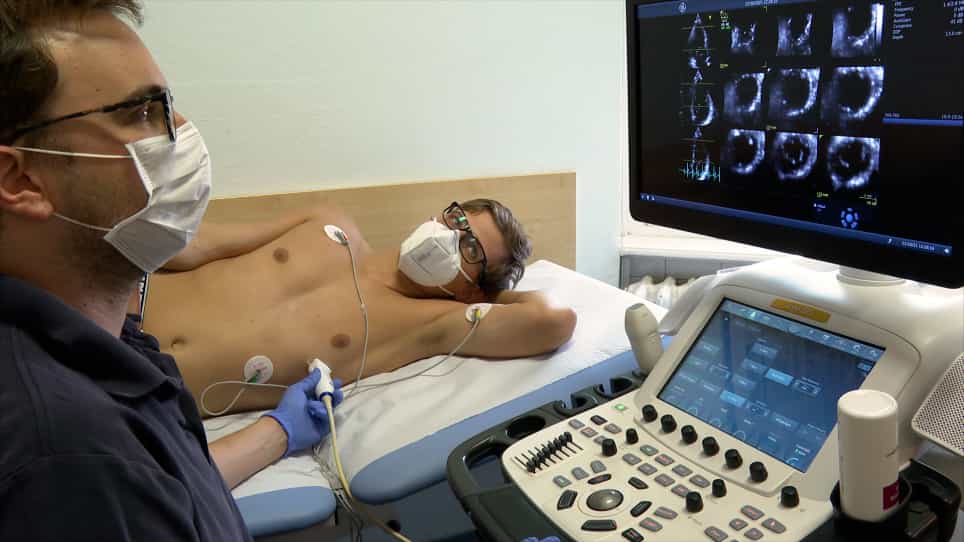
Real time wave intensity (WI), Doppler mitral filling and noninvasive cardiac output were recorded and analyzed using the ALOKA 5.500 machine equipped with a wave intensity real time analysis system. Wave intensity was defined noninvasively as the product of delta U and delta V where delta U was vascular diameter change (representing pressure change) and delta V was the velocity inside the vessel. The measurements were done in real time during constant short time intervals. The WI data were obtained from the right common carotid artery in all patients.
Results:
The 1st and 2nd WI peaks were significantly lower in supine position in the DCM group and rose significantly in upright position when compared to the data from patients after transplantation and volunteers. The values of 1st and 2nd peak in supine position in DCM were respectively 4606 (+/- 2283) and 1483 (+/- 675) and upright 1st and 2nd were 5405 (+/- 3432) and 202 (+/- 1726). The values of 1st and 2nd peak in the Tx group were significantly higher at rest: 10,743 (+/- 6290) and 3195 (+/- 2127), respectively, and were not significantly lower after upright maneuver. The highest values of both products (1st and 2nd) of WI were observed in healthy volunteers 14,632 (+/- 6293) and 14,153 (+/- 6969) and were significantly higher when compared to the DCM group (p = 0.01). Cardiac output in the supine position was significantly lower in the DCM patients and fell after position was changed to erect. In the Tx group, cardiac output was normal at rest and didn't fall significantly in the upright position. The DCM and transplant patients showed abnormalities in diastolic heart function after changing to the erect position (restrictive pattern of mitral filling); however, more severe filling abnormalities were found in the DCM patients.
Conclusion:
Our results demonstrate that patients suffering from DCM are less tolerant of arthostatic stress than patients after heart transplantation. The slight increase in wave intensity in the DCM group hints at stronger activation of autonomic vascular control, leading to a stiffening in the arterial system, which possibly protects the central nervous system from hypoperfusion. The diastolic alteration was probably the response of diseased myocardium to increased requirements of the peripheral system after changing the position of the patients. This diastolic alteration, although less pronounced, was noticed in the transplanted group, but was not seen in healthy individuals. Therefore, we conclude that wave intensity is a new, powerful marker providing information not only about left ventricular systolic function but also about mechanoelastic properties of the arterial system integrated with elastic properties of the myocardium.

Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests