Related Experiment Video
Updated: Aug 19, 2026


Synthesis and Characterization of an Aspirin-fumarate Prodrug that Inhibits NFκB Activity and Breast Cancer Stem Cells
Published on: January 18, 2017
[Antiaggregation: aspirin]
A Eichenberger1, L Pontiggia, J H Beer
1Departement Innere Medizin, Kantonsspital Baden. adrian.eichenberger@ksb.ch

Insights
Aspirin effectively prevents secondary cardiovascular events, with a number needed to treat of 25. However, it carries risks of bleeding, necessitating careful consideration for primary prevention in high-risk individuals.
Area of Science:
- Cardiology
- Pharmacology
- Preventive Medicine
Background:
- Randomized trials confirm aspirin's efficacy as an antiplatelet agent.
- Aspirin is established for secondary prevention of cardiovascular events.
Purpose of the Study:
- To evaluate the benefits and risks of aspirin therapy.
- To define guidelines for aspirin use in primary and secondary prevention.
Main Methods:
- Review of randomized controlled trials on aspirin.
- Analysis of number needed to treat (NNT) and number needed to harm (NNH) data.
- Assessment of risk stratification models for primary prevention.
Main Results:
- NNT for vascular event prevention is approximately 25.
- NNH for cerebral bleeding is about 1,000; for severe extracerebral bleeding, 100-200.
- Primary prevention is recommended for high-risk patients (≥1-1.5% annual risk).
Conclusions:
- Aspirin is a valuable tool for secondary cardiovascular event prevention.
- Risk-benefit assessment is crucial, especially for primary prevention.
- Further discussion on mechanisms, interactions, and aspirin resistance is warranted.
Abstract:
Many randomized trials have shown aspirin as an effective antiplatelet drug for the secondary prevention of cardiovascular events. The NNT (number needed to treat) to prevent 1 vascular event is about 25. The NNH (number needed to harm) inducing one cerebral bleeding is about 1'000, to provoke one severe extracerebral bleeding about 100-200. The primary prevention can be recommended only for high risk patients for cardiovascular events (annual risk of 1-1.5% or more), calculated on the basis of the Framingham data, the Sheffield tables or in analysis of U.S. Preventive Services Task Force. The mechanisms of action, interactions and the "aspirin-resistance" are briefly discussed.
More Related Videos
 09:13
Turbidimetry on Human Washed Platelets: The Effect of the Pannexin1-inhibitor Brilliant Blue FCF on Collagen-induced Aggregation
Published on: April 6, 2017
 08:56
Synthesis of a Borylated Ibuprofen Derivative Through Suzuki Cross-Coupling and Alkene Boracarboxylation Reactions
Published on: November 30, 2022
Related Concept Videos
 01:30
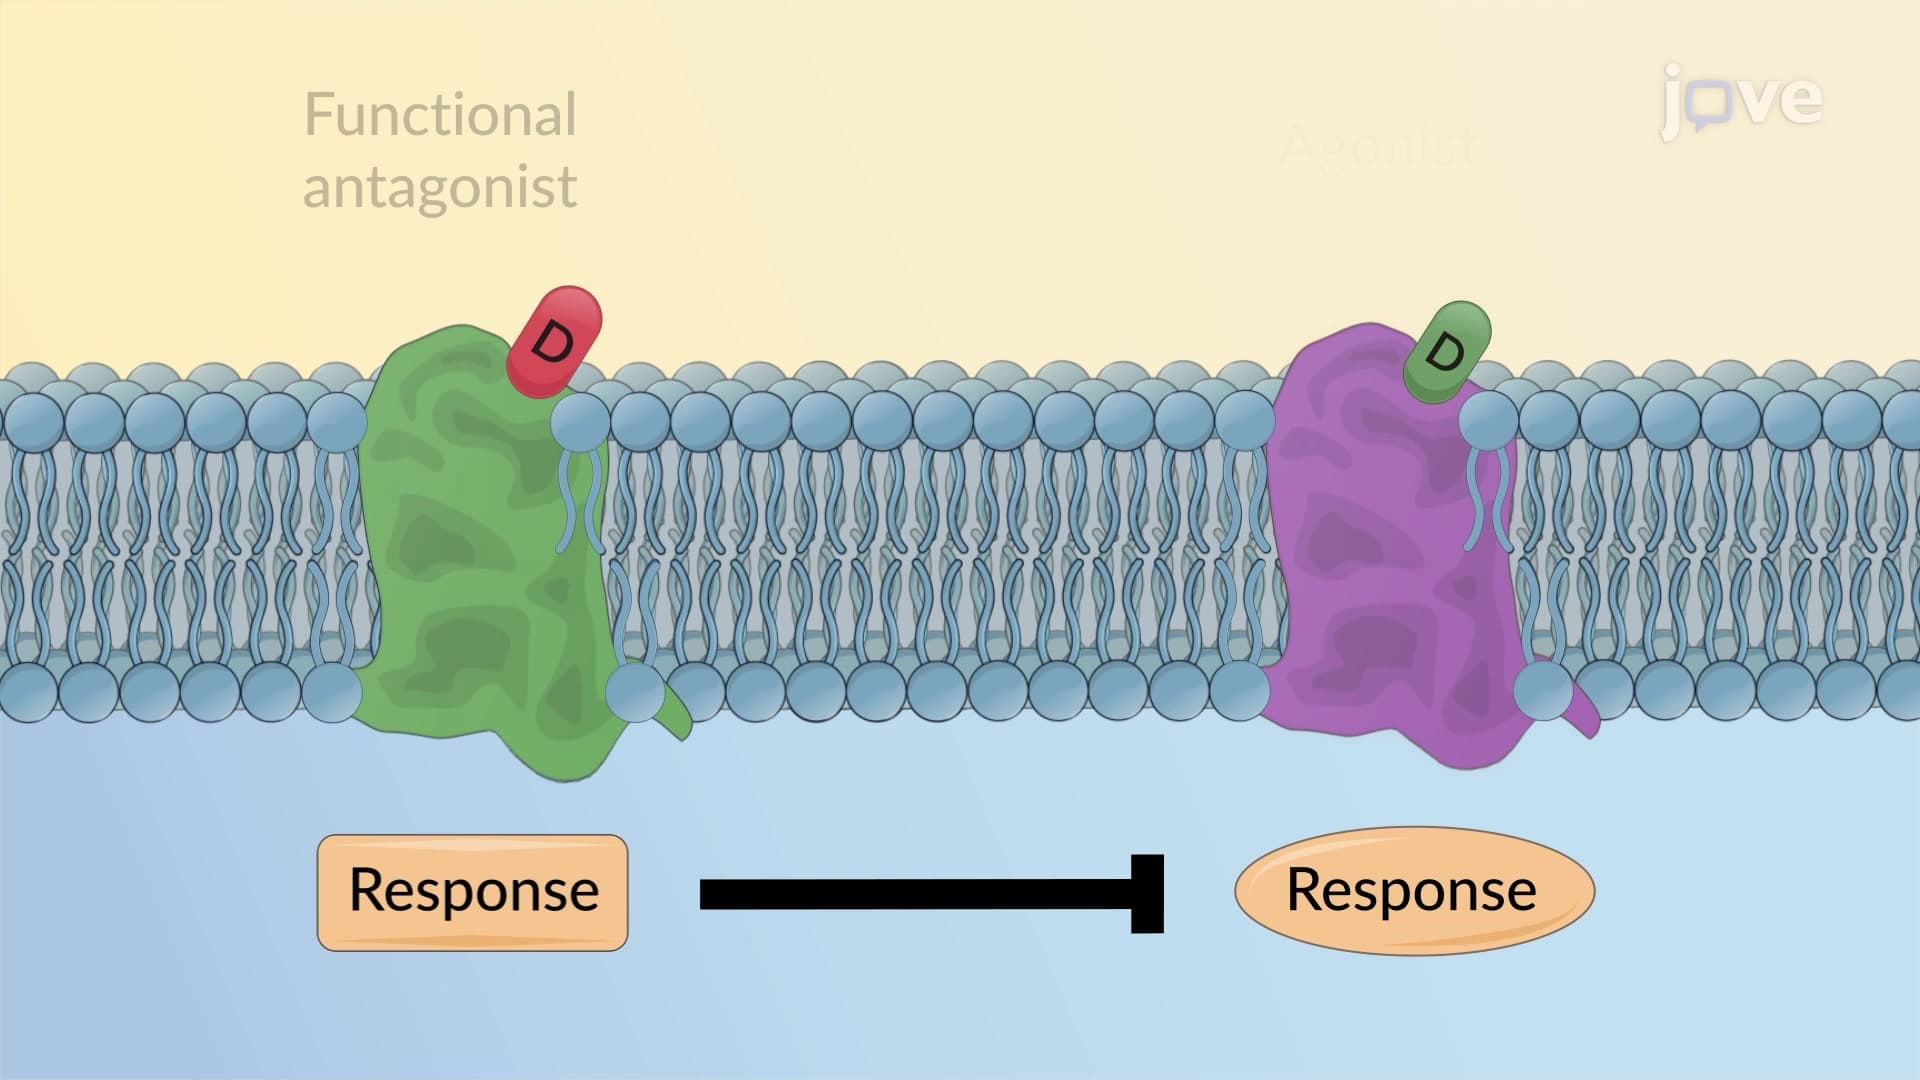
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:28
Acid Suppressive Drugs for Peptic Ulcer Disease: Histamine H2-Receptor Antagonists