Related Experiment Video
Updated: Sep 26, 2026

Quantifying Acute Changes in Renal Sympathetic Nerve Activity in Response to Central Nervous System Manipulations in Anesthetized Rats
Published on: September 11, 2018
A fluctuation in adrenocepter- and muscarinic receptor-mediated blood pressure responses in acute hyperthyroid rats
Hideo Honda1, Takeshi Iwata, Takuya Mochizuki
1Department of Pharmacology, Tokyo University of Pharmacy and Life Science, 1432-1 Horinouchi, Hachioji, Japan. hhonda@ps.toyaku.ac.jp

Abstract:
Hyperthyroidism was induced by daily subcutaneous injections of L-thyroxine (T(4), 0.5 mg/kg/day) for 3 days, 1 week, or 2 weeks to study whether there is a fluctuation in adrenoceptor- and muscarinic receptor-mediated blood pressure responses at a hyperthyroid stage. T(4) treatment for 3 days or 1 week significantly suppressed the pressor response induced by norepinephrine (NE). The depressor responses induced by isoprenaline or acetylcholine (ACh) were increased by T(4) treatment for only 3 days. The pressor response induced by N(G)-nitro-L-arginine (L-NA) was increased by T(4) treatment for only 3 days. Results suggest that adrenoceptor- and muscarinic receptor-mediated blood pressure responses fluctuate in hyperthyroidism caused by T(4) in rats, that the basal nitric oxide (NO) production and/or release are increased in hyperthyroid rats at an early stage of the disease.

Related Concept Videos
 01:27
Hyperthyroidism II: Pathophysiology
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction while...
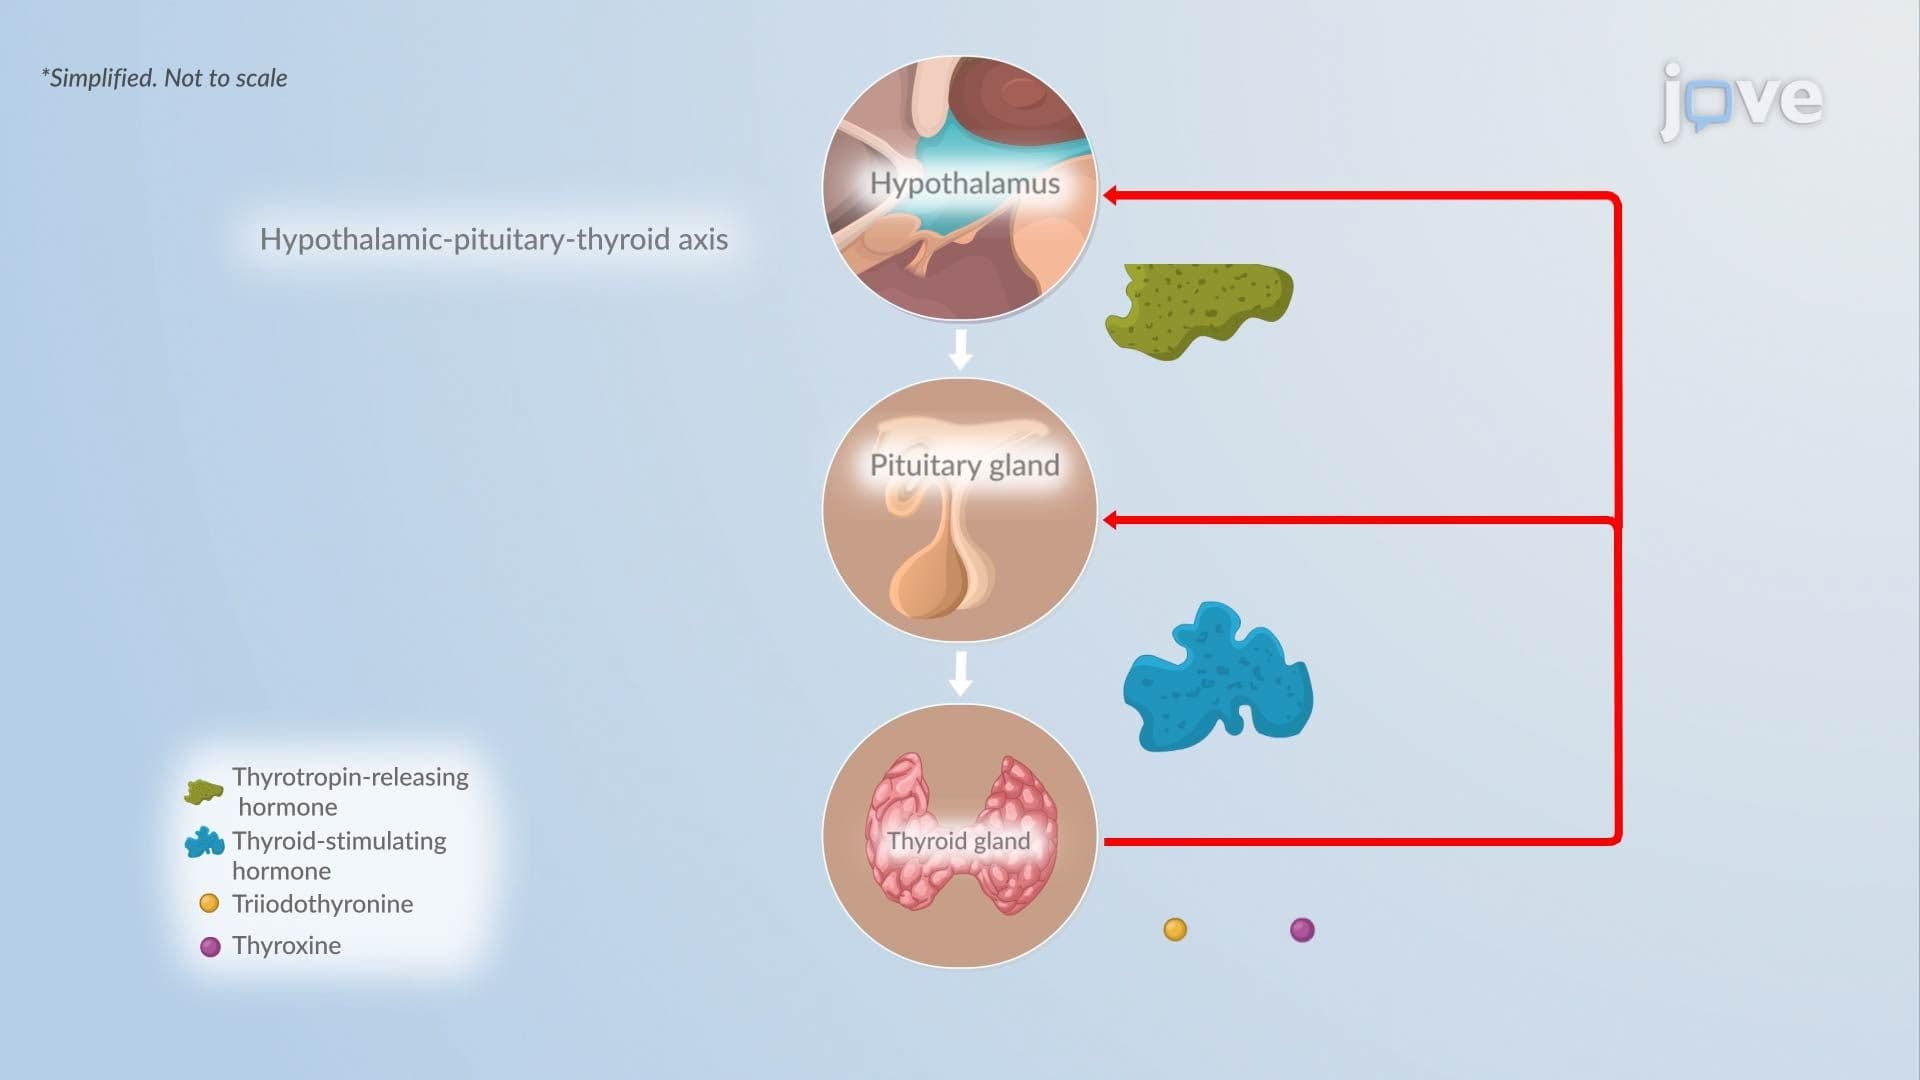 01:25
Hyperthyroidism I: Introduction
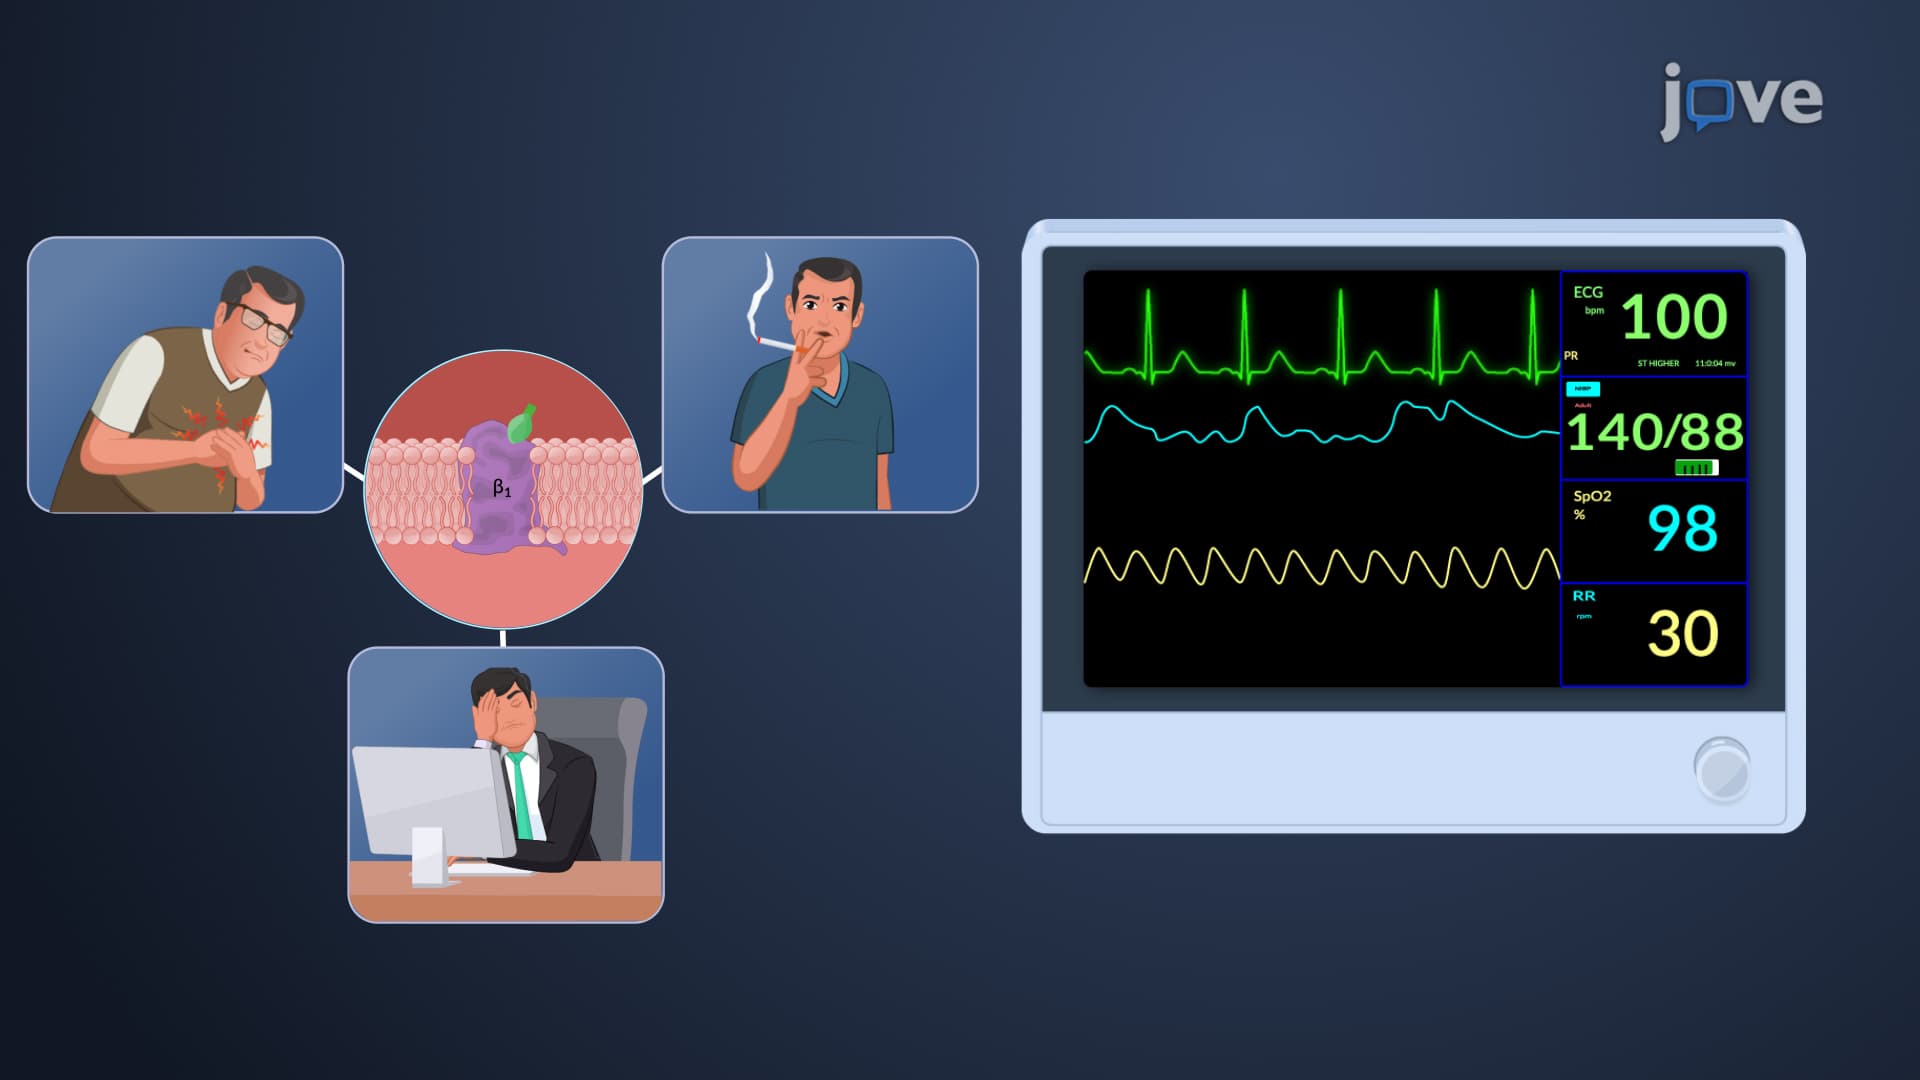 01:17
Antihypertensive Drugs: Action of β1 Blockers
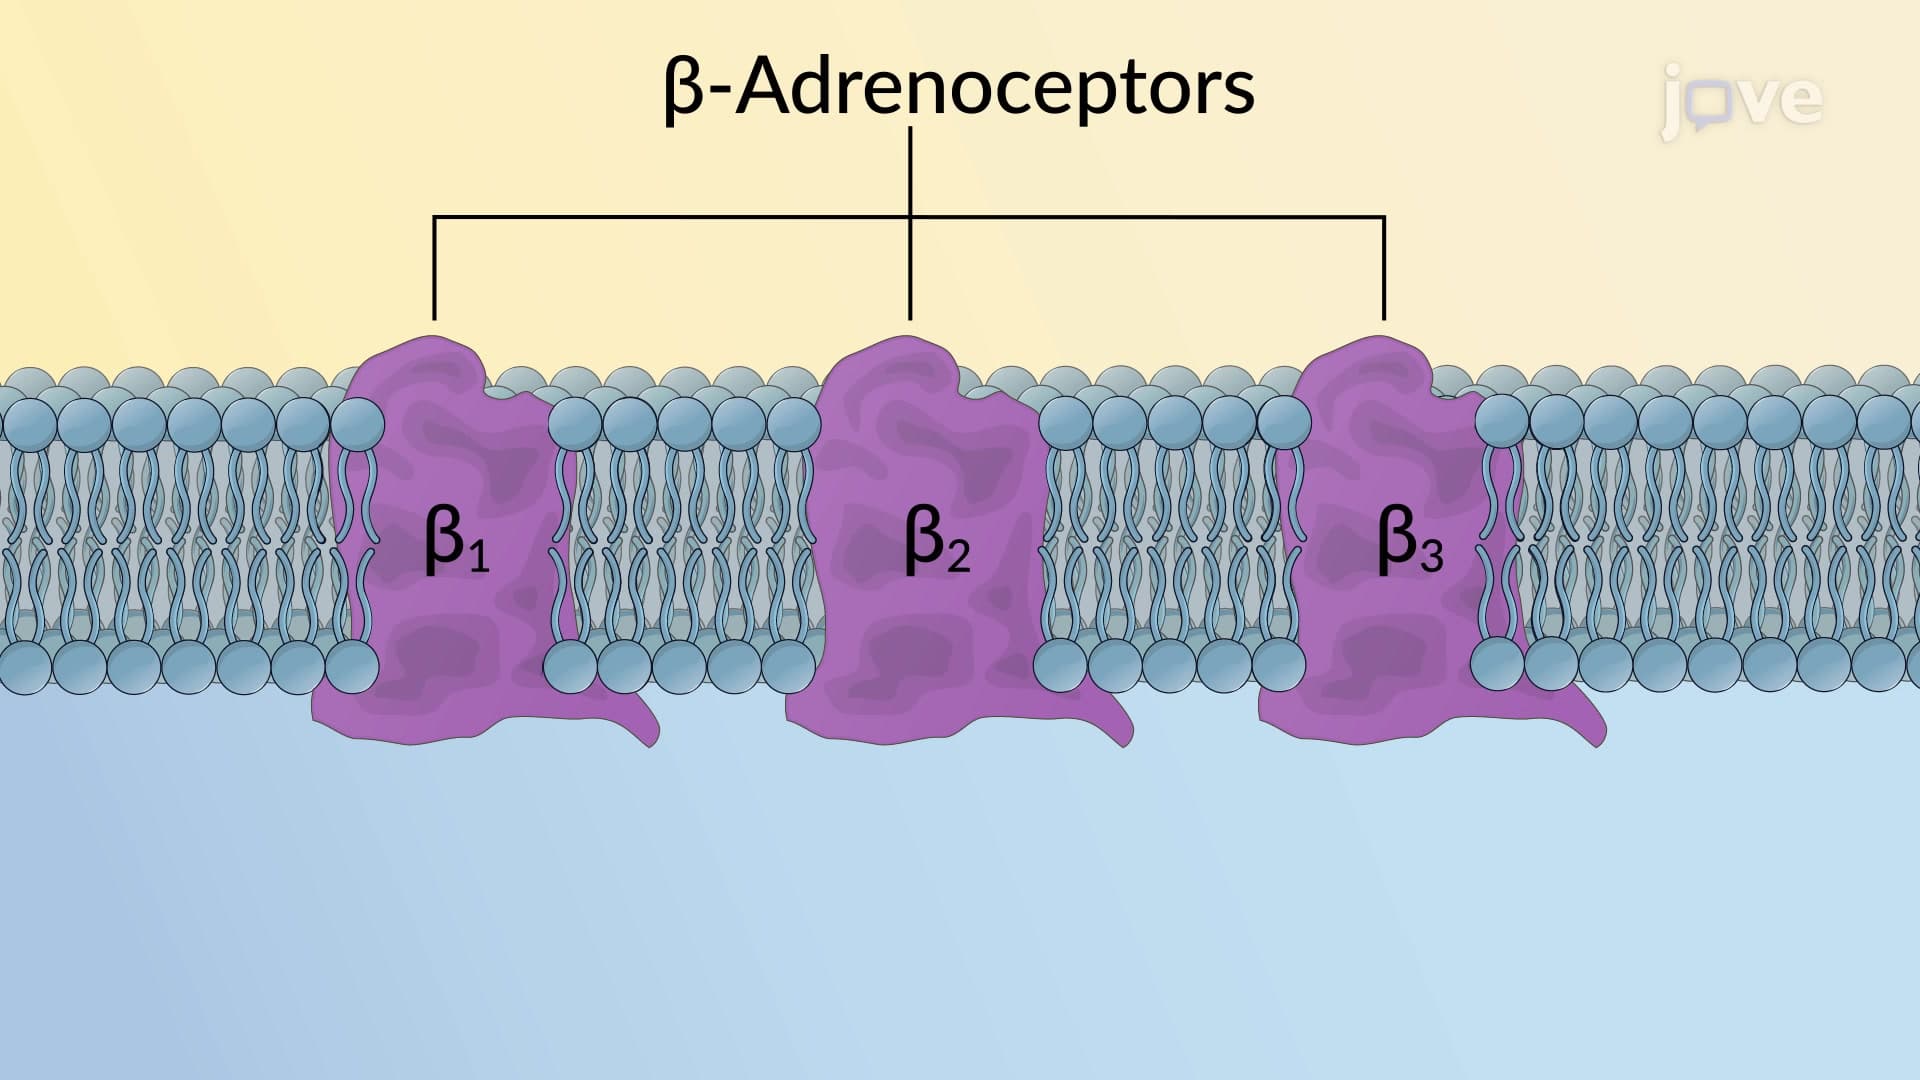 01:26
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
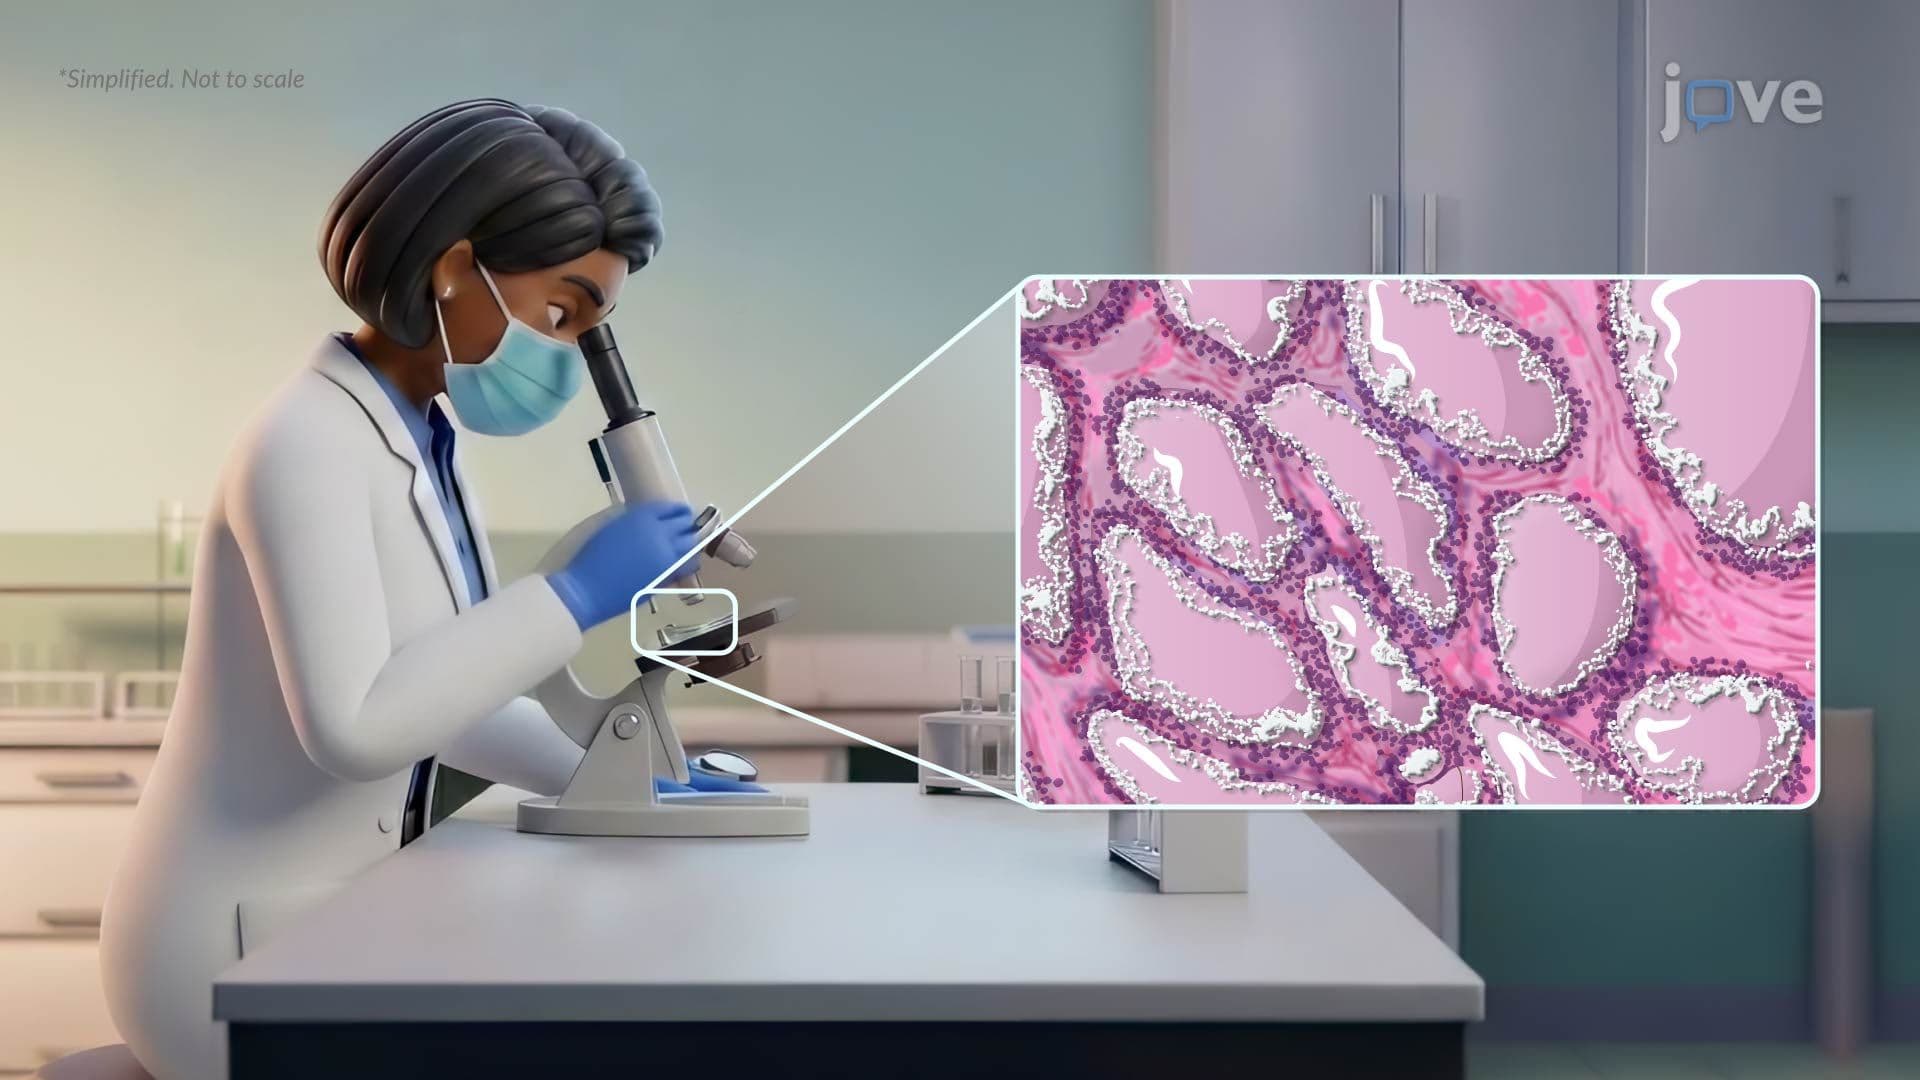 01:24
Graves Disease II: Pathophysiology