Related Experiment Video
Updated: Sep 26, 2026


Subcutaneous Infection of Methicillin Resistant Staphylococcus Aureus (MRSA)
Published on: February 9, 2011
Bacterial aetiology of non-resolving otitis media in South African children
Robin E Huebner1, Avril D Wasas, Maurice Hockman
1Respiratory and Meningeal Pathogens Research Unit of the MRC/NHLS/University of the Witwatersrand, Johannesburg, South Africa.

Insights
In South Africa, nearly all Streptococcus pneumoniae causing persistent childhood otitis media are antibiotic-resistant. This highlights critical challenges in treating pediatric ear infections, especially in young children with recurrent symptoms.
Area of Science:
- Otolaryngology
- Pediatric Infectious Diseases
- Microbiology
Background:
- Non-resolving otitis media in children poses diagnostic challenges, particularly regarding causative pathogens and antibiotic resistance.
- Limited data exists on etiology and antimicrobial susceptibility in children receiving private healthcare in South Africa.
- High antibiotic access in South Africa's private sector may correlate with resistance patterns seen in developed nations.
Purpose of the Study:
- To determine the bacterial etiology of non-resolving acute otitis media in South African children receiving private care.
- To analyze antimicrobial resistance patterns and serotypes of isolated bacterial pathogens.
- To investigate factors associated with pathogen isolation and specific bacterial types.
Main Methods:
- Middle-ear fluid samples were collected from 173 children (2 months to 7 years) with non-resolving acute otitis media.
- Cultures were performed on samples from children with persistent pain or fever within 14 days of symptom onset.
- Bacterial isolates were identified, and antimicrobial susceptibility testing and serotyping were conducted for Streptococcus pneumoniae.
Main Results:
- Bacteria were isolated from 27% of children, with Streptococcus pneumoniae being the most common pathogen (35 isolates).
- 94% of isolated pneumococci exhibited antimicrobial resistance, with high rates against penicillin (86%), trimethoprim-sulfamethoxazole (54%), erythromycin (69%), and clindamycin (57%).
- Common pneumococcal serotypes included 19F, 14, 23F, 6B, and 19A. Younger age, fever, and prior otitis media episodes were associated with pneumococcal isolation.
Conclusions:
- The study reveals a high prevalence of antibiotic-resistant Streptococcus pneumoniae in non-resolving pediatric otitis media within South Africa's private healthcare sector.
- These findings underscore the need for careful antibiotic selection and consideration of resistance patterns in treating recalcitrant childhood ear infections.
- Young children with persistent symptoms and a history of otitis media are particularly vulnerable to resistant pneumococcal infections.
Abstract:
Little is known of the aetiology, serotypes or susceptibility of the pathogens causing non-resolving otitis media in children receiving care from specialists in private practice in developed or in developing countries. Increased access to antibiotics in the community amongst children receiving such private care in South Africa may be anticipated to lead to levels of resistance similar to those found in countries with similar models of private practice, such as the United States. This study was conducted to determine the aetiology of non-resolving otitis media in South African children receiving private care and to determine the antimicrobial resistance patterns and serotypes of the bacterial isolates. Middle-ear fluid was cultured from 173 children aged two months to seven years with non-resolving acute otitis media accompanied by persistent pain or fever who were referred to otorhinolaryngologists for drainage of middle-ear fluid within 14 days of the start of symptoms. While 92 per cent of the children had recently received antibiotics and 54 per cent were currently receiving them, bacteria were isolated from 47 children (27 per cent). Streptococcus pneumoniae was the most common pathogen (35), followed by Haemophilus influenzae (nine), Staphylococcus aureus (six), Moraxella catarrhalis (two), Streptococcus pyogenes (two) and Pseudomonas aeruginosa (one). Two isolates were identified in each of eight children. Antimicrobial resistance to one or more antibiotics was found in 33/35 (94 per cent) of the pneumococci isolated, with resistance to penicillin in 86 per cent, resistance to trimethoprim-sulfamethoxazole in 54 per cent and to erythromycin and clindamycin in 69 per cent and 57 per cent, respectively. The pneumococcal serotypes found were 19F (28 per cent), 14 (26 per cent), 23F (23 per cent), 6B (nine per cent), 19A (87 per cent), and four (three per cent). Children with a bacterial pathogen isolated were younger (mean age of 17 months) than children from whom no bacteria were isolated (mean age of 23 months; p = 0.03). Isolation of a pneumococcus was also significantly associated with younger age (mean = 16 months versus 22 months, p = 0.03), the presence of fever (OR = 2.15, p = 0.049), and having one or more prior episodes of otitis media within the six months before tympanocentesis (OR = 7.72, p = 0.03). Almost all pneumococci isolated from non-resolving acute otitis media in this community are antibiotic-resistant and should be considered especially in young children who have failed previous therapy and who have non-resolving pain or fever.
Related Concept Videos
 01:25
Mechanism of Antibiotic Resistance in MRSA
 01:29
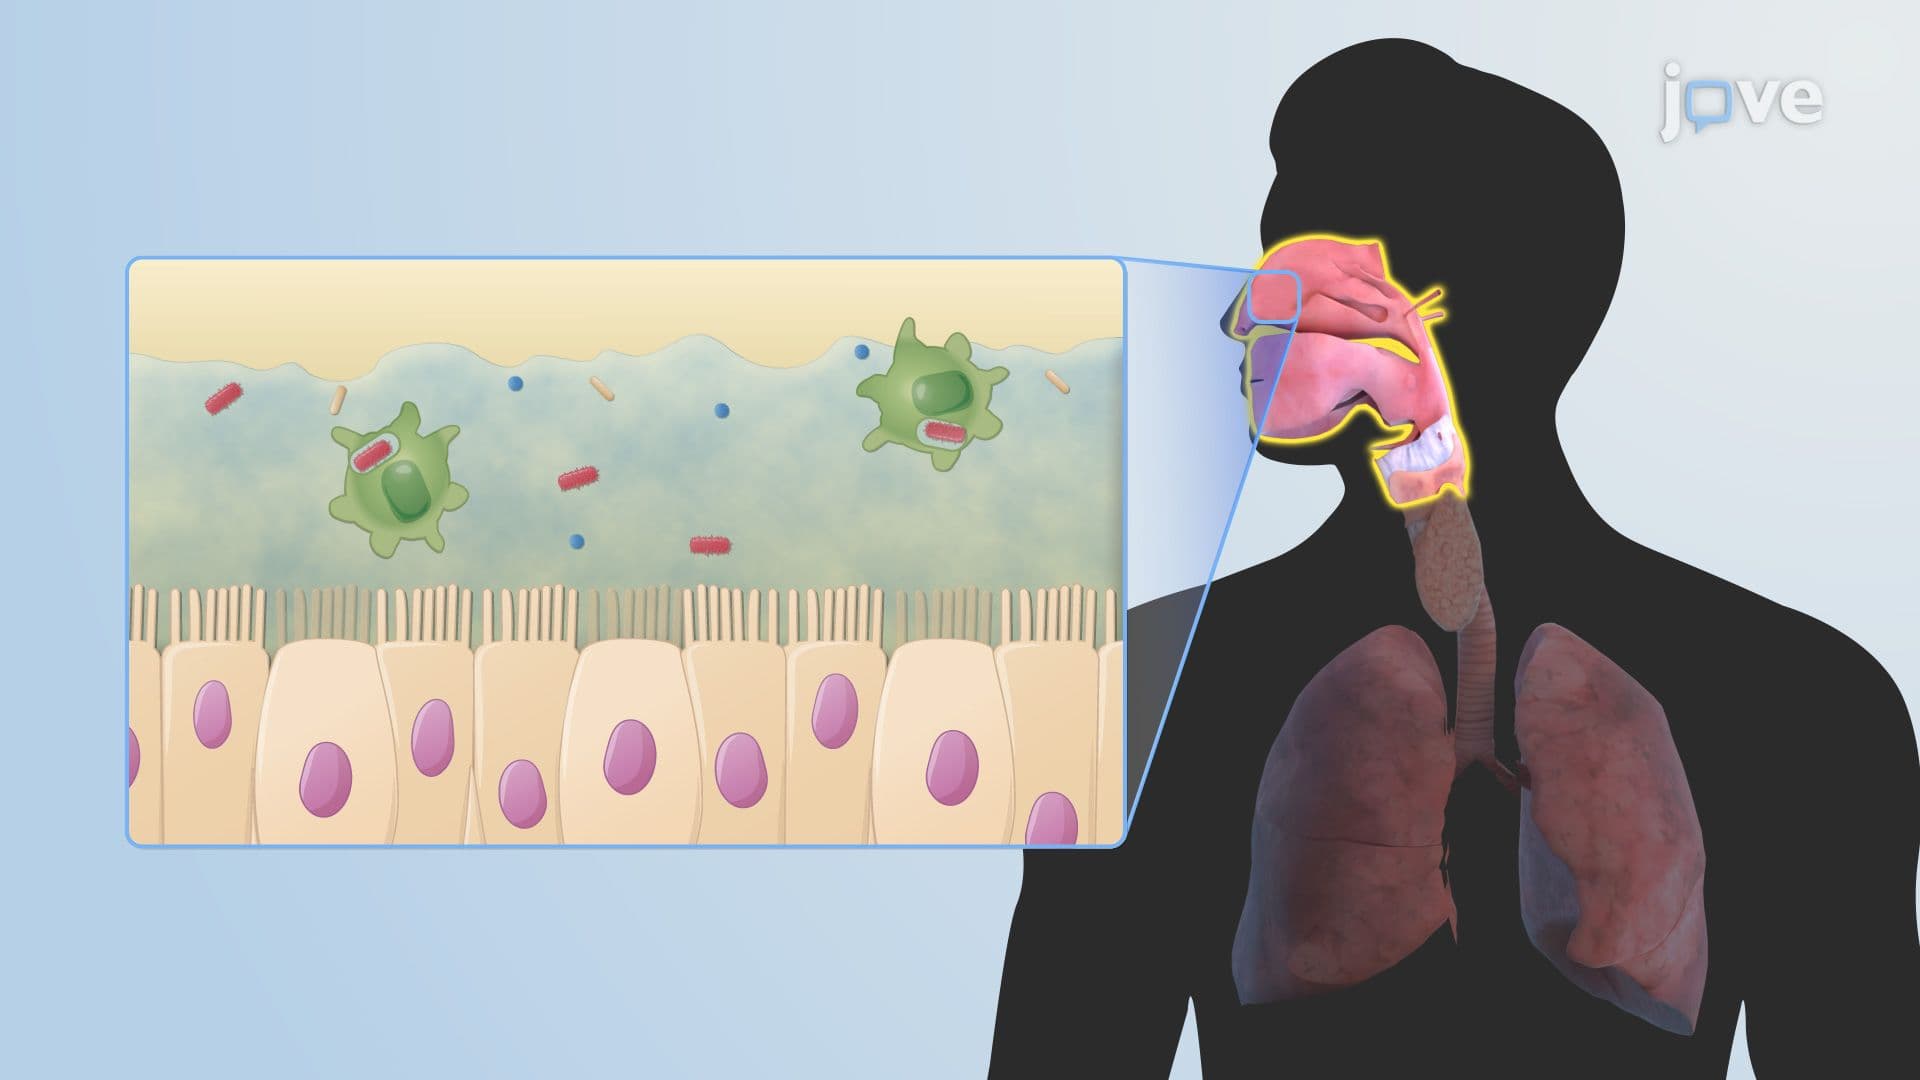
Microbiota of the Respiratory Tract
 01:22
Bacterial Meningitis I: Introduction
 01:26
Bacterial Meningitis II: Pathophysiology
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.
 01:25
Clinical Significance of Antibiotic Resistance