Related Experiment Video
Updated: Sep 26, 2026
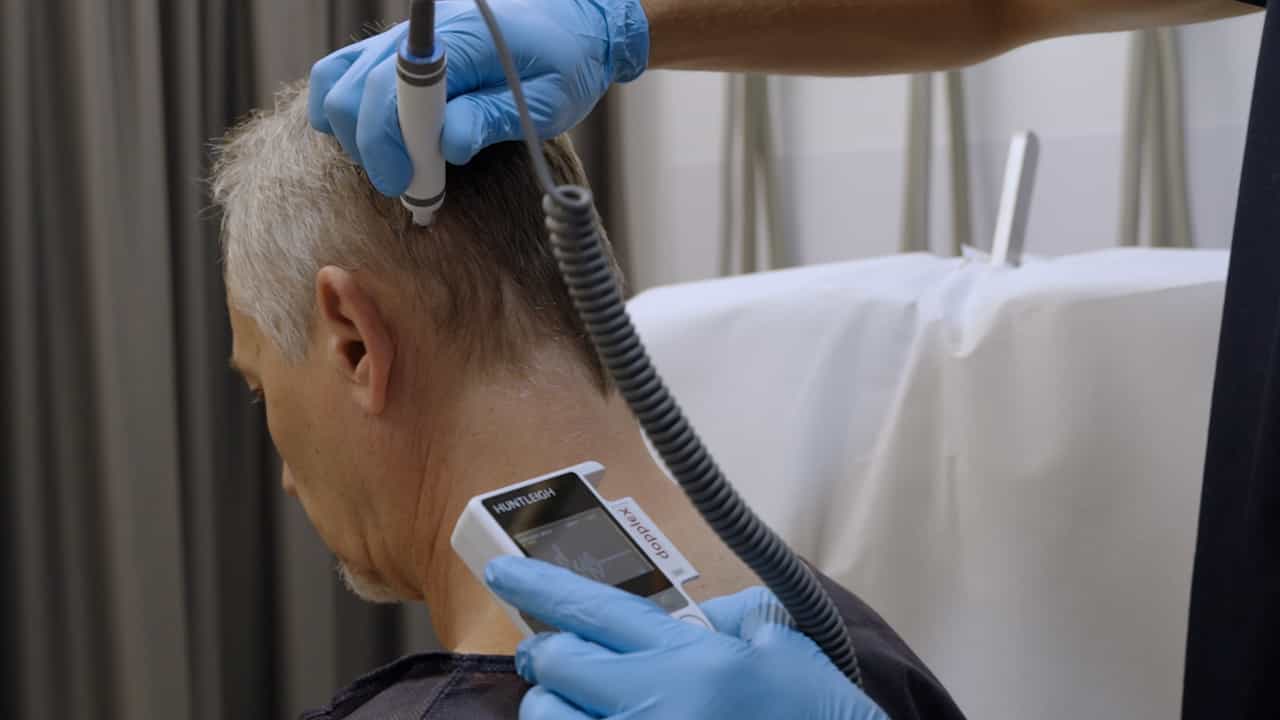

Minimally Invasive Surgical Decompression of Occipital Nerves
Published on: September 13, 2024
Backache, headache, and neurologic deficit after regional anesthesia
1Department of Anesthesiology, Baylor College of Medicine, 6550 Fannin, Smith Tower Suite 1003, Houston, TX 77030, USA. umunnur@bcm.tmc.edu

Back pain, chemical backache, PDPH, and neurologic deficit all may be reported after regional anesthesia for childbirth. Back pain is common during pregnancy, but epidural analgesia during labor does not increase the incidence of long-term back pain. Chemical backache caused by 2-chloroprocaine is probably a result of hypocalcemic tetany of paraspinous muscles. The mechanism is presumed to be chelation of calcium by sodium bisulfite, an antioxidant present in nesacaine-MPF. PDPH after dural puncture is caused by leakage of CSF, which causes cerebral hypotension. Cerebral hypotension leads to traction on pain-sensitive intracranial structures and cerebral vasodilation. Initial therapy includes hydration, caffeine, and sumatriptan. EBP is the most effective treatment in severe PDPH. If the first EBP fails, a second blood patch can be performed. Neurologic deficits after regional anesthesia are rare. Meticulous technique and vigilance are the keystones in avoiding major neurologic complications of regional anesthesia. Rapid diagnosis and appropriate treatment are essential to optimize a successful outcome if complications do develop.
Back pain, chemical backache, PDPH, and neurologic deficit all may be reported after regional anesthesia for childbirth. Back pain is common during pregnancy, but epidural analgesia during labor does not increase the incidence of long-term back pain. Chemical backache caused by 2-chloroprocaine is probably a result of hypocalcemic tetany of paraspinous muscles. The mechanism is presumed to be chelation of calcium by sodium bisulfite, an antioxidant present in nesacaine-MPF. PDPH after dural puncture is caused by leakage of CSF, which causes cerebral hypotension. Cerebral hypotension leads to traction on pain-sensitive intracranial structures and cerebral vasodilation. Initial therapy includes hydration, caffeine, and sumatriptan. EBP is the most effective treatment in severe PDPH. If the first EBP fails, a second blood patch can be performed. Neurologic deficits after regional anesthesia are rare. Meticulous technique and vigilance are the keystones in avoiding major neurologic complications of regional anesthesia. Rapid diagnosis and appropriate treatment are essential to optimize a successful outcome if complications do develop.
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:12
Regional Terms
Primarily, the human body has two major regions, the axial and appendicular regions. The axial region comprises regions from the head to the abdomen and makes up the central body axis. In contrast,...
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...
 01:22
Stages of General Anesthesia