Related Experiment Video
Updated: Sep 26, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
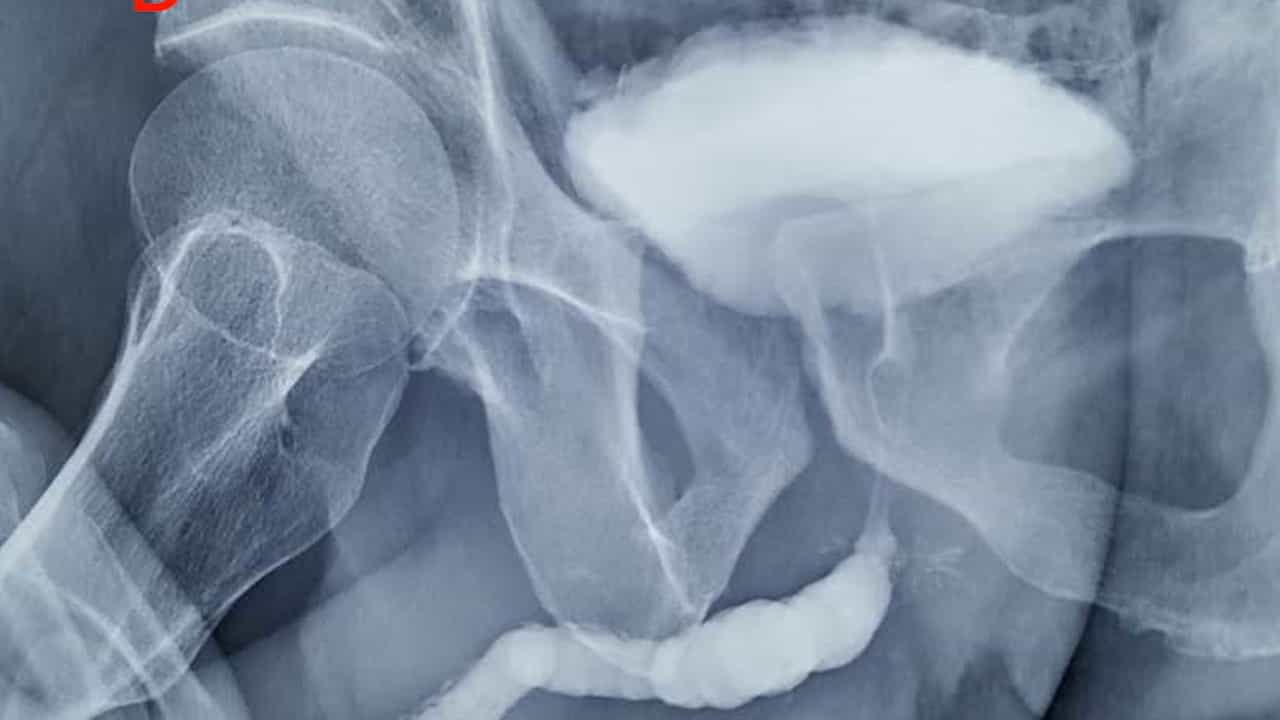
Posterior urethral valves: prognostic factors
P Lopez Pereira1, L Espinosa, M J Martinez Urrutina
1Department of Paediatric Urology, University Hospital La Paz, Madrid, Spain. plpuro@hotmail.com

Insights
Glomerular filtrate rate (GFR) at one year old is the key predictor of chronic renal failure (CRF) in boys with posterior urethral valves (PUV). Proteinuria and echogenic renal changes also indicate a worse prognosis for renal function.
Area of Science:
- Pediatric Nephrology
- Urology
- Medical Research
Background:
- Posterior urethral valves (PUV) are a common congenital anomaly in male infants.
- Bladder dysfunction is a known factor affecting renal function in PUV patients.
- Predicting long-term renal outcomes beyond bladder issues is crucial for management.
Purpose of the Study:
- To identify predictors of renal function outcome in boys with PUV, excluding bladder dysfunction.
- To investigate the role of variables like vesico-ureteric reflux, urinary tract infections, and renal echogenicity.
Main Methods:
- Retrospective study of 40 boys with PUV diagnosed within the first three months of life.
- Minimum of five years of follow-up for all patients.
- Comparison of initial and follow-up renal function, vesico-ureteric reflux, urinary tract infection, proteinuria, hypertension, renal echogenicity, and management strategies.
Main Results:
- Glomerular filtrate rate (GFR) at one year old was significantly lower in boys who developed chronic renal failure (CRF) (52 mL/min/1.73 m2) compared to those with normal renal function (102 mL/min/1.73 m2).
- Proteinuria during follow-up was present in 79% of patients with CRF versus 17% with normal renal function.
- Echogenic renal changes were observed in all patients who developed CRF, compared to 53% of those with normal renal function.
Conclusions:
- GFR at one year old is the most significant predictor of future CRF in boys with PUV.
- Onset of proteinuria during follow-up is associated with a poorer renal prognosis.
- Renal echogenicity can help identify kidneys at risk for developing renal insufficiency.
Objective:
To determine which variables besides bladder dysfunction can help to predict the outcome of renal function in boys with posterior urethral valves (PUV).
Patients And Methods:
All 40 patients with PUV in this retrospective study were diagnosed and began treatment in our hospital within the first 3 months of life, and have had >or= 5 years of follow-up. At the time of diagnosis, 33 were in renal insufficiency (RI) and seven had normal renal function (RF). At the time of the study 16 were in chronic renal failure (CRF) and 24 had normal RF. We compared their RF (initial and during follow-up), vesico-ureteric reflux (VUR), urinary tract infection (UTI), proteinuria, hypertension, renal echogenicity, final patient age and initial management.
Results:
The mean serum creatinine values before and after initial treatment were worse in boys who developed CRF than in those who did not (P = 0.08); the mean glomerular filtrate rate (GFR) at 1 year old was 52 mL/min/1.73 m2 in the former and 102 in the latter (P < 0.001). Proteinuria was present during the follow-up in 79% of patients in CRF and in only 17% of those with normal RF. All patients who developed CRF had echogenic renal changes while only 53% of the others had (P < 0.01). Other variables showed no statistically significant differences (VUR, UTI, hypertension and final patient age). Of 33 patients in RI at diagnosis, nine were treated by valve ablation and 24 by temporary pyelo-ureterostomy. The initial mean serum creatinine value was worse in the latter than in the former (20.8 vs 13.0 mg/L). However, at 1 year old the mean GFR was better in the latter than in the former (P < 0.05). These GFR differences persisted during the first years of life but had disappeared by the fifth.
Conclusions:
The most significant prognostic factor for the future development of CRF is the GFR at 1 year old. The onset of proteinuria during the follow-up is associated with a worse prognosis. Echogenic renal changes may help to identify those dysplastic kidneys that will develop RI. Neonatal boys in RI who underwent pyelo-ureterostomy had better RF during the first years of life than those who underwent valve ablation.
Related Concept Videos
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:28
Microbiota of the Urogenital Tract
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:27
Mitral Valve Prolapse I: Introduction
 01:30
Urinary Tract Calculi III: Medical Management