Related Experiment Video
Updated: Sep 26, 2026


Assessing Corticospinal Excitability During Goal-Directed Reaching Behavior
Published on: December 2, 2022
Ready to go
1Med Trans One, Greenville, SC, USA.

The patient with a decreased level of consciousness in the absence of trauma presents difficult assessment and intervention problems. This is compounded when the history is vague or nonspecific. In this case, the patient's history of embolic CVA alerted providers to the possibility of another thrombus. This patient's sudden symptoms could have resulted from a clot in the brain, heart or aorta. This patient presented with an altered level of consciousness, vomiting and low blood pressure. As is typical in elderly female patients, she had an unusual presentation of an MI. A myocardial infaction is classified as either transmural or subendocardial. A transmural infarct extends through the full thickness of the myocardium and holds greater-risk of complications due to loss of functional muscle. In a subendocardial infarct, necrosis is limited to the endocardial surface. Although many elderly patients present with subendocardial MIs, this one had a large transmural MI. In general, the circumflex artery serves the lateral and posterior walls of the myocardium, and the right coronary artery (RCA) serves the inferior wall. In an anterior MI, the left anterior descending artery (LAD) is obstructed. This vessel serves the left ventricle, parts, of the septum and paillary muscles. The LAD is often referred to as the "widowmaker" because left ventricular infarcts have a high incidence of mortality. Occlusion of LAD can cause the usual damage of an MI, and can also cause fatal damage to the valves. This patient was in profound cardiogenic shock -- the left ventricle had infarcted and was unable to maintain cardiac output. Because of her recent stroke, she was not a candidate for thrombolytic medication. With ultrasonography, a large area of the anterior wall was found to be akinetic, or not functioning at all. In this care, the sourrounding myocardium not only has to pump blood with less muscle but also to "drag" the dead tissue. This results in a progressively higher rate of O2 cnsumption within the heart, further damage to the strained heart, and death. As cigarette smoking and obesity complete for the leading preventable cause of death in the United States, familiarity with cardiac anatomy and physiology 12-lead interpretation, pharmacology and electrical therapy is essential for all emergency providers
The patient with a decreased level of consciousness in the absence of trauma presents difficult assessment and intervention problems. This is compounded when the history is vague or nonspecific. In this case, the patient's history of embolic CVA alerted providers to the possibility of another thrombus. This patient's sudden symptoms could have resulted from a clot in the brain, heart or aorta. This patient presented with an altered level of consciousness, vomiting and low blood pressure. As is typical in elderly female patients, she had an unusual presentation of an MI. A myocardial infaction is classified as either transmural or subendocardial. A transmural infarct extends through the full thickness of the myocardium and holds greater-risk of complications due to loss of functional muscle. In a subendocardial infarct, necrosis is limited to the endocardial surface. Although many elderly patients present with subendocardial MIs, this one had a large transmural MI. In general, the circumflex artery serves the lateral and posterior walls of the myocardium, and the right coronary artery (RCA) serves the inferior wall. In an anterior MI, the left anterior descending artery (LAD) is obstructed. This vessel serves the left ventricle, parts, of the septum and paillary muscles. The LAD is often referred to as the "widowmaker" because left ventricular infarcts have a high incidence of mortality. Occlusion of LAD can cause the usual damage of an MI, and can also cause fatal damage to the valves. This patient was in profound cardiogenic shock -- the left ventricle had infarcted and was unable to maintain cardiac output. Because of her recent stroke, she was not a candidate for thrombolytic medication. With ultrasonography, a large area of the anterior wall was found to be akinetic, or not functioning at all. In this care, the sourrounding myocardium not only has to pump blood with less muscle but also to "drag" the dead tissue. This results in a progressively higher rate of O2 cnsumption within the heart, further damage to the strained heart, and death. As cigarette smoking and obesity complete for the leading preventable cause of death in the United States, familiarity with cardiac anatomy and physiology 12-lead interpretation, pharmacology and electrical therapy is essential for all emergency providers
More Related Videos


Related Concept Videos
 01:20
Motivational Cycle
The cycle begins with a need. This need can arise from various conditions, such as hunger, thirst, or temperature changes. For instance, when an individual feels cold, their body...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care evaluation by...
 01:20
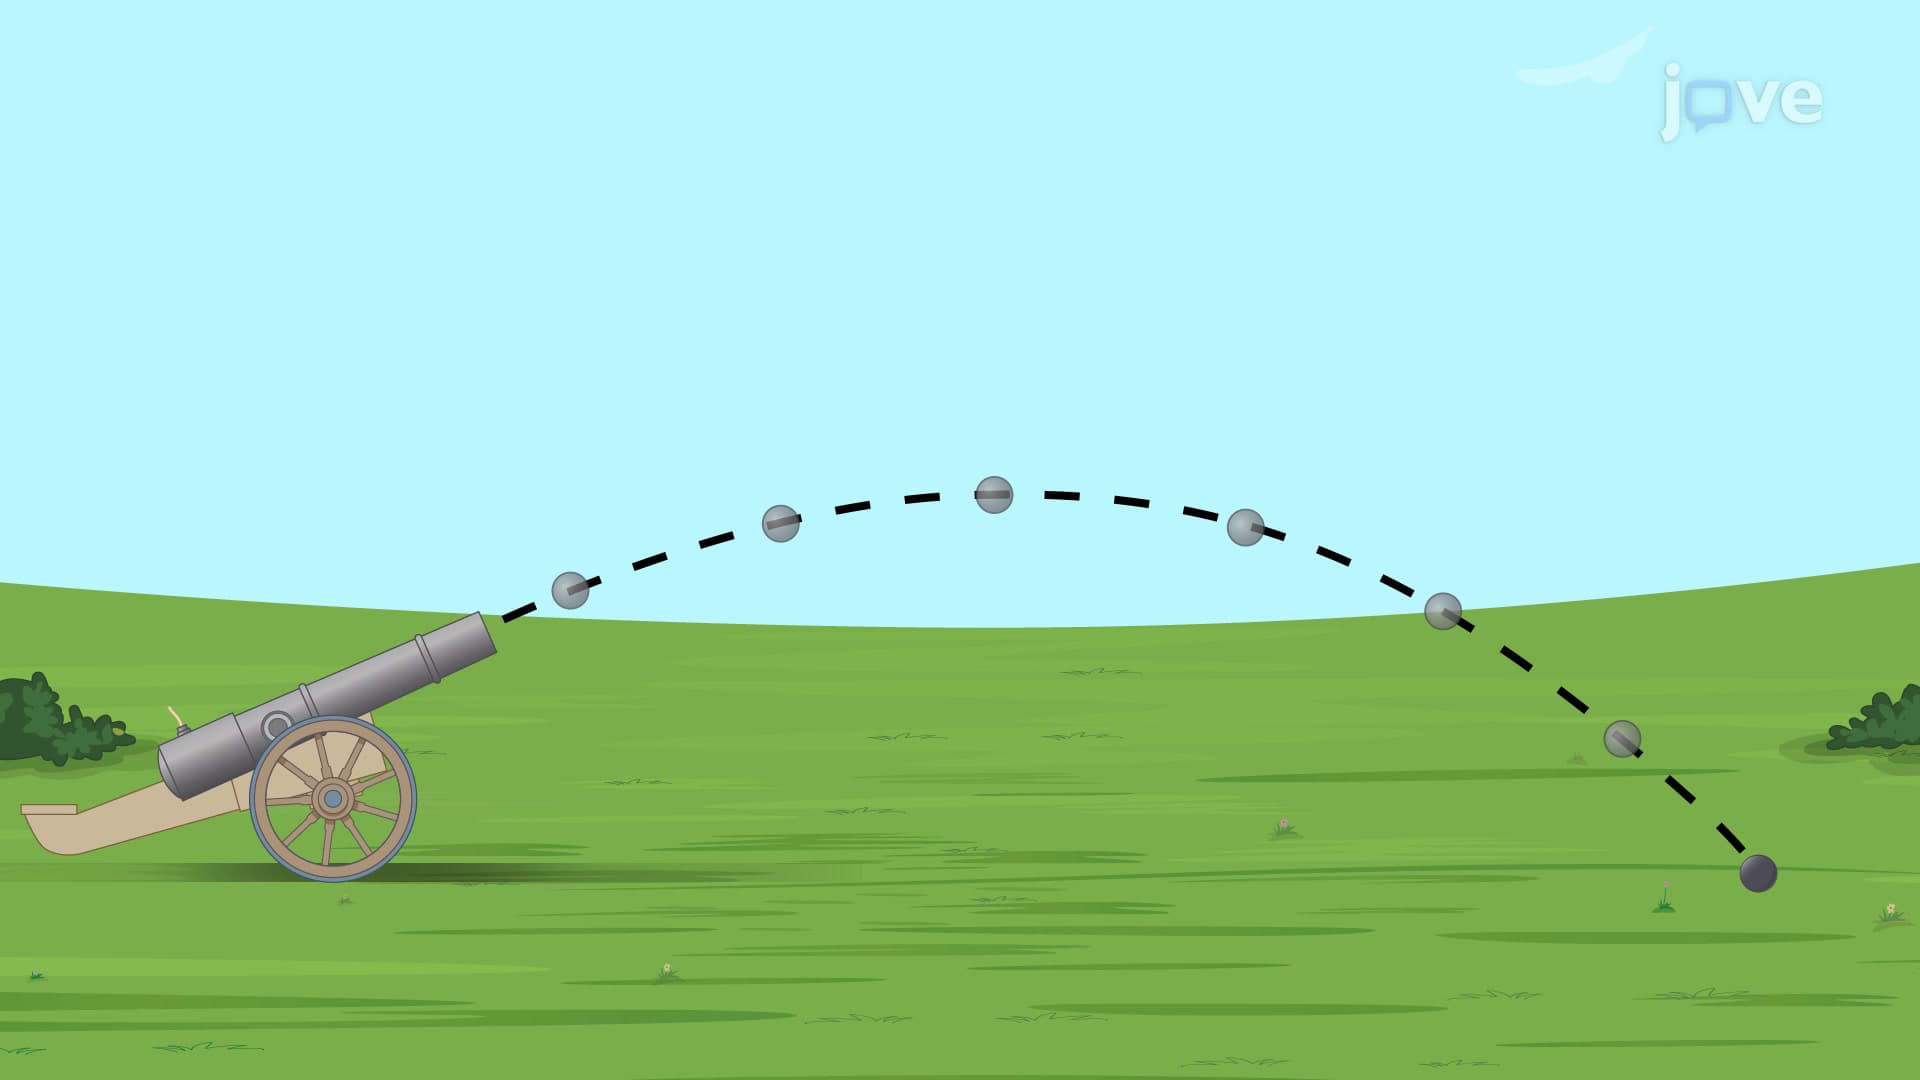
Projectile Motion
When an object falls under gravity and has no horizontal...
 01:25
Projectile Motion
 01:25
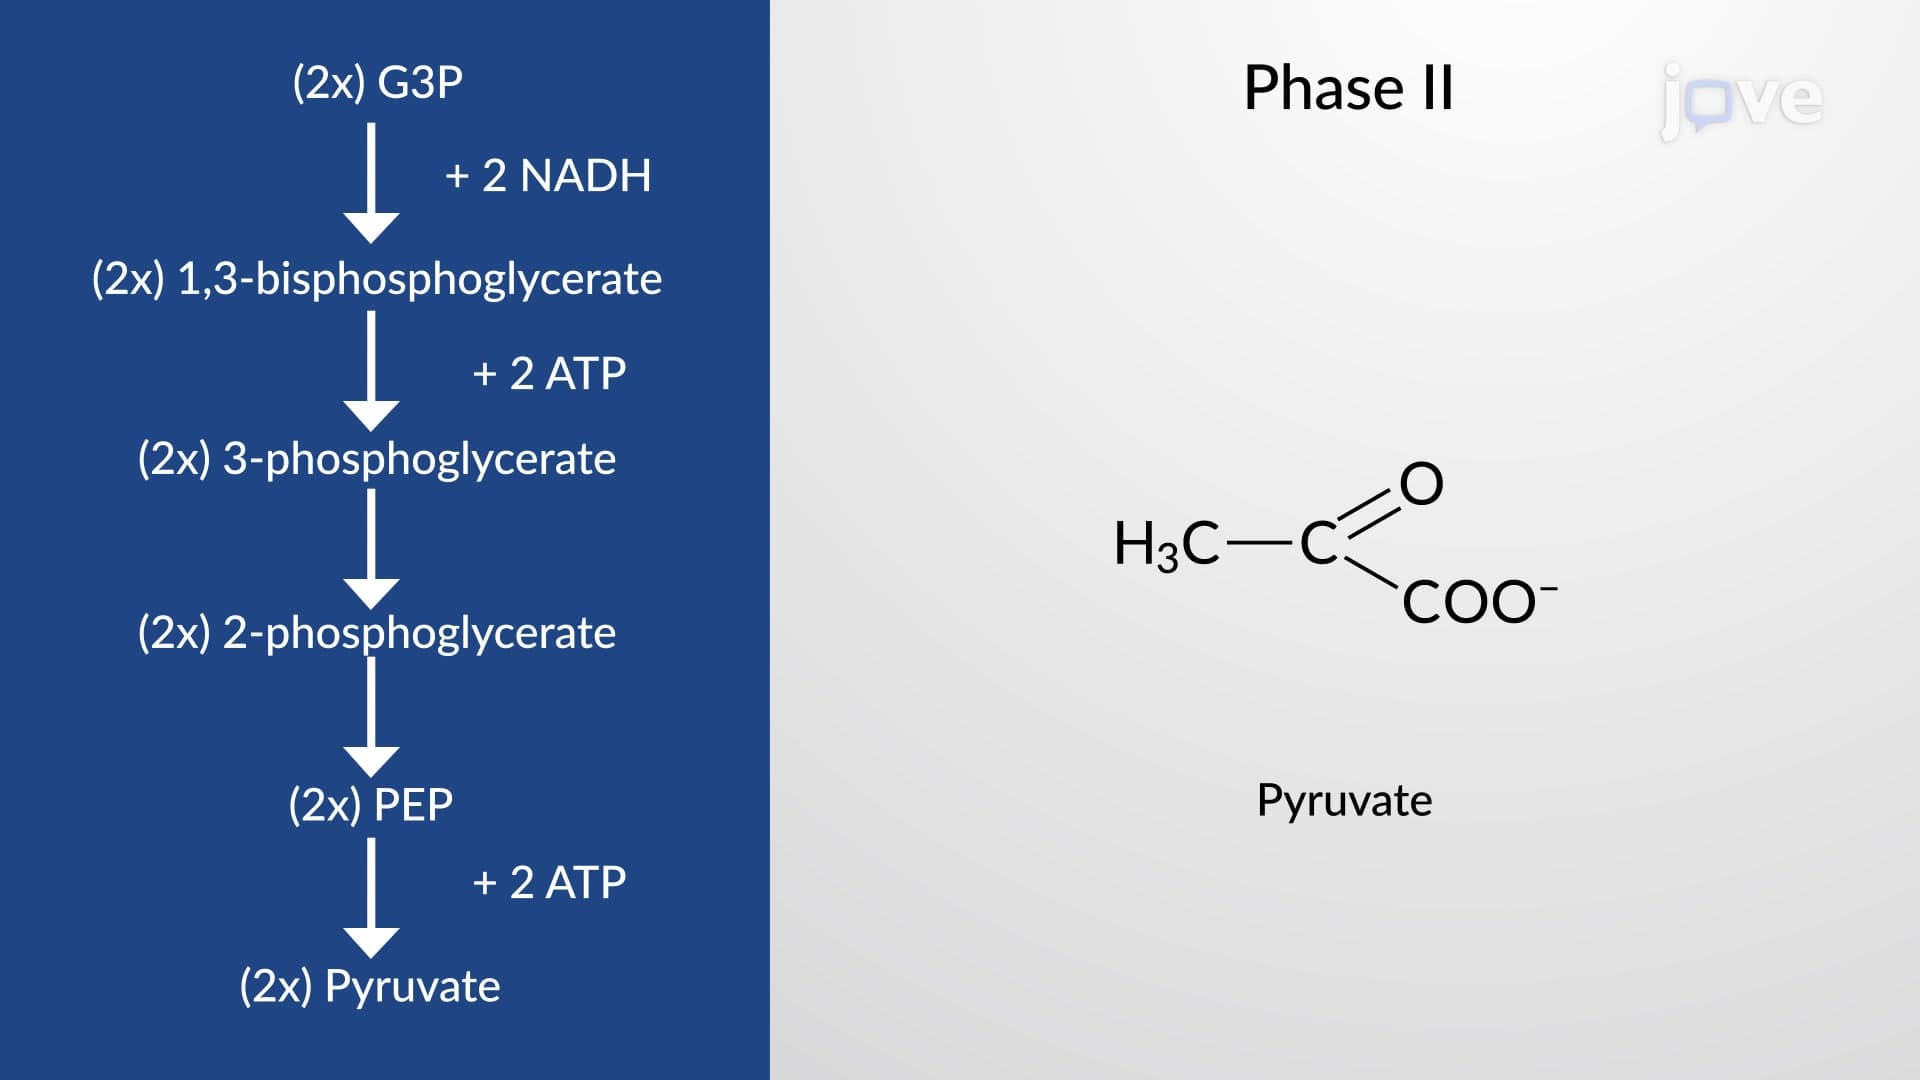
Glycolysis: Pay-off Phase
Step 1 - 5: Glycolysis Preparatory Phase
The first phase of glycolysis has 5 steps where the glucose is...
 01:16
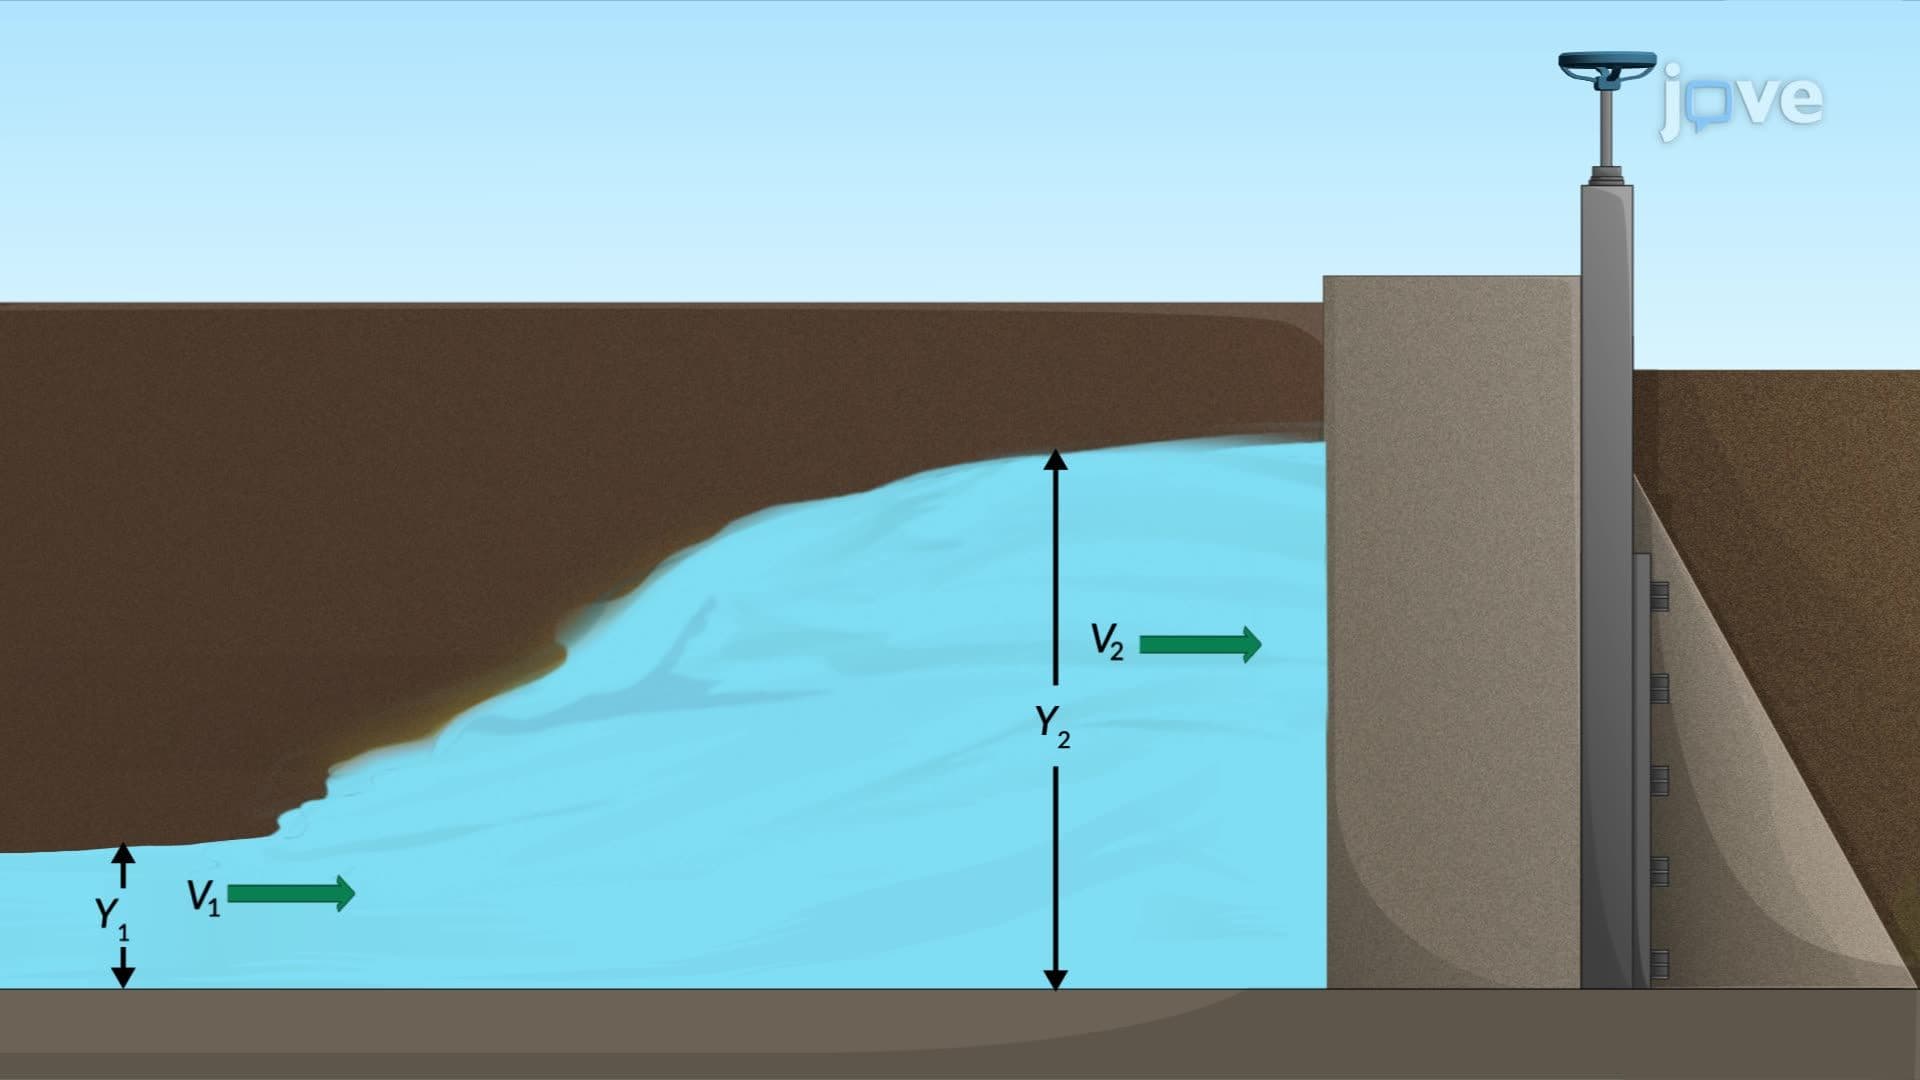
Hydraulic Jump: Problem Solving