Related Experiment Video
Updated: Sep 26, 2026
Identification of Small Molecule-binding Proteins in a Native Cellular Environment by Live-cell Photoaffinity Labeling
Published on: September 20, 2016
Effect of itraconazole on the pharmacokinetics of rosuvastatin
Kelvin J Cooper1, Paul D Martin, Aaron L Dane
1AstraZeneca, Macclesfield, Cheshire, United Kingdom.

Background:
Rosuvastatin is a new 3-hydroxy-3-methylglutaryl coenzyme A (HMG-CoA) reductase inhibitor. Itraconazole, an inhibitor of cytochrome P450 (CYP) 3A4 and the transport protein P-glycoprotein, is known to interact with other HMG-CoA reductase inhibitors. The current trials aimed to examine in vivo the effect of itraconazole on the pharmacokinetics of rosuvastatin.
Methods:
Two randomized, double-blind, placebo-controlled, 2-way crossover trials were performed. Healthy male volunteers (trial A, n = 12; trial B, n = 14) received itraconazole, 200 mg, or placebo once daily for 5 days; on day 4, 10 mg (trial A) or 80 mg (trial B) of rosuvastatin was coadministered. Plasma concentrations of rosuvastatin, rosuvastatin-lactone (trial A only), and active and total HMG-CoA reductase inhibitors were measured up to 96 hours after dosing.
Results:
After coadministration with itraconazole, the rosuvastatin geometric least-square mean for the treatment ratio was increased by 39% for AUC(0-ct) (area under the rosuvastatin plasma concentration-time curve from time 0 to the last common time at which quantifiable concentrations were obtained for both treatments within a volunteer in trial A) and by 28% for AUC(0-t) (area under the rosuvastatin plasma concentration-time curve from time 0 to the time of the last quantifiable concentration in trial B), with the treatment ratio for maximum observed plasma drug concentration increased by 36% in trial A and 15% in trial B compared with placebo. For trial A (but not for trial B), the upper boundary of the 90% confidence interval for the treatment ratios fell outside the preset limits (0.7-1.43). The 95% confidence intervals for all treatment ratios (except maximum observed plasma drug concentration in trial B) did not include 1. These results indicate that itraconazole produces a modest increase in plasma concentrations of rosuvastatin. Rosuvastatin accounted for the majority of the circulating active HMG-CoA reductase inhibitors (> or =87%) and most of the total inhibitors (> or =75%).
Conclusions:
Itraconazole produced modest increases in rosuvastatin plasma concentrations, which are unlikely to be of clinical relevance. The results support previous in vitro metabolism findings that CYP3A4 plays a minor role in the limited metabolism of rosuvastatin.

Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:25
Pharmacokinetics: Drug–Drug Interactions
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:26
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
 01:09
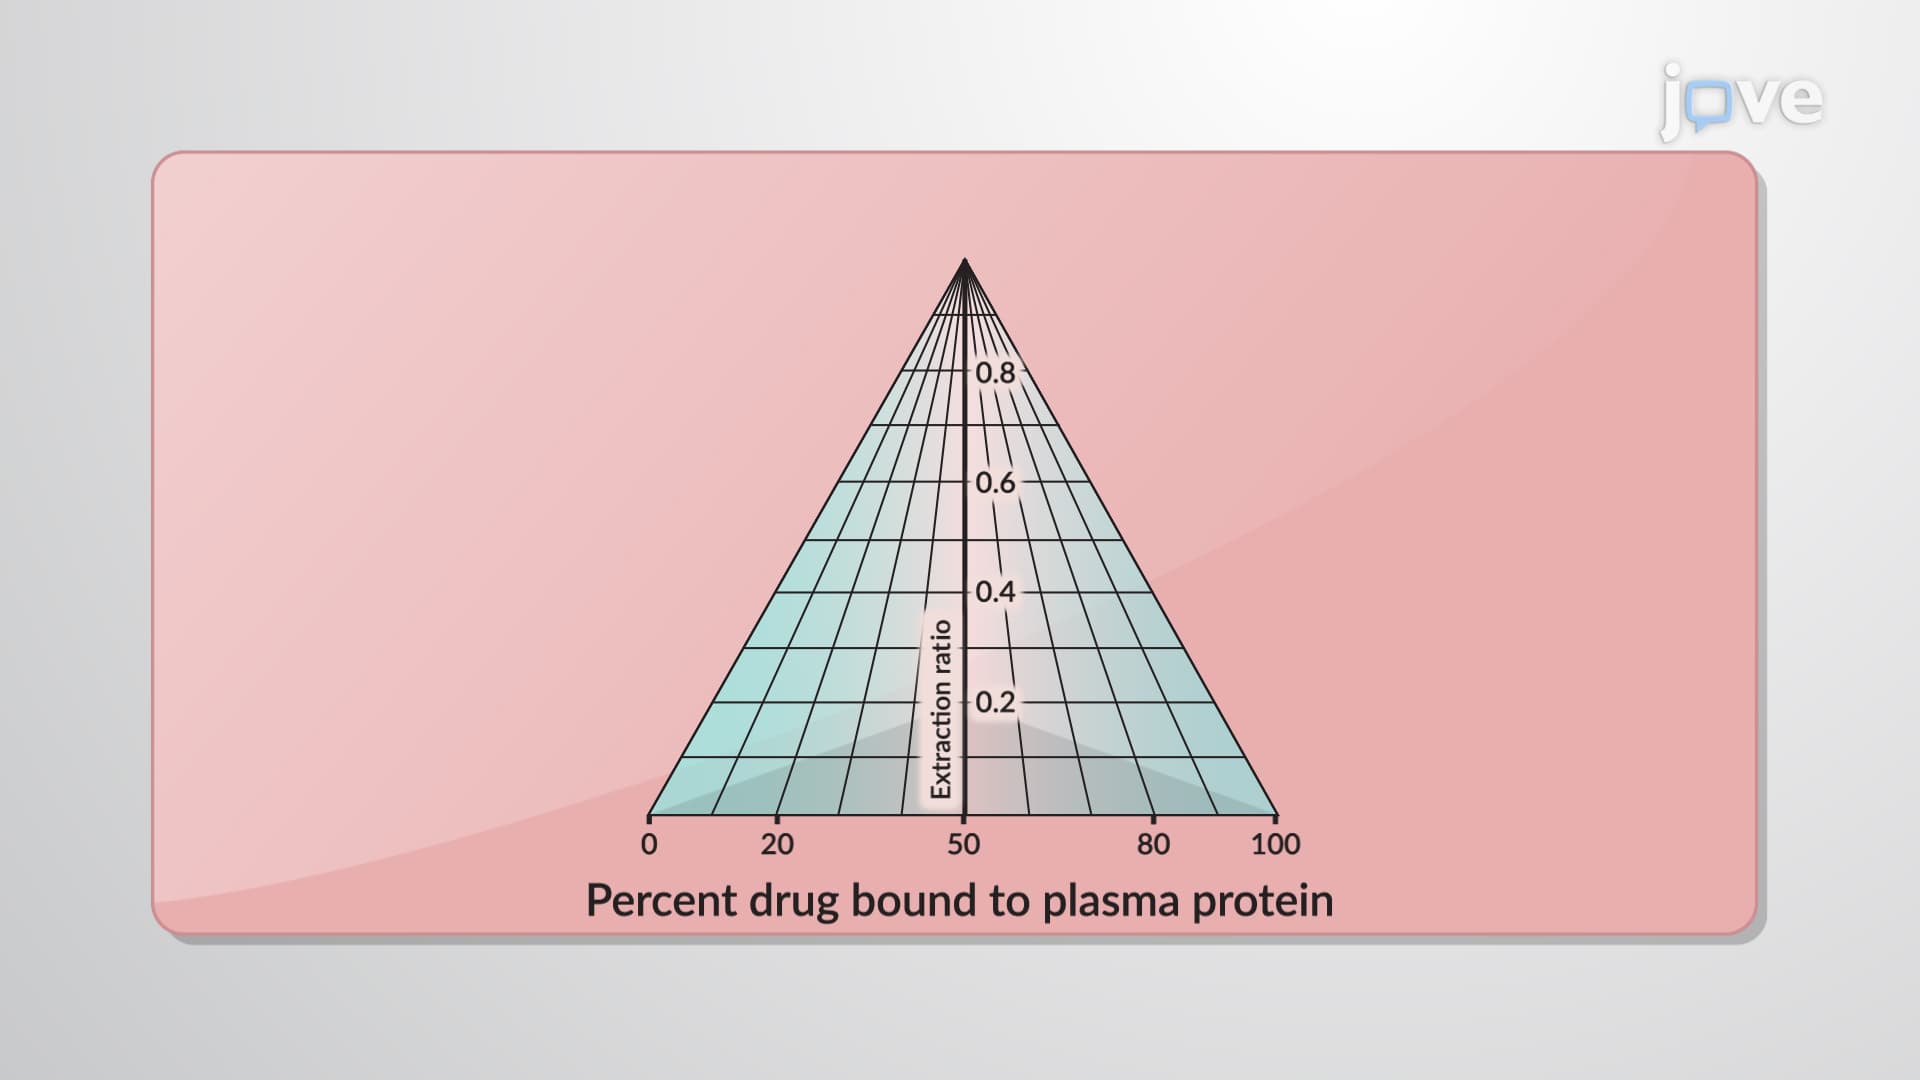
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow