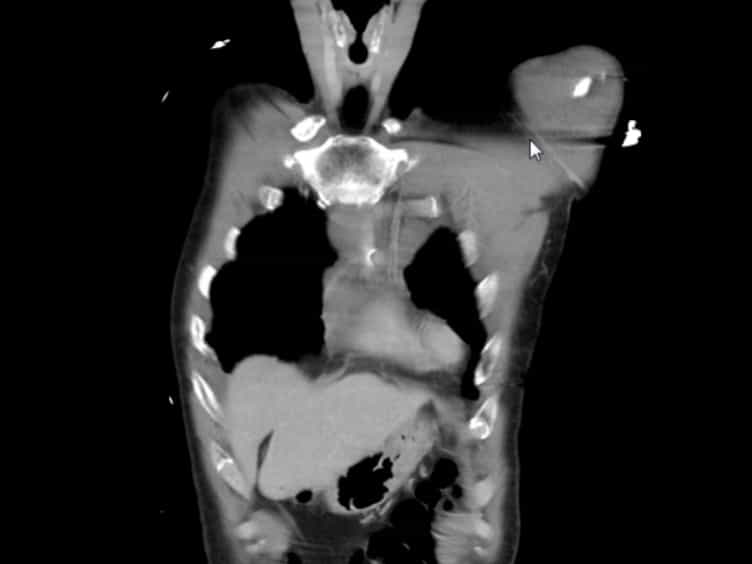


Insights
Pectus excavatum (PE), a common childhood chest deformity, often requires surgical repair. The modified Ravitch technique offers good results with minimal complications, while the Nuss repair has a higher complication rate.
Area of Science:
- Congenital anomalies
- Pediatric surgery
- Thoracic surgery
Background:
- Pectus excavatum (PE) is a frequent congenital chest wall anomaly affecting males more than females.
- Severity increases during adolescence, leading to symptoms like dyspnea, fatigue, chest pain, and reduced cardiac output.
- Surgical repair is recommended for symptomatic patients with a high pectus severity index.
Discussion:
- The modified Ravitch technique, typically performed after age 8 (optimal 12-16 years), involves minimal cartilage removal and a temporary support bar.
- This approach has a high success rate (97% good to excellent results), short operation time, and brief hospitalization.
- The minimally invasive Nuss repair, while faster, is associated with more pain, longer hospitalization, and higher complication rates, and is less suitable for older patients or those with asymmetry.
Key Insights:
- The modified Ravitch technique is a well-established, effective surgical option for pectus excavatum.
- The Nuss repair presents an alternative but with notable drawbacks regarding pain and complications.
- Patient selection and long-term follow-up are crucial for determining the optimal surgical approach.
Outlook:
- Further long-term studies are needed to compare the efficacy and outcomes of both surgical techniques.
- Advancements in surgical techniques aim to minimize invasiveness while improving patient recovery and results.
- Understanding the long-term impact of each repair method will guide future treatment strategies for pectus excavatum.
Abstract:
Pectus excavatum (PE) is one of the most common anomalies of childhood. It occurs in approximately 1 in every 400 births, with males afflicted 5 times more often than females. PE is usually recognized in infancy, becomes much more severe during adolescent growth years, and remains constant throughout adult life. Symptoms are infrequent during early childhood, but become increasingly severe during adolescent years with easy fatigability, dyspnea with mild exertion, decreased endurance, pain in the anterior chest, and tachycardia. The heart is deviated into the left chest to varying degrees causing reduction in stroke volume and cardiac output. Pulmonary expansion is confined, causing a restrictive defect. Repair is recommended for patients who are symptomatic and who have a markedly elevated pectus severity index as determined by chest X-ray or computed tomography scan. Repair using the highly modified Ravitch technique is usually performed after the age of 8 years. The optimal age for repair is between 12 and 16 years. Repair can be performed on adults with similar good results. Recent modifications in the Ravitch technique remove minimal cartilage and routinely use a temporary internal support bar for 6 months. Operation rarely takes more than 3 hours, and hospitalization rarely exceeds 3 days. Pain is mild and complications are rare, with 97% of patients experiencing a good to excellent result. The new minimally invasive Nuss repair avoids cartilage resection and takes less operating time, but is associated with more severe pain, longer hospitalization and a higher complication rate, with the bar remaining for 2 or more years. This technique is less applicable to older patients and those with asymmetric deformities. Long-term follow-up will be necessary to determine which operation may be best for any specific patient.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:17
Pericarditis III: Medical Management
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management