Related Experiment Video
Updated: Sep 2, 2026

Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
Vascular thoracic outlet syndrome
Lazar B Davidovic1, Dusan M Kostic, Nenad S Jakovljevic
1Institute for Cardiovascular Diseases, Serbian Clinical Centre, 8, K Todorovica St, 11 000, Belgrade, Yugoslavia. lazard@eunet.yu

Abstract:
The surgical treatment of 30 cases of vascular thoracic outlet syndrome (TOS) in 25 patients is presented. Patients included 17 women and 8 men with average age of 26.1 years. The causes of compression were cervical rib ( n = 16), soft tissue anomalies ( n = 12), and scar tissue after clavicle fracture ( n = 2). Ten subclavian artery aneurysms containing intraluminal thrombus as well as one subclavian artery occlusion were found. All such cases had multiple distal arterial embolization. Presenting features of cases with arterial TOS included: hand ischemia ( n = 11), transient ischemic attack (TIA) ( n = 1), and claudication or vasomotor phenomena during the arm hyperabduction ( n = 11). Two patients with venous TOS developed hand edema during arm hyperabduction, and five other patients had axillary-subclavian venous thrombosis. In all cases decompressive procedures using a combined supraclavicular and infraclavicular approach were performed. Decompression was achieved by cervical rib excision ( n = 12), combined cervical and first rib excision ( n = 4), and first rib excision ( n = 14). In all cases division of all soft tissue elements was also accomplished. Associated vascular procedures included resection and replacement of 10 subclavian artery aneurysms, one subclavian-axillary and one axillary-brachial bypass, as well as nine brachial embolectomies. All five cases with axillary-subclavian vein thrombosis before decompression were treated with anticoagulant therapy. The mean follow-up period was 3 years and 2 months (range 1 to 6 years). Two pleural entry injuries and two transient brachial plexus injuries were noted. All reconstructed arteries were patent during the follow-up period. Complete resolution of symptoms with a return to full activity was noticed in all cases with arterial TOS and in two cases with venous TOS without axillary-subclavian vein thrombosis. In cases with axillary-subclavian vein thrombosis relief of symptoms was mild, and there were limitations on daily activity. Vascular TOS is seen less frequently than the neurogenic form; however, in most cases it requires surgical treatment. We prefer a combined supraclavicular and infraclavicular approach because it offers complete exposure of the subclavian artery, cervical and first ribs, and all soft tissue anomalies.


Related Concept Videos
 01:15
Thoracic Aorta
 01:19
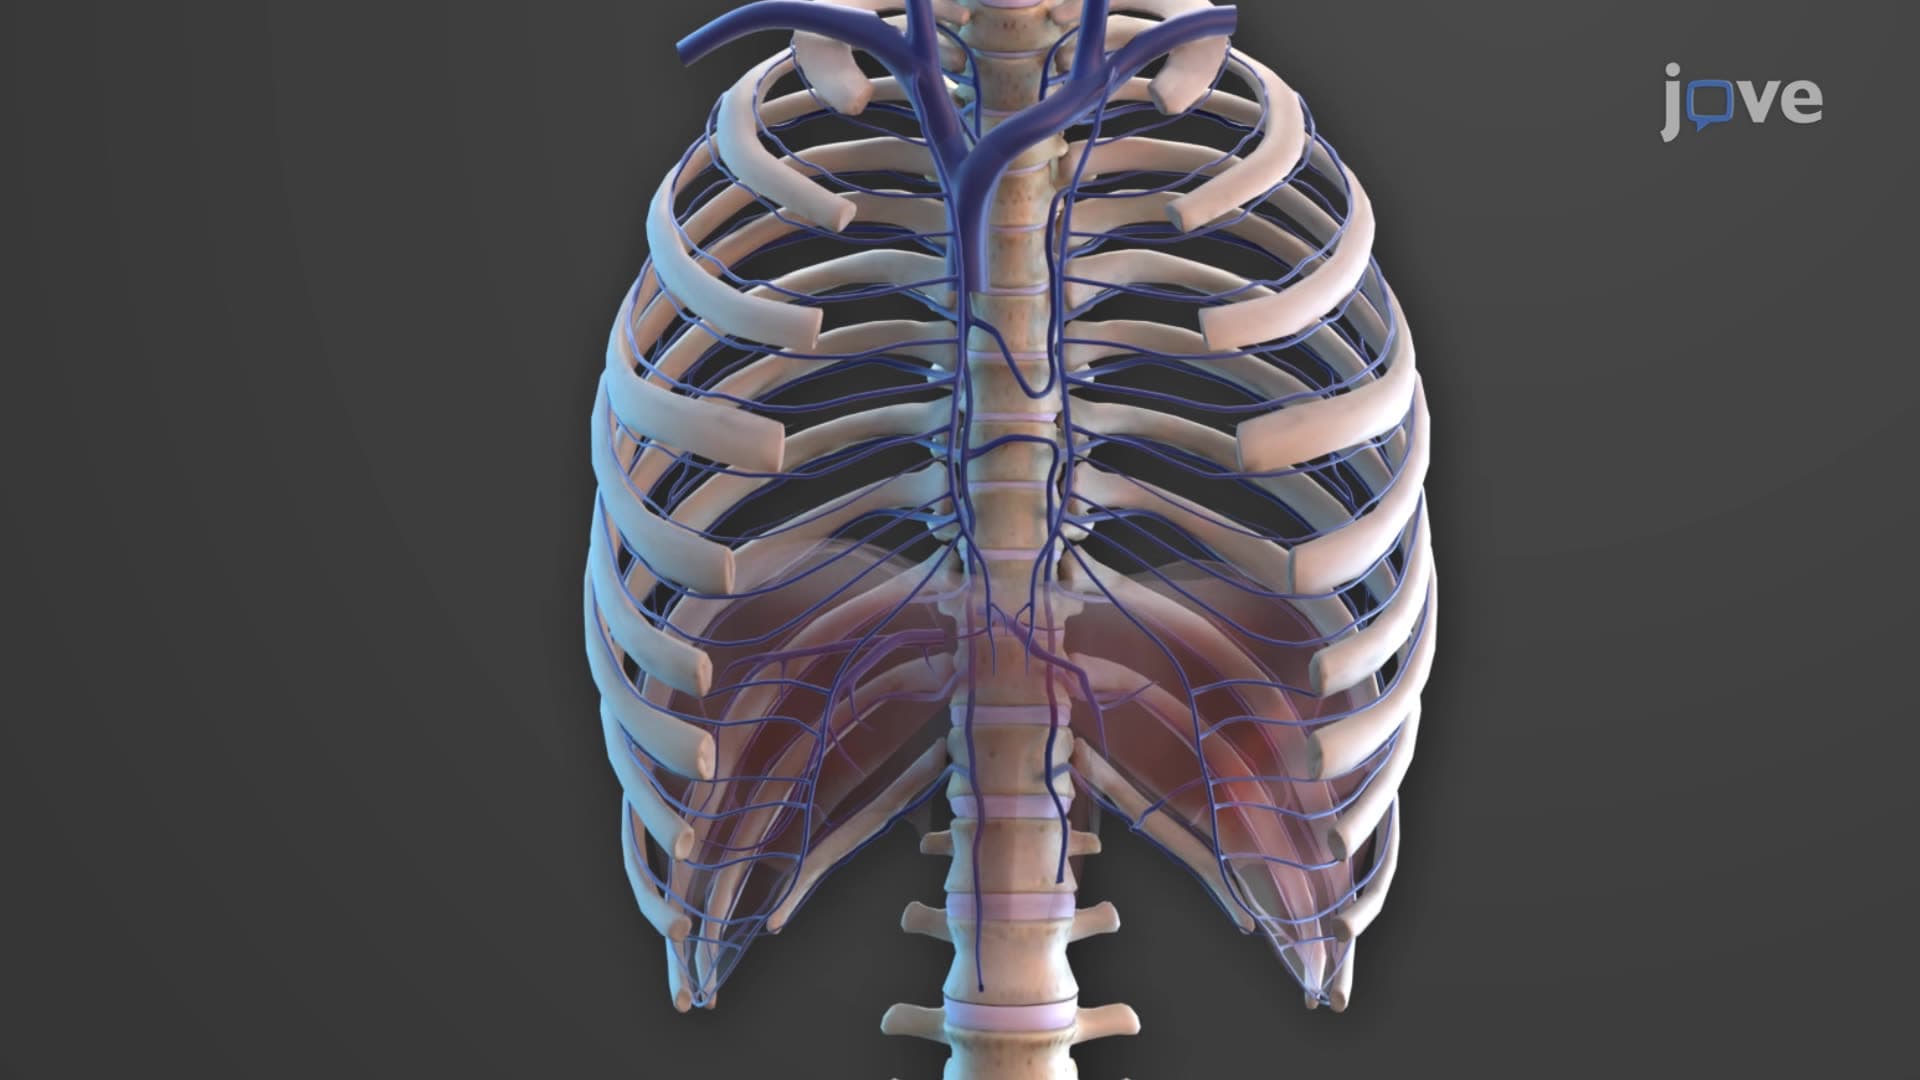
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies