Related Experiment Video
Updated: Sep 26, 2026
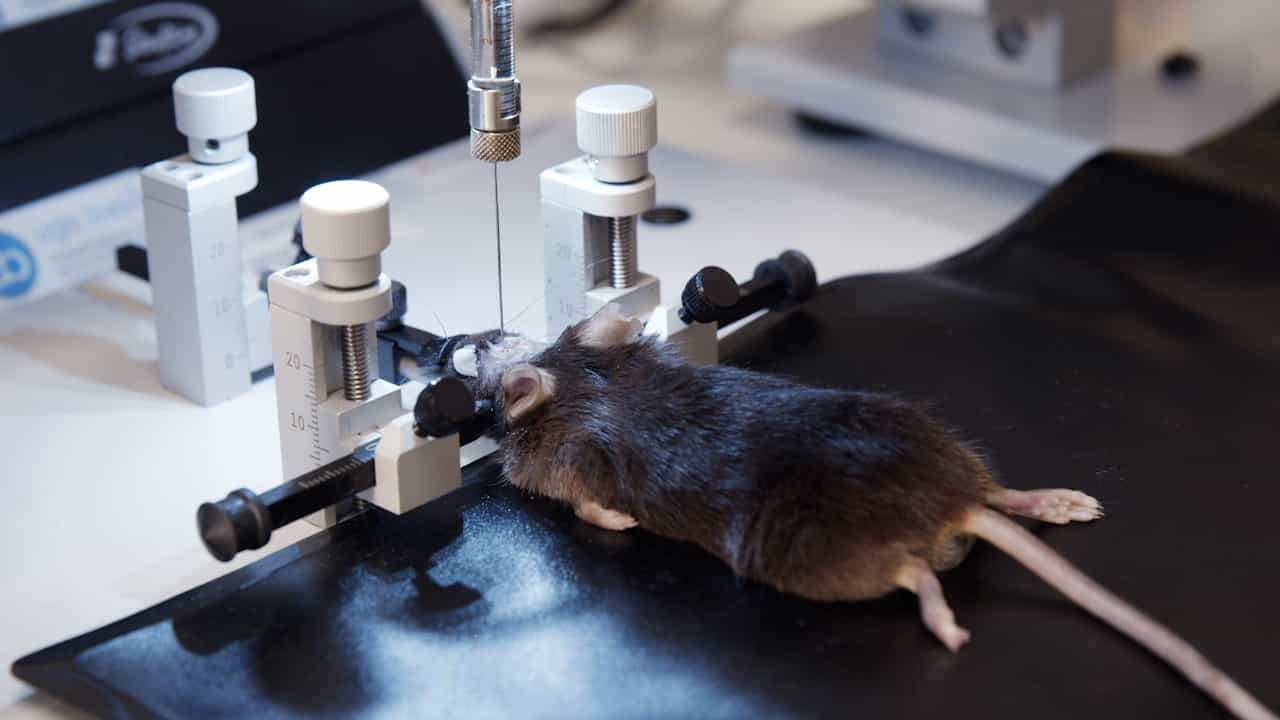
Lentiviral-Induced Striatal Pathology as a Preclinical Model of Polyglutamine Spinocerebellar Ataxias
Published on: March 13, 2026
[Nasu Hakola disease: a report of the first two cases in Bolivia]
M C Molina-Monasterios1, H Molina-Abecia
1Servicio de Neurología y Neurocirugía, Hospital Obrero N.1 de la Caja Nacional de Salud, La Paz, Bolivia. monicmolina@hotmail.com

Introduction:
Nasu Hakola disease (NHD) is a progressive dementia that presents accompanied by bone cysts and, at random, epilepsy. It is an autosomal recessive hereditary disease and its genetic defect is located at the 19q13.1 chromosome. The genetic mutation was identified at DAP 12. It appears that DAP 12 is expressed in the microglial activation and the differentiation of macrophages in the central nervous system and, at the same time, in the osteoclasts in charge of bone remodelling. This double character consisting of dementia and bone cysts, which contain triglycerides and thin PAS positive membranes in a bone with cortical erosion and medullary hypoplasia, enables us to differentiate this disease from other frontotemporal neurodegenerative disorders, such as Pick s disease. At the same time this also allows it to be distinguished from multiple sclerosis, metachromatic leukodystrophy, Marchafava Bignami disease, and prion diseases (such as new variant Creutzfeldt Jakob).
Case Reports:
In this paper we describe two cases of NHD, also known as polycystic lipomembranous osteodysplasia with sclerosing leukoencephalopathy, in which progressive dementia, bone cysts and epilepsy were identified. Serious brain atrophy was found and confirmed by imaging studies and brain biopsies, which were also used to rule out other degenerative diseases of the frontal lobe, as well as Creutzfeldt Jakob disease.
Conclusions:
Both cases meet all the necessary criteria to satisfy a diagnosis of NHD. This is a hereditary, little known disease whose genetic alterations (i.e. mutations) are still in need of further study. It mainly affects males, who suffer the onset of dementia in their thirties. The neurological disorders constitute a frontal syndrome, due to predominant prefrontal involvement, and they occur in the dorsolateral area, with disorders affecting the executive and planning functions; in the orbitofrontal area, which is reflected in social maladjustment and clear obsessive compulsive traits; and also in the medial or cingulate area, which manifests itself as apathy and lack of motivation. When dealing with this disease, in addition to symptomatic therapy, genetic counselling is also important.
Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:23
Tuberculosis