Related Experiment Video
Updated: Sep 26, 2026

Quantification of Monocyte Transmigration and Foam Cell Formation from Individuals with Chronic Inflammatory Conditions
Published on: October 17, 2017
Elevated white blood cell count as a risk factor of coronary artery disease: inconsistency between forms of the
Yutaka Takeda1, Shogo Suzuki, Tatsuya Fukutomi
1Internal Medicine and Bioregulation, Nagoya City University Graduate School of Medical Sciences, Nagoya, Japan.

Insights
Elevated white blood cell (WBC) counts are linked to acute coronary syndrome (ACS) but not stable angina pectoris (sAP). This suggests WBCs may specifically destabilize coronary artery plaques in ACS.
Area of Science:
- Cardiology
- Hematology
- Epidemiology
Background:
- White blood cells (WBCs) are implicated in coronary artery plaque destabilization and coronary artery disease (CAD).
- The differential relationship between WBC counts and distinct CAD forms requires further investigation.
Purpose of the Study:
- To investigate the association between baseline WBC counts and different manifestations of CAD, specifically acute coronary syndrome (ACS) and stable angina pectoris (sAP).
- To identify distinct risk factors associated with ACS versus sAP in a Japanese population.
Main Methods:
- Retrospective analysis of health check-up records from 6021 Japanese male workers (1994-1999).
- Comparison of baseline WBC counts between subjects with ACS, sAP, and those without CAD.
- Logistic regression analysis to identify independent risk factors for ACS and sAP.
Main Results:
- Patients with ACS exhibited significantly higher baseline WBC counts compared to subjects without CAD (9210 vs. 6205/microL, P<0.001).
- WBC counts in sAP patients were similar to those without CAD (6233/microL).
- Hypertension was linked to sAP, while hypercholesterolemia and smoking were risk factors for ACS. Elevated WBC count (odds ratio 2.049) was the sole discriminator between ACS and sAP.
Conclusions:
- An elevated WBC count is a potential risk factor for ACS, possibly due to plaque destabilization, but not for sAP.
- Distinct risk factor profiles exist for ACS and sAP, highlighting the heterogeneous nature of CAD.
Abstract:
White blood cells (WBC) destabilize coronary artery plaques and an elevated WBC count is a risk factor of coronary artery disease (CAD). Nevertheless, the differences between the forms of CAD in the relationship with WBC count remain to be elucidated. To study these differences, we reviewed the health-checkup records from 1994 to 1999 for 6021 Japanese post office workers without any cardiovascular abnormalities. Baseline WBC counts of patients with acute coronary syndrome (ACS) were significantly higher than those of subjects free from coronary artery discase (mean +/- SD = 9210 +/- 2703/microL vs 6205 +/- 1635/microL, P<0.001), while the patients with stable angina pectoris (sAP) (6233 +/- 1528/microL) were similar to subjects without coronary artery disease in baseline WBC counts. Hypertension at the baseline was related to sAP (relative risk [95% CI] = 61.78 [17.29 to 78.66]) but not to ACS. Conversely, hypercholesterolemia and cigarette smoking were risk factors for ACS (relative risk [95% CI] = 11.48 [2.39 to 18.03] and 10.04 [3.00 to 12.12], respectively) but not for sAP. Multivariate logistic regression analysis found only WBC count (1000/microL) discriminated between ACS and sAP (P=0.038, odds ratio 2.049 [1.042-4.016]). We conclude that an elevated WBC count may be a risk factor of ACS but not sAP, and this finding is consistent with previous reports demonstrating the effects of WBCs in the destabilization of coronary artery plaques.
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...
 01:21
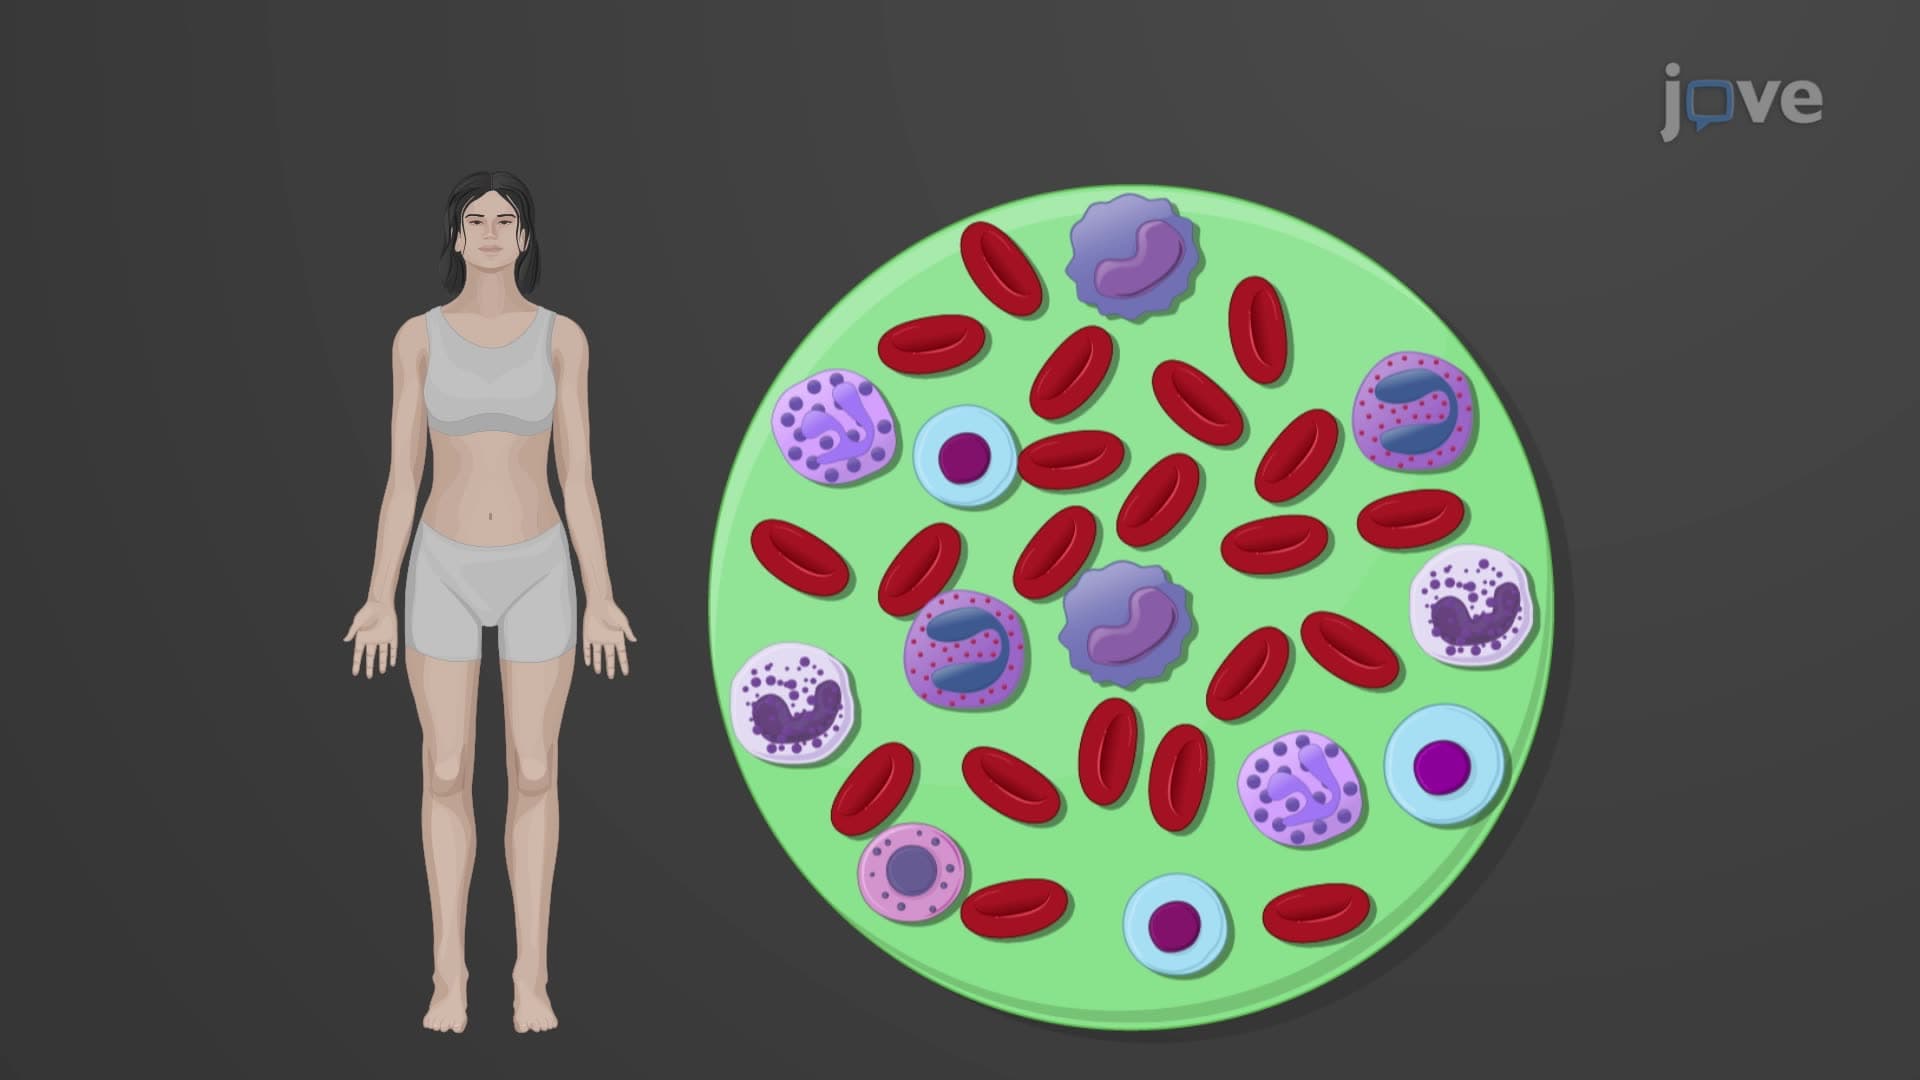
Structure and Function of Leukocytes
White blood cells protect the body...