[Comparison between radial and femoral approaches in ad hoc coronary angioplasty]
Related Experiment Video
Updated: Sep 26, 2026
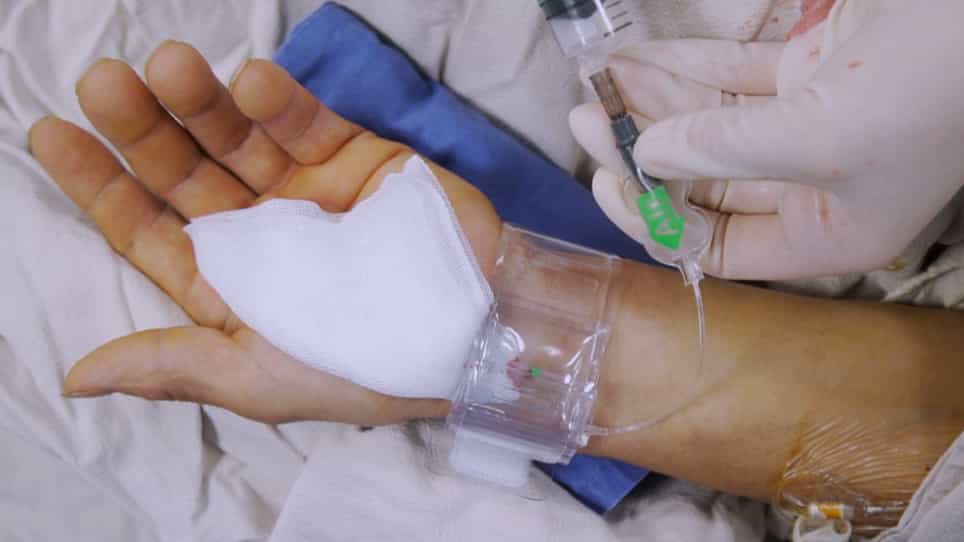
Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
F Larrazet1, F Philippe, T Folliguet
1Institut mutualiste Montsouris, département de pathologie cardiaque, 42, bd Jourdan, 75674 Paris. fabrice.larrazet@imm.fr

Insights
The radial approach for coronary angioplasty showed similar complication and adverse event rates compared to the femoral approach. However, radial procedures involved longer radiation times and higher radiation doses.
Area of Science:
- Cardiology
- Interventional Cardiology
- Medical Imaging
Background:
- Coronary angioplasty is a common procedure for treating coronary artery disease.
- Vascular access is typically achieved via the radial or femoral artery.
- Comparing the safety and efficacy of these approaches is crucial for patient outcomes.
Purpose of the Study:
- To compare the radial versus femoral approach for ad hoc coronary angioplasty.
- To evaluate immediate local and general complications.
- To assess major adverse cardiovascular events at 1 year and radiation exposure.
Main Methods:
- Prospective comparison of 591 patients undergoing coronary angioplasty.
- Group 1: Radial artery approach (n=328).
- Group 2: Femoral artery approach (n=263).
- Data collected on complications, adverse events, and radiation dose.
Main Results:
- Conversion rate from radial to femoral/humeral approach was 10%.
- Angioplasty, stenting, and dilatation failure rates were similar between groups.
- Immediate complication rates (2.5% radial vs 3.6% femoral) and 1-year MACE (13% both groups) were comparable.
- Radial approach associated with increased irradiation time (23 vs 17 min) and dose (242 vs 185 Gy.cm2).
Conclusions:
- Radial and femoral approaches demonstrate similar efficacy and safety profiles for coronary angioplasty.
- The radial approach requires a higher radiation dose and longer procedure time.
- An acceptable conversion rate from radial to femoral access exists.
Abstract:
Between September 1999 and June 2001, 591 patients required ad hoc coronary angioplasty. The authors compared the group of patients in whom the approach of first intent was radial (n = 328, 55%) with those in whom the femoral approach had been used (n = 263), in terms of immediate local (haematoma or thrombosis requiring surgical intervention or transfusion) and general complications (myocardial infarction, cerebrovascular accident), and major adverse cardiovascular events (infarction, angioplasty, bypass and death) at 1 year. The dose of ionising radiation during the procedures was also compared prospectively. The conversion rate from the radial (R) to the humeral or femoral (F) approach was 10%. The angioplasty, stenting, and stenting without dilatation failure rates were identical in the two groups (5% versus 5%, 0.6% versus 1.9%, 3% versus 4%, respectively). The average irradiation time was greater in the R group than in the F group (23 +/- 12 min vs 17 +/- 4 min, p < 0.001) as was the irradiation per surface unit (242 +/- 137 Gy.cm2 vs 185 +/- 117 Gy.cm2, p < 0.001). The immediate complication rate was comparable in the two groups (2.5% in group R vs 3.6% in group F) as was the major adverse cardiovascular event rate at 1 year (13% in both groups). The authors observed the same rate of immediate complications and late adverse cardiac events in patients undergoing coronary angioplasty followed by immediate angioplasty by the radial or femoral approaches with an acceptable conversion rate from the radial to the femoral approach. The procedures by the radial approach seem to be associated with a greater time and dosage of ionising radiation.

Related Concept Videos
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:28
Cardiac Catheterization I: Pre-Procedure Overview