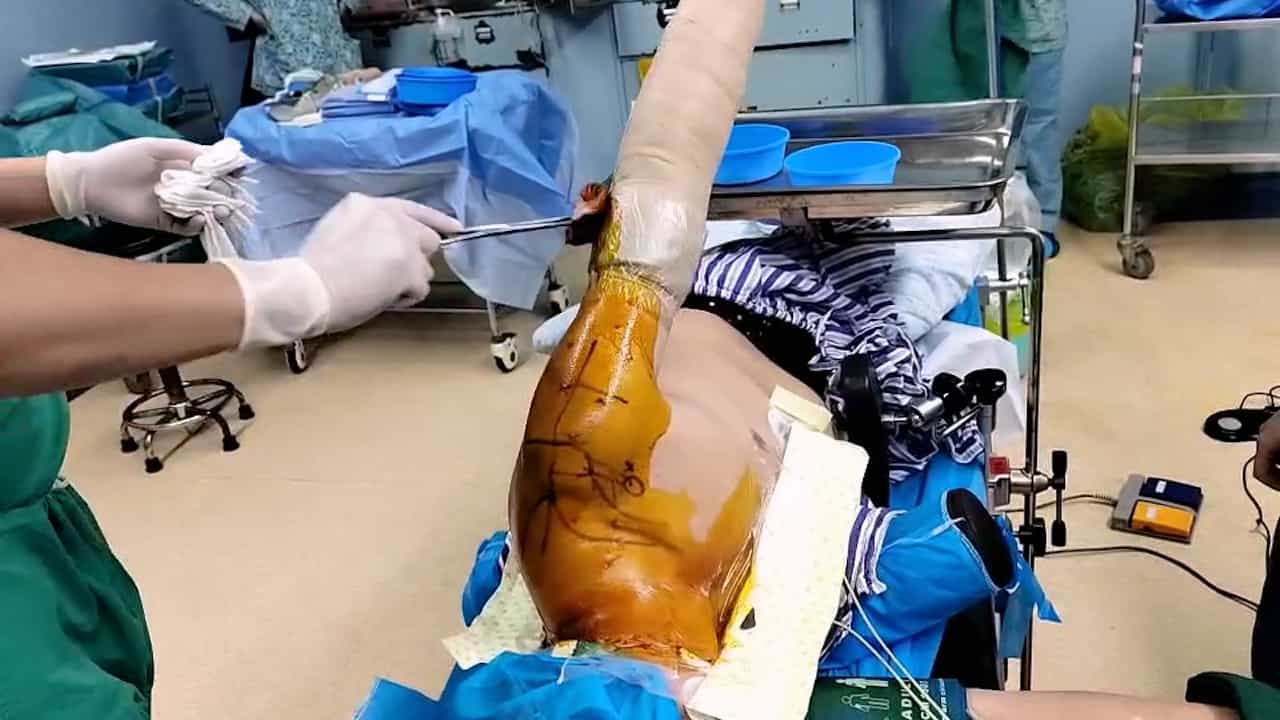
Related Experiment Video
Updated: Sep 26, 2026


Modified Long Head of Biceps Tendon Rerouting and Fixation as Partial Capsular Reconstruction for Massive Irreparable Rotator Cuff Tears
Published on: March 6, 2026
Posterolateral rotatory instability treated by a modified biceps rerouting technique: technical considerations and
Sung-Jae Kim1, Sang-Jin Shin, Jae-Hoon Jeong
1Department of Orthopaedic Surgery, Yonsei University College of Medicine, Seoul, Korea.

Purpose:
This study compared the clinical results of modified biceps femoris tenodesis with posterolateral rotatory instability (PLRI) injuries and PLRI combined with PCL injuries.
Type Of Study:
Case series.
Methods:
Of 46 patients treated for PLRI, 21 had isolated PLRI (group 1), and 25 had PLRI with PCL injuries (group 2). The most common cause of injury was motor vehicle accident. The PCL was reconstructed using an arthroscopic 1-incision technique. The advantages of the modified Clancy technique include fixation of the biceps tendon to the isometric position and reduced surgical damage to the iliotibial band by dissection to the lateral femoral epicondyle through the interval between the iliotibial band and biceps muscle.
Results:
All knees tested positive in the preoperative reverse pivot shift test, and 43 patients (93%) tested negative postoperatively. The side-to-side difference of an average external rotation thigh-foot angle (ERTFA) at both 30 degrees and 90 degrees of knee flexion was 15 degrees and 11 degrees in group 1 and 21 degrees and 26 degrees in group 2 preoperatively. Postoperative ERTFA tested at 30 degrees and 90 degrees of knee flexion were 10 degrees less than the uninvolved knee in both groups. At a mean follow-up of 40.3 months, the postoperative Lysholm knee score was 93.6 in group 1 and 90.4 in group 2. The postoperative HSS mean value was 91.1 in group 1 and 87.9 in group 2. A correction loss of more than 5 degrees was found in 3 patients of group 1 and in 5 patients of group 2 at an average 12 months after surgery. In 5 of 8 patients, severe scar tissues were found at the insertion site of the biceps tendon to the fibula during surgery. These tissues were associated with damage of the involved structures at the time of injury.
Conclusions:
Based on our experience, we recommend the modified biceps tenodesis for the reconstruction of both PLRI injuries and PLRI combined with PCL injuries except in patients with severe damage at the attachment site of the biceps tendon.