Pathophysiology and management of pediatric ascites
Related Experiment Video
Updated: Sep 26, 2026
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Mahmoud Sabri1, Miguel Saps, John M Peters
1Division of Pediatric Gastroenterology, Children's Hospital of Pittsburgh, 3705 Fifth Avenue, Pittsburgh, PA 15213, USA. John.Peters@chp.edu

Abstract:
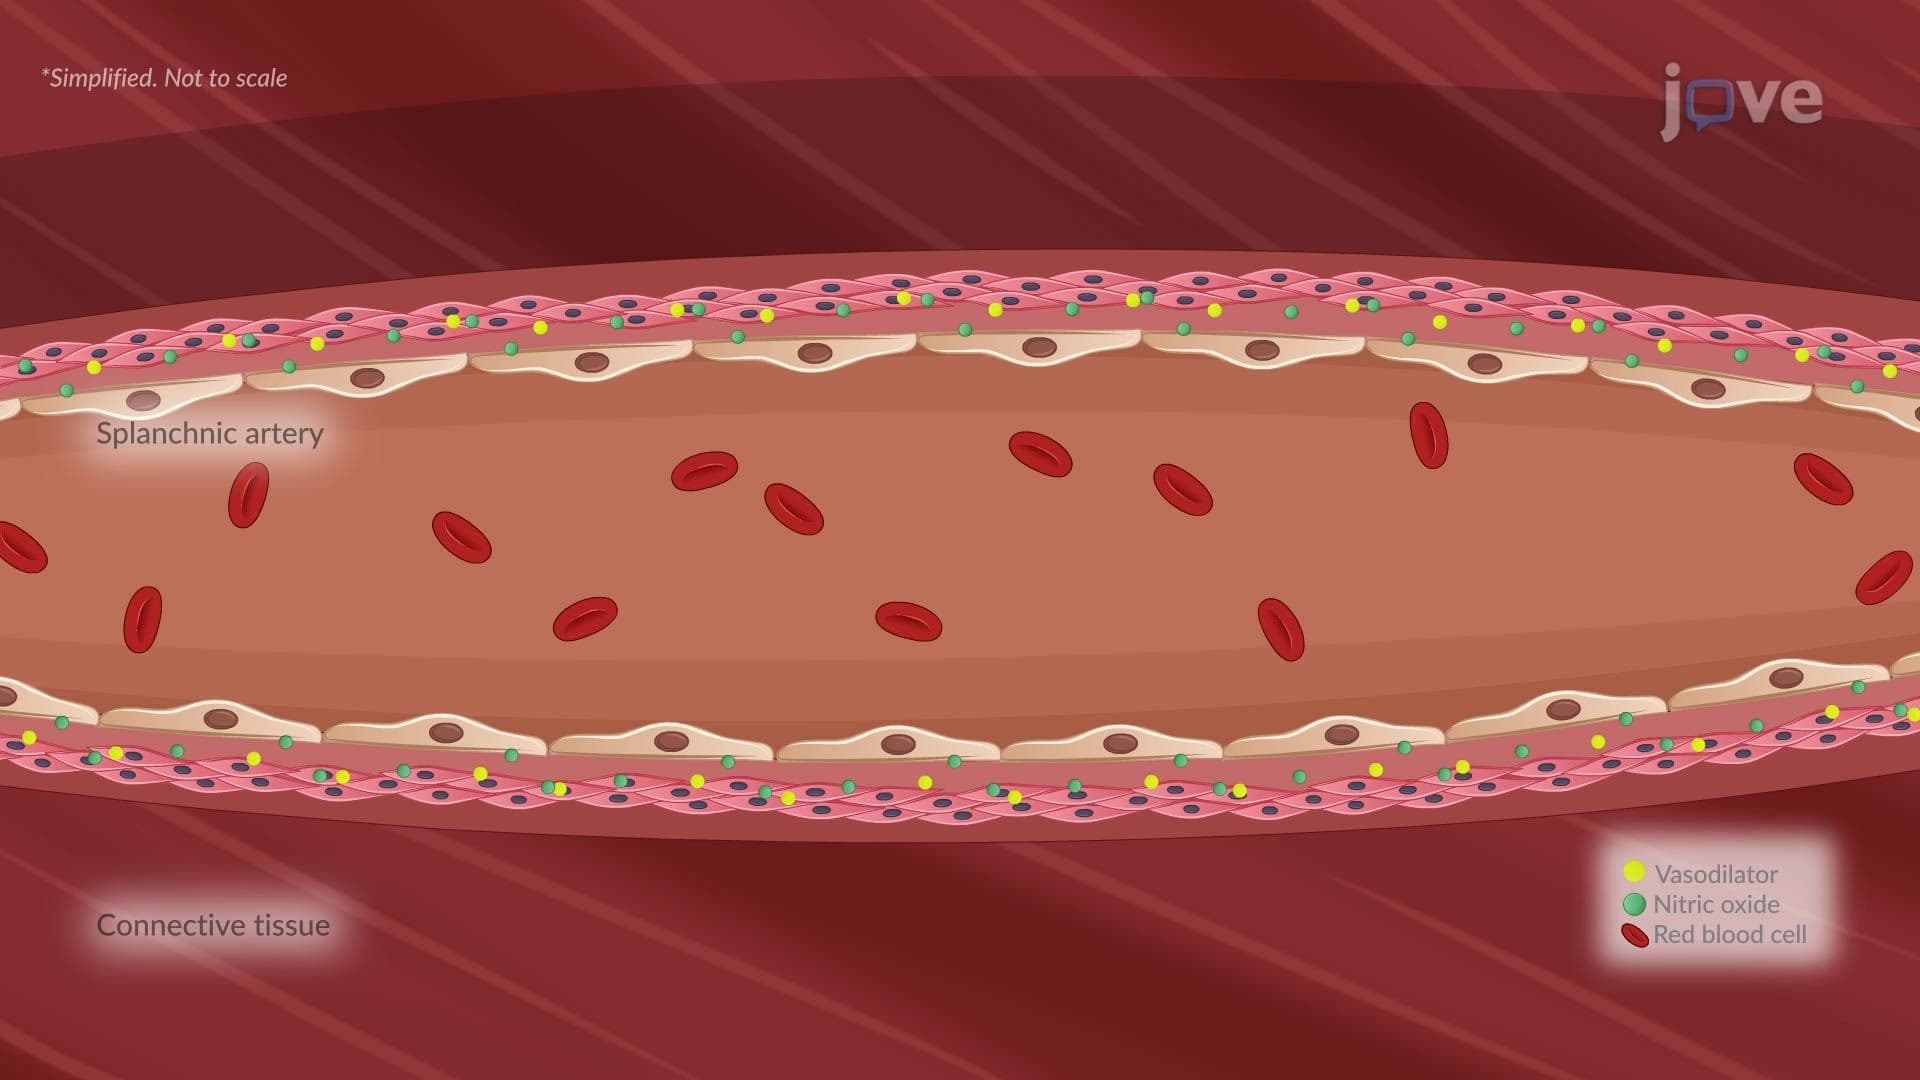
Ascites accumulation is the product of a complex process involving hepatic, renal, systemic, hemodynamic, and neurohormonal factors. The main pathophysiologic theories of ascites formation include the "underfill," "overflow," and peripheral arterial vasodilation hypotheses. These theories are not necessarily mutually exclusive and are linked at some level by a common pathophysiologic thread: The body senses a decreased effective arterial blood volume, leading to stimulation of the sympathetic nervous system, arginine-vasopressin feedback loops, and the renin-angiotensin-aldosterone system. Cornerstones of ascites management include dietary sodium restriction and diuretics. Spironolactone is generally tried initially, with furosemide added if clinical response is suboptimal. More refractory patients require large-volume paracentesis (LVP) accompanied by volume expansion with albumin. Placement of a transjugular intrahepatic portosystemic shunt is reserved for individuals with compensated liver function who require very frequent sessions of LVP. Peritoneovenous shunts are not used in contemporary ascites management. Liver transplantation remains the definitive therapy for refractory ascites. Although treatment of ascites fails to improve survival, it benefits quality of life and limits the development of such complications as spontaneous bacterial peritonitis.
Related Concept Videos
 01:19
Ascites
 01:24
Nephrotic Syndrome III : Nursing Management
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Peritoneal Dialysis III: Nursing Management