Related Experiment Video
Updated: Sep 26, 2026

Spectrophotometric Methods for the Study of Eukaryotic Glycogen Metabolism
Published on: August 19, 2021
Combined glucose-6-phosphate dehydrogenase and glucosephosphate isomerase deficiency can alter clinical outcome
Julia L Clarke1, Tom J Vulliamy, David Roper
1Department of Haematology, Faculty of Medicine, Imperial College of Science Technology and Medicine, Hammersmith Hospital, London, UK.

Insights
Glucosephosphate isomerase (GPI) deficiency causes hemolytic anemia. A novel GPI mutation was identified, but co-existing glucose-6-phosphate dehydrogenase (G6PD) deficiency altered the clinical outcome.
Area of Science:
- Genetics
- Biochemistry
- Hematology
Background:
- Glucosephosphate isomerase (GPI) deficiency is an autosomal recessive disorder causing nonspherocytic hemolytic anemia.
- The clinical severity of GPI deficiency can vary significantly among individuals.
Observation:
- A 4-year-old female presented with severe congenital hemolytic anemia and low red cell GPI activity.
- DNA analysis revealed a novel homozygous 921C to G mutation in the GPI gene (Phe307Leu).
- This patient exhibited higher red cell GPI activity than a second patient with the same mutation but a more severe phenotype.
Findings:
- The first patient also had reduced red cell glucose-6-phosphate dehydrogenase (G6PD) activity (50% of normal).
- Molecular studies showed heterozygosity for the G6PD Viangchan mutation and skewed X-chromosome inactivation.
- This pattern led to near-exclusive expression of the G6PD mutation, a variant typically not causing chronic hemolysis.
Implications:
- Combined GPI and G6PD deficiencies may lead to a distinct clinical presentation compared to isolated defects.
- Understanding these combined metabolic effects is crucial for predicting and managing hemolytic anemia.
- This case highlights the complex interplay of genetic factors in determining disease severity.
Abstract:
Glucosephosphate isomerase (GPI) deficiency in humans is an autosomal recessive disorder, which results in nonspherocytic hemolytic anemia of variable clinical expression. A 4-year-old female with severe congenital hemolytic anemia had low red cell GPI activity of 15.5 IU/g Hb (50% of normal mean) indicating GPI deficiency. Subsequent DNA sequence analysis revealed a novel homozygous 921C to G mutation in the GPI gene sequence, predicting a Phe307 to Leu replacement. Strikingly, the red cell GPI activity in this patient was higher than that found in a second patient expressing the same GPI variant, with a more severe clinical phenotype. We propose that the hemolysis in the first patient may be modified by an accompanying deficiency of glucose-6-phosphate dehydrogenase (G6PD). The proband's red cell G6PD activity was reduced at 4.5 IU/g Hb (50% of normal mean) and molecular studies revealed heterozygosity for the G6PD Viangchan mutation and a skewed pattern of X-chromosome inactivation, producing almost exclusive expression of the mutated allele. The G6PD Viangchan variant is characterised by severe enzyme deficiency, but not chronic hemolysis. This study suggests that the metabolic consequences of a combined deficiency of GPI and G6PD might be responsible for a different clinical outcome than predicted for either defect in isolation.


Related Concept Videos
 01:20
Inborn Errors of Metabolism
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:21
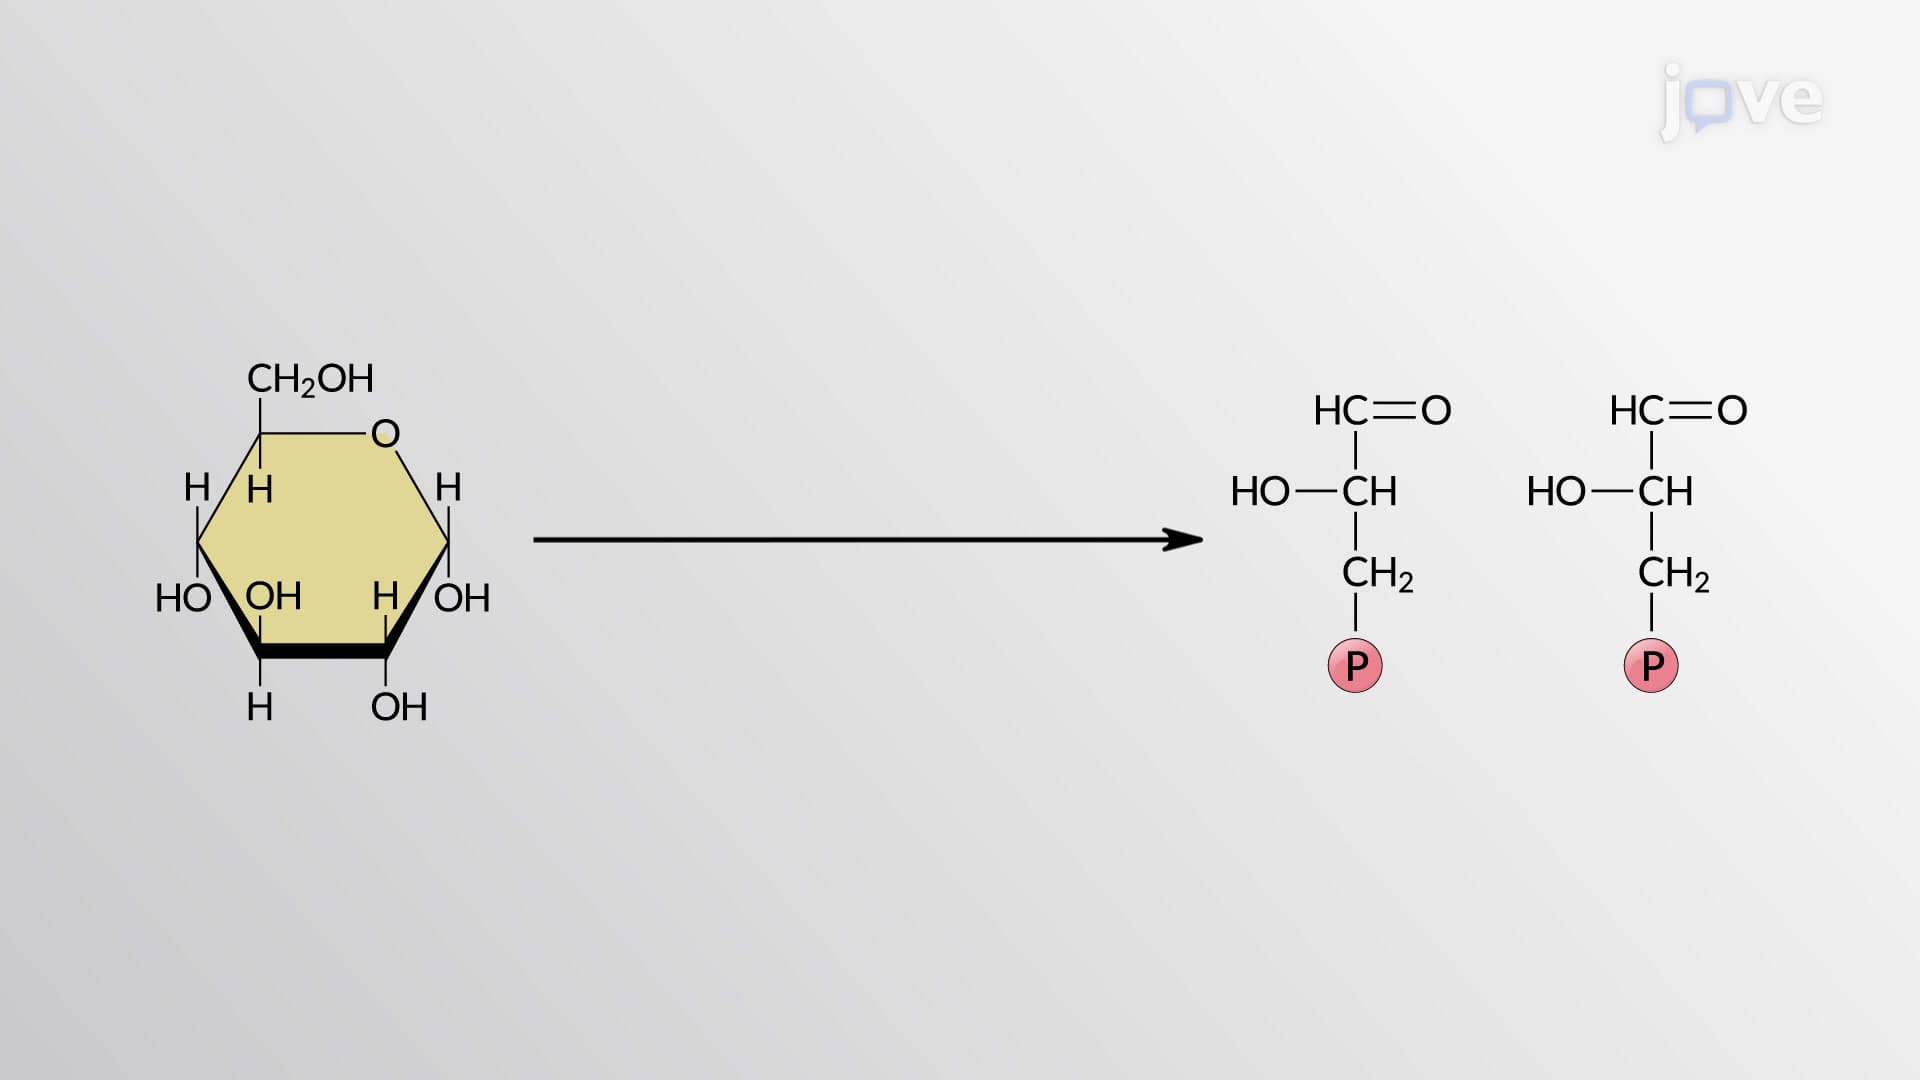
Glycolysis: Preparatory Phase
 01:24
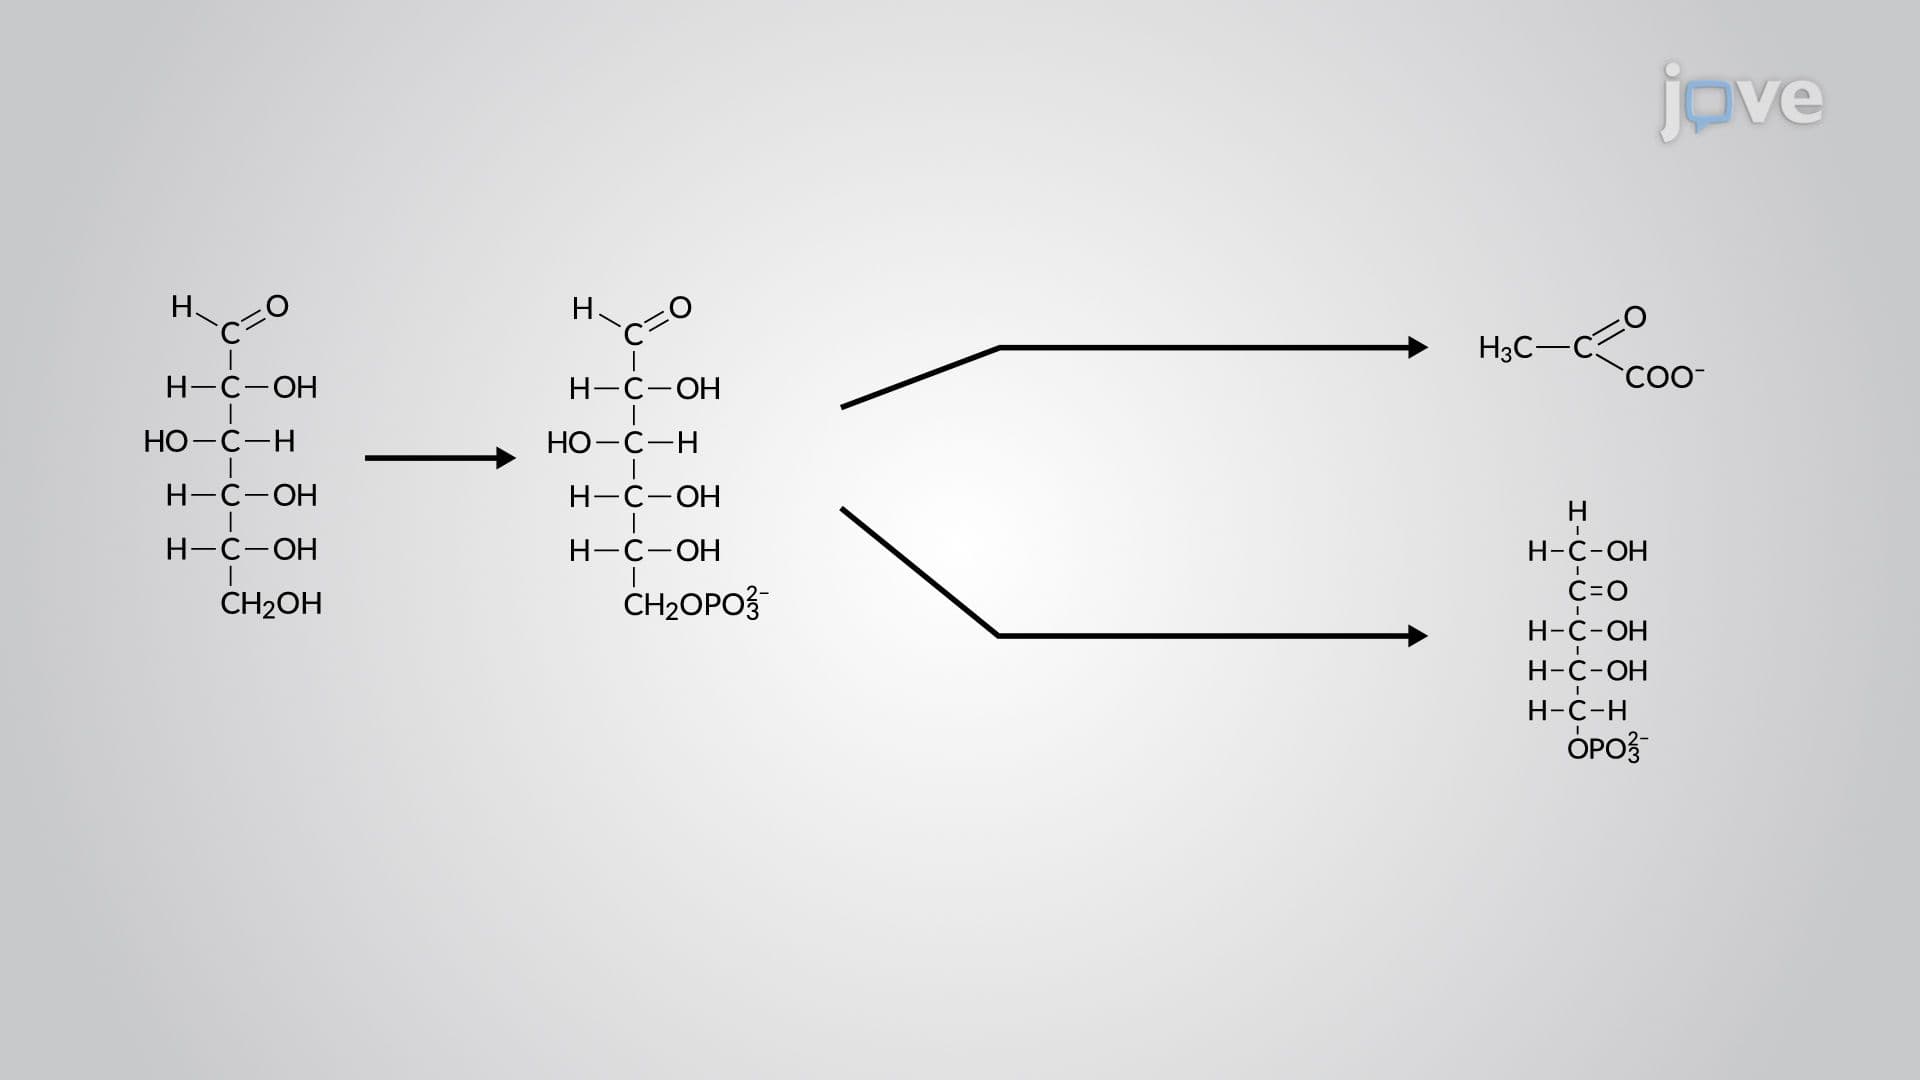
Other Glycolytic Pathways
 01:29
Hyperglycemia
 01:20
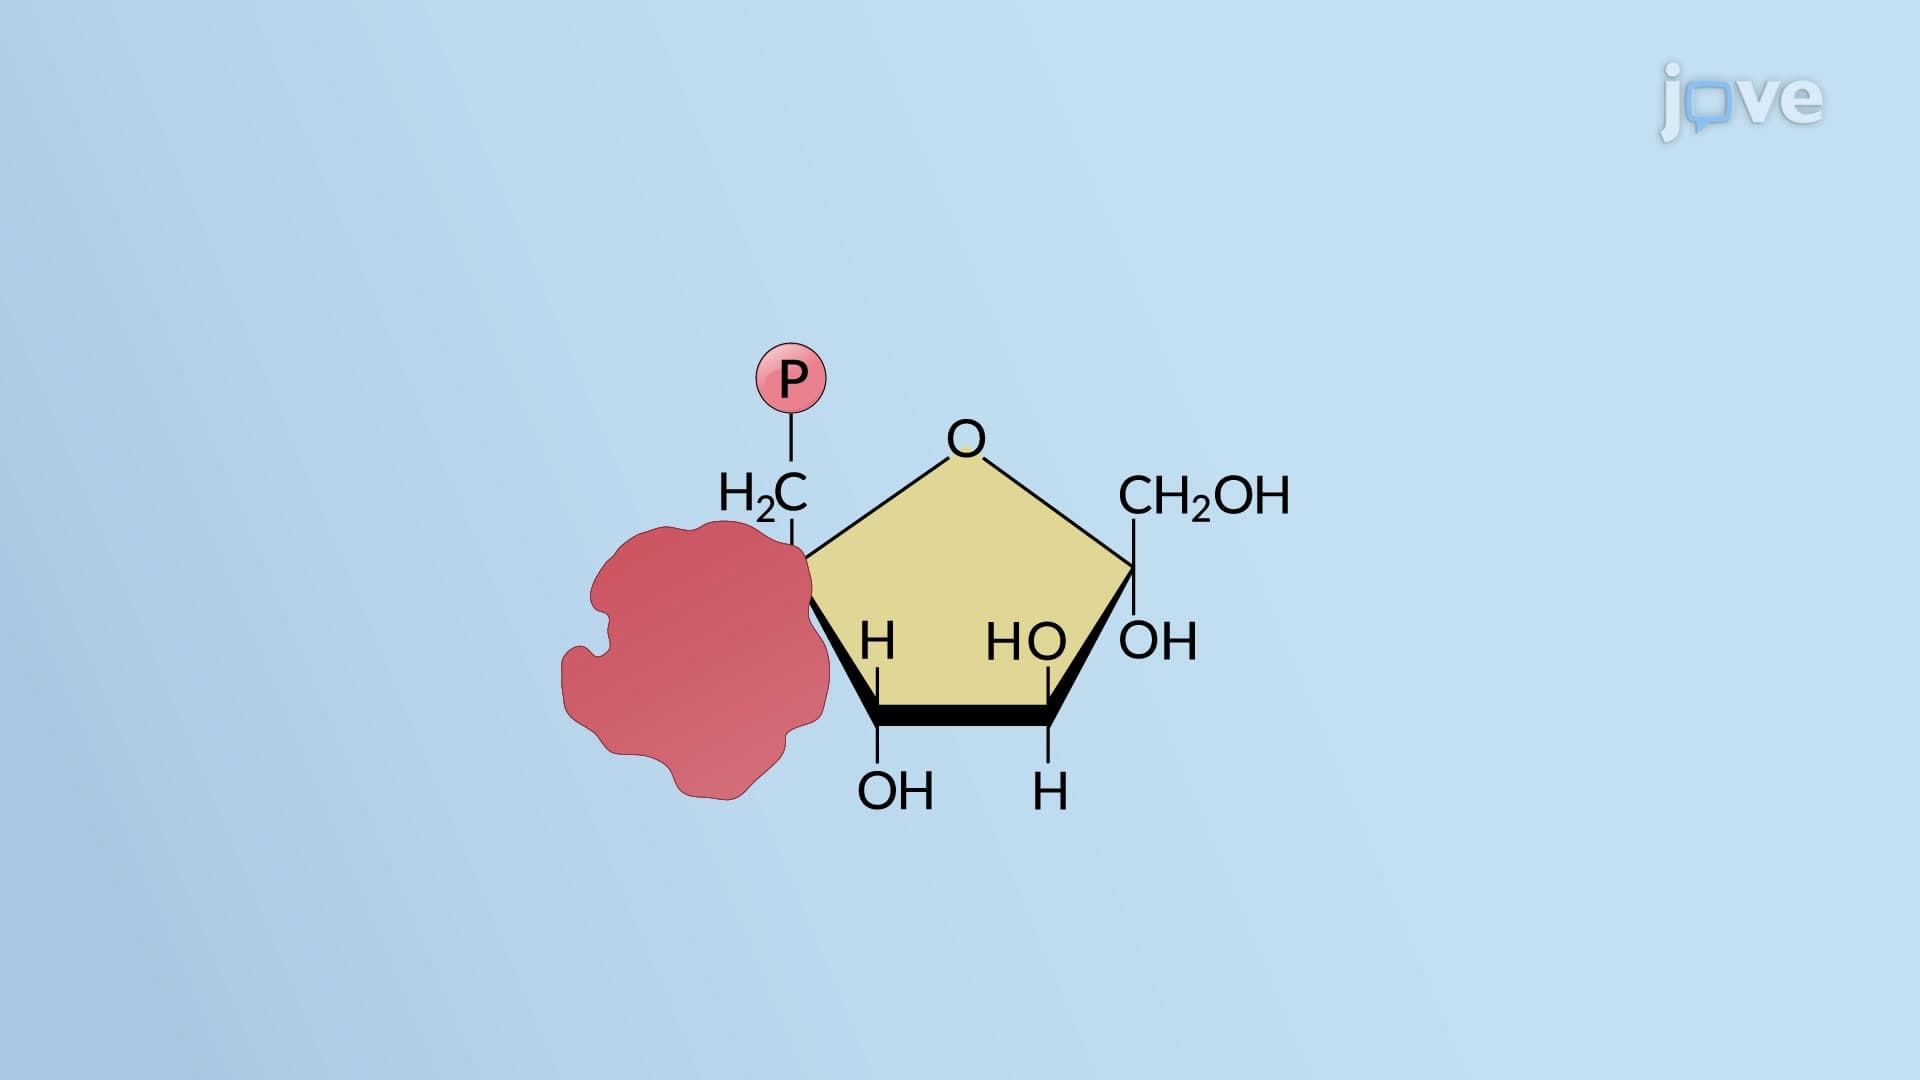
Energy-requiring Steps of Glycolysis