Related Experiment Video
Updated: Sep 26, 2026


Induction of Nephrotic Syndrome in Mice by Retrobulbar Injection of Doxorubicin and Prevention of Volume Retention by Sustained Release Aprotinin
Published on: May 6, 2018
Aminoglycoside dosages and nephrotoxicity: quantitative relationships
Florent Rougier1, Michel Ducher, Michel Maurin
1UMR CNRS 5558-ADCAPT Service Pharmaceutique, Hôpital Antoine Charial, Francheville, France.

Objective:
To develop a model that relates the probability of occurrence of nephrotoxicity to the cumulative area under the curve (AUC) of amikacin serum concentration.
Design And Patients:
This was a retrospective study of two groups of patients in whom nephrotoxicity was observed after administration of amikacin. The first group consisted of patients treated with once-daily administration (ODA) [n = 13]. The second group consisted of patients treated with twice-daily administration (TDA) [n = 22].
Main Outcome Measures:
The probability of nephrotoxicity occurrence.
Results:
The model is a powerful tool to represent and describe the influence of the dosage regimen on aminoglycoside nephrotoxicity. The onset of nephrotoxicity is delayed in the ODA group (p = 0.01) for the same total daily dose among the two groups. The cumulative serum AUC values at onset of nephrotoxicity were greater for the ODA group (p = 0.029). In addition, for the same probability of nephrotoxicity occurrence (50%), the cumulative AUC for the ODA dosage regimen is 2 613 mg. h/L versus only 1 521 mg. h/L for the TDA dosage regimen. The difference in nephrotoxicity between ODA and TDA is greatest for a cumulative AUC of 2 495 mg. h/L, which corresponds to standard therapy with amikacin 900 mg/day during a 7-day period, i.e. 15 mg/kg/day for a 60kg patient with normal renal function (initial creatinine clearance >80 mL/min). For an AUC above 2 495 mg. h/L, the difference in nephrotoxicity decreases slowly to zero. This result means that ODA is especially justified when the treatment is administered over a short duration, i.e. less than 7 days.
Conclusions:
The utility of selecting ODA in order to obtain less nephrotoxicity in comparison with TDA is therefore not established when the treatment is prolonged. In clinical use, the choice of the dosage regimen is not clear-cut, and both expected efficacy and expected toxicity must be taken into account in order to obtain an overall optimisation of each patient's therapy.

Related Concept Videos
 01:20
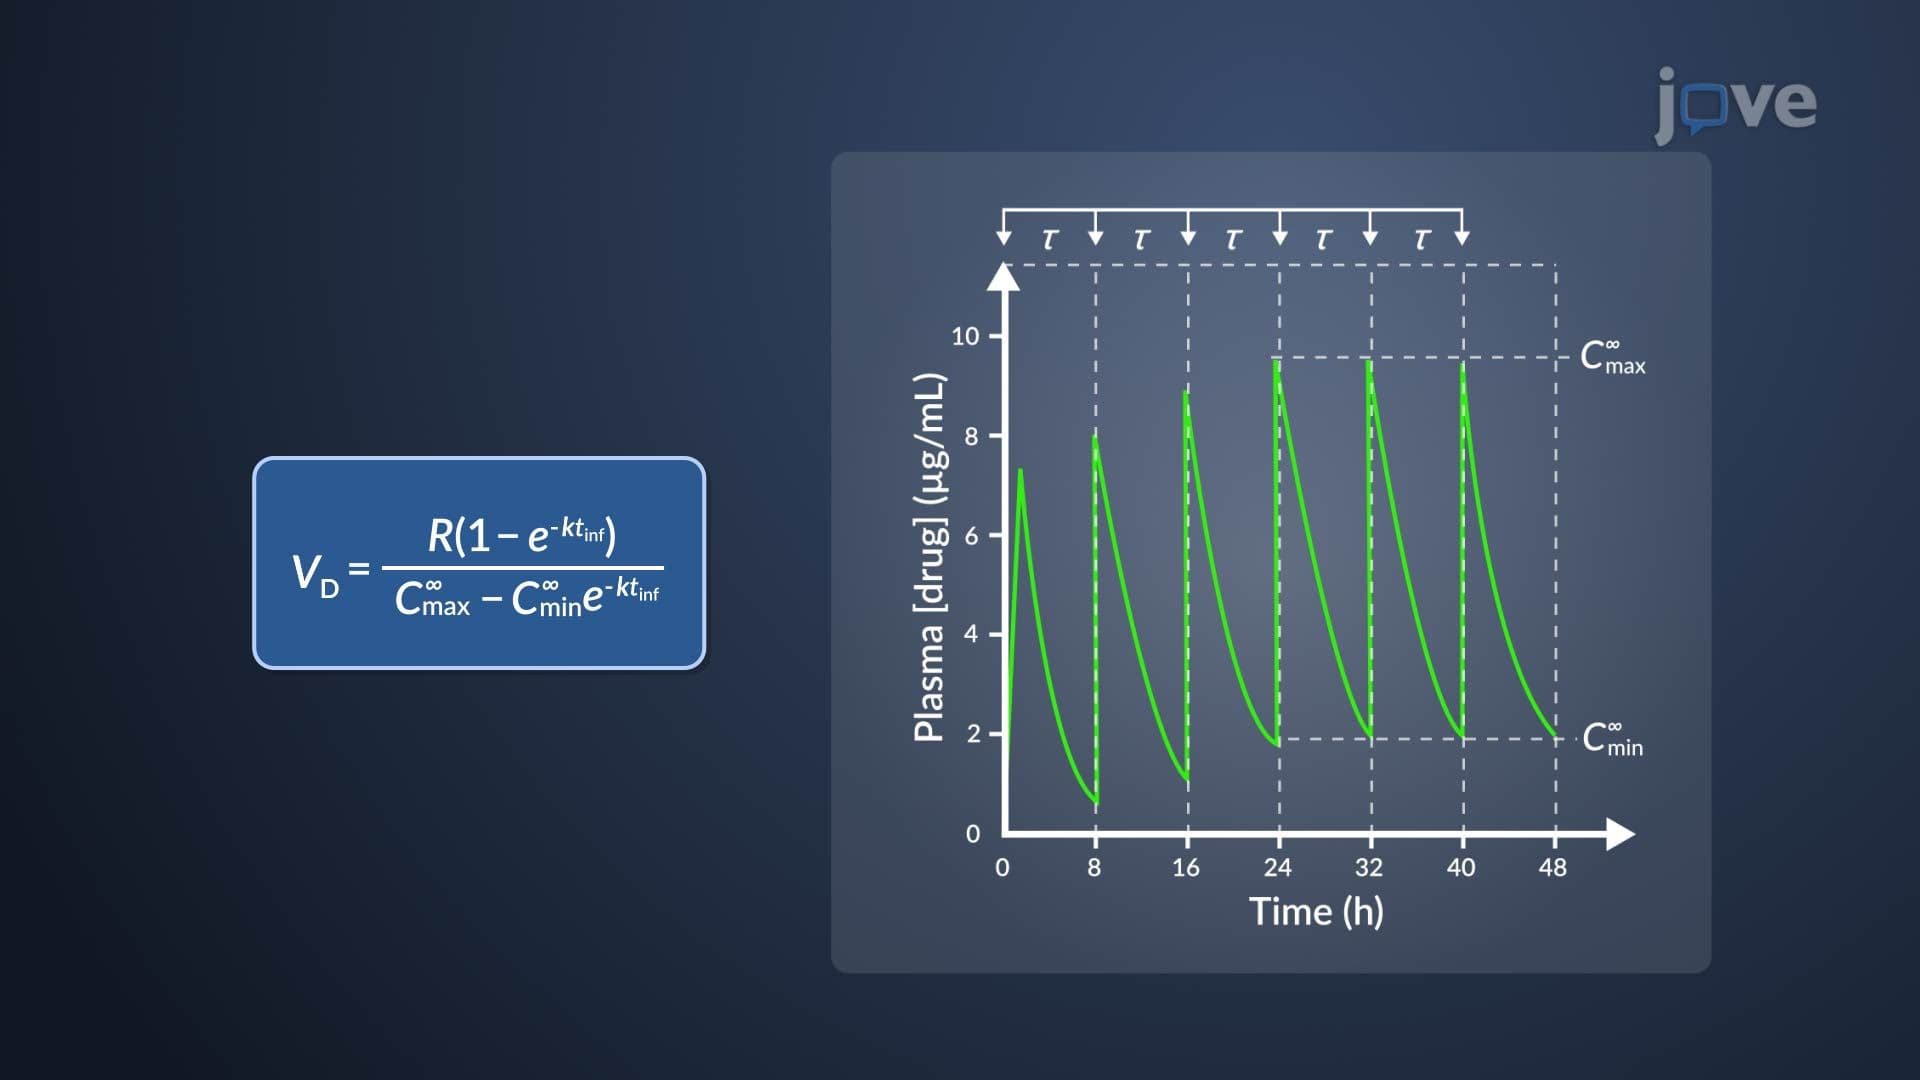
Estimation of k and VD of Aminoglycosides
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:15
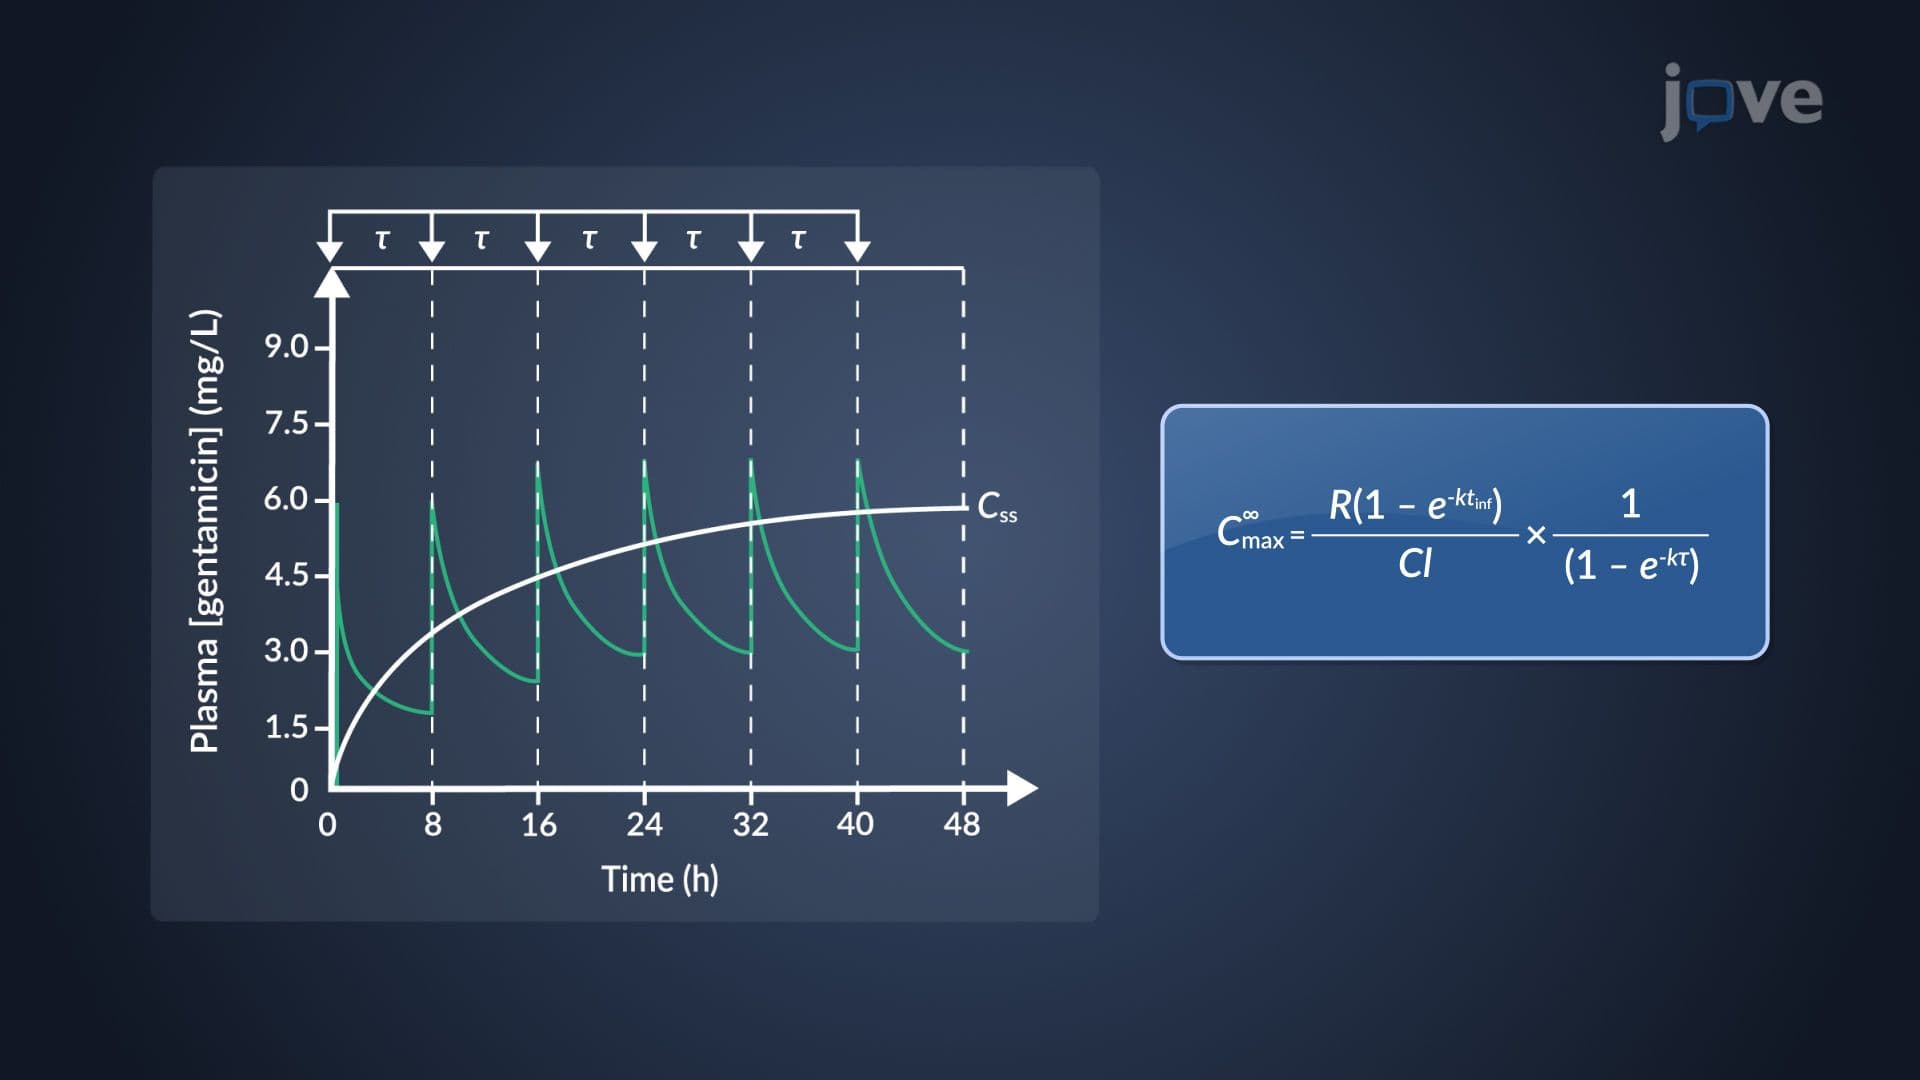
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:23
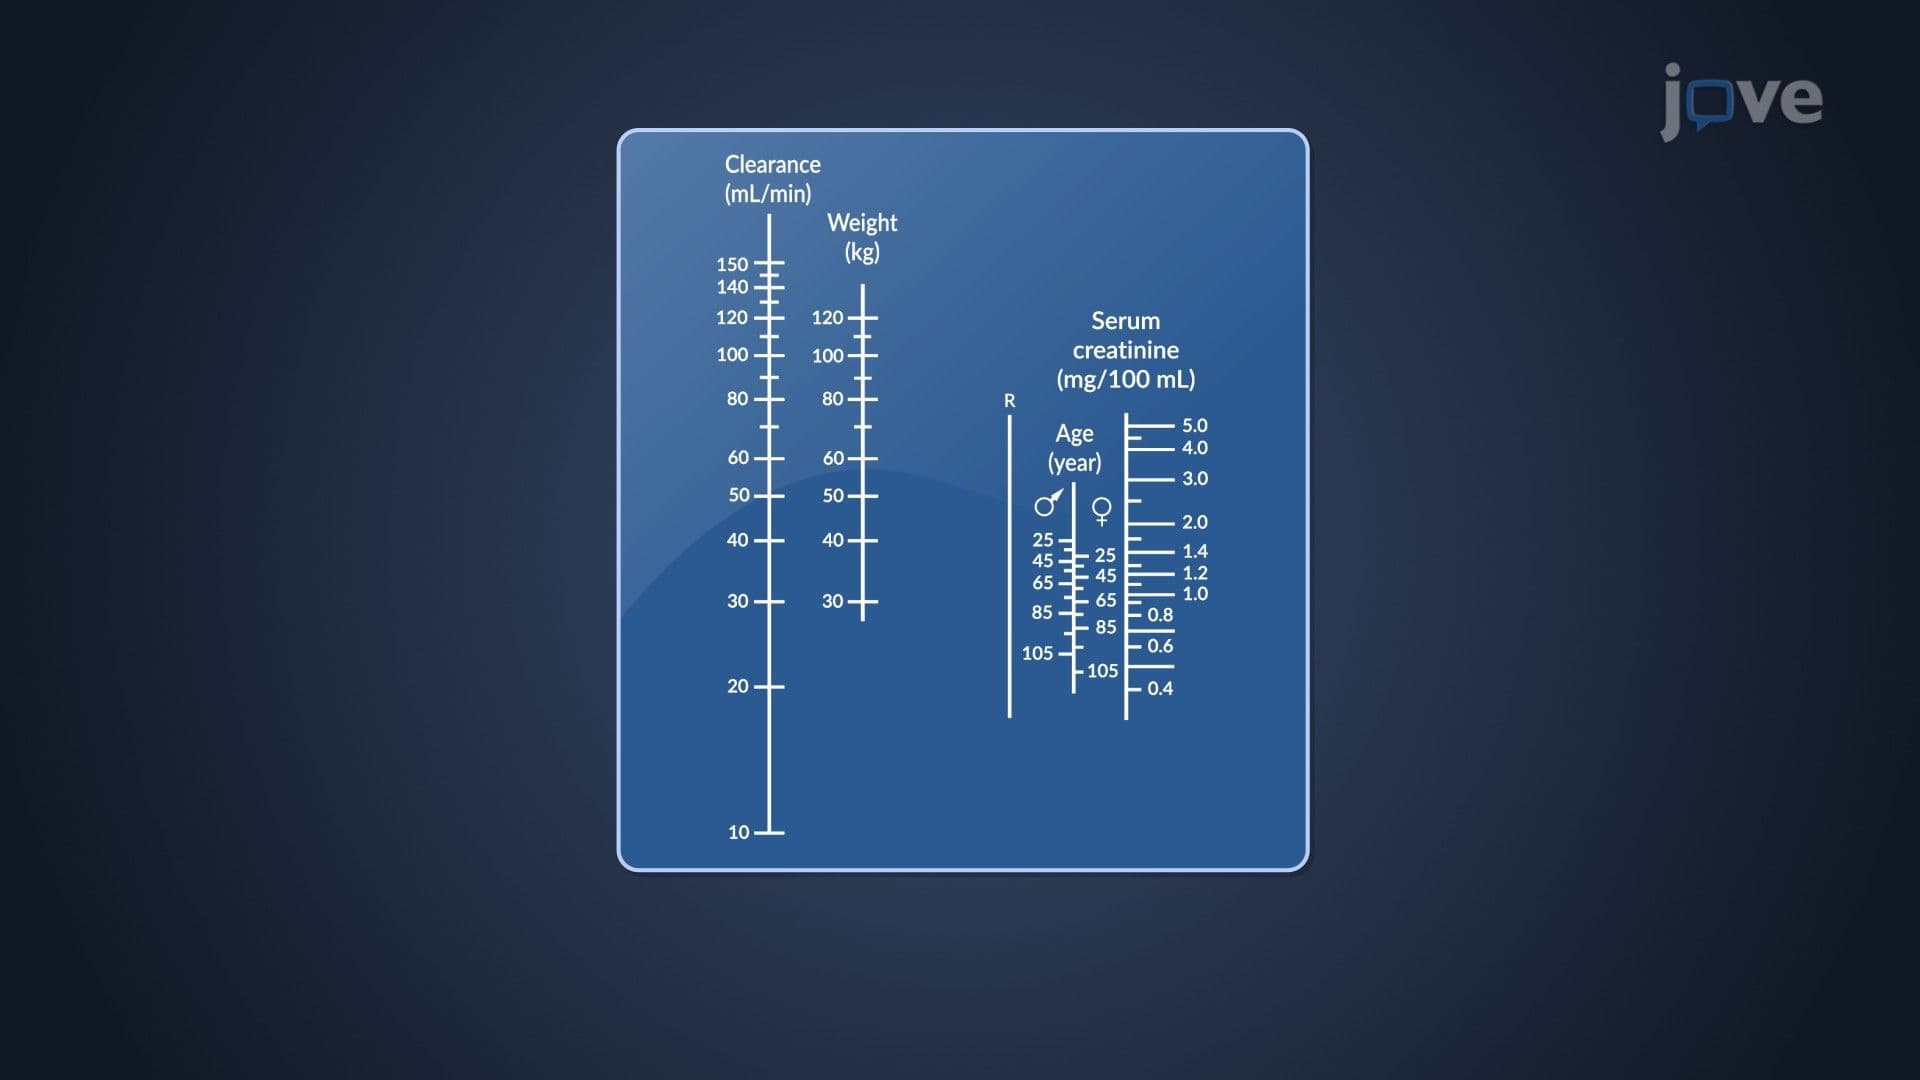
Dosage Regimen Designs: Nomograms and Tabulations