Related Experiment Video
Updated: Sep 26, 2026
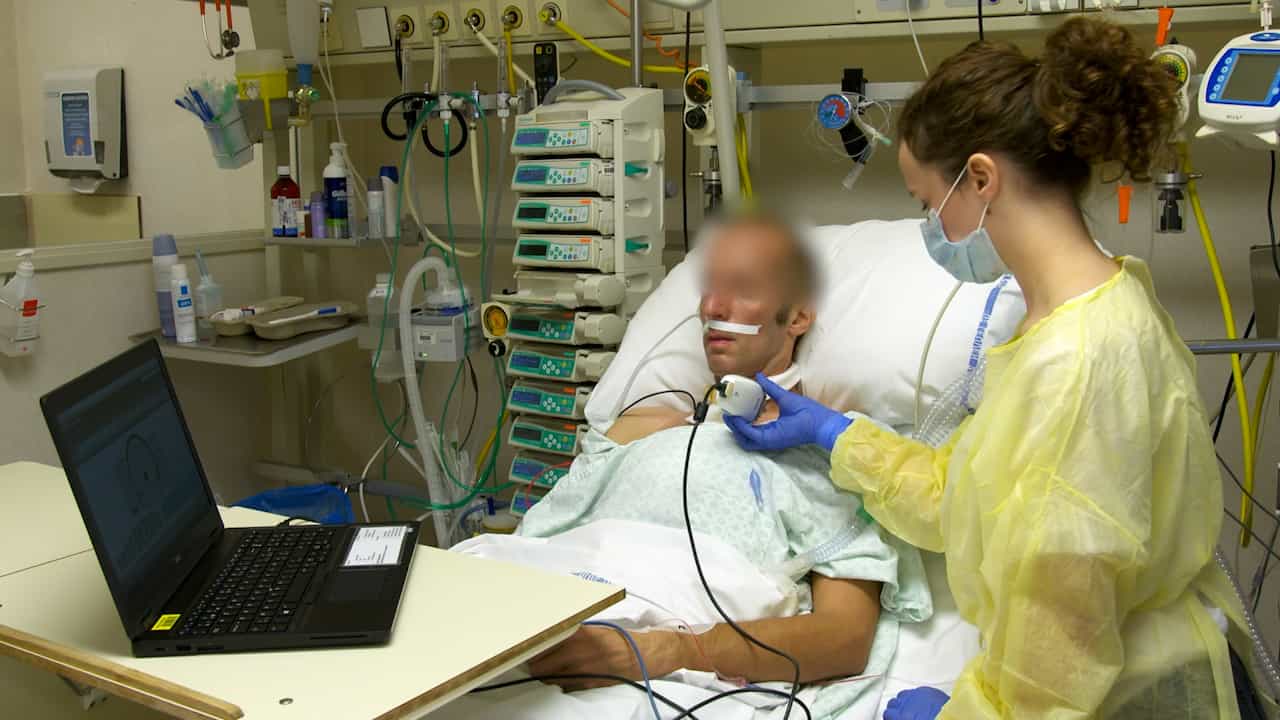

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Time course of expiratory flow limitation in COPD patients during acute respiratory failure requiring mechanical
Valentina Alvisi1, Anna Romanello, Michel Badet
1Department of Anesthesiology, University of Ferrara, Italy.

Study Objectives:
(1) To determine the incidence of expiratory flow limitation (FL) at ICU admission, at the time of extubation, and at ICU discharge in intubated patients with COPD receiving mechanical ventilation for acute respiratory failure (ARF); and (2) to assess the feasibility of inspiratory capacity (IC) as an indication of pulmonary dynamic hyperinflation in this setting.
Design:
Prospective, observational pilot study with physiologic measurements performed at ICU admission and during the weaning process driven by the clinician. A 60-min T-tube trial was initiated once criteria for weaning were present. The decision to extubate or reventilate patients was made by the clinician at the end of this session. Assessment of failure or success of T-tube trials was performed independently.
Setting:
A 25-bed ICU of a tertiary teaching university hospital.
Patients:
Over a 13-month period, 25 intubated patients with COPD receiving mechanical ventilation for ARF were included.
Interventions:
None.
Measurements And Results:
At ICU admission, FL assessed by the negative expiratory pressure test was measured under passive ventilatory conditions at the baseline ventilatory settings, on zero end-expiratory pressure, and in a semirecumbent position. During weaning, FL, respiratory pattern, and IC were measured during T-tube trials, before extubation, 1 h after extubation, and at ICU discharge. At ICU admission, 24 of 25 patients presented FL with, on average, 73 +/- 22% of the tidal volume. Ten patients were unavailable for follow-up due to death (n = 6) unplanned extubation (n = 3), or refusal (n = 1), so that only 15 patients completed the whole protocol (all 15 patients were extubated). For these 15 patients, the incidence of FL was 93% at ICU admission, 47% before extubation, and 40% at ICU discharge. IC was significantly greater at ICU discharge than before extubation (36 +/- 11% predicted vs 44 +/- 12% predicted, p < 0.01) and in successful T-tube trials compared with unsuccessful T-tube trials (38 +/- 13% predicted vs 24 +/- 8% predicted, p < 0.01).
Conclusions:
The incidence of expiratory FL is high in patients with COPD receiving mechanical ventilation, and is reduced during aggressive therapy when the patient is placed on mechanical ventilatory support and the time that weaning begins during the ICU stay. IC was lower in patients in whom weaning was unsuccessful. Further large-scale studies are required to confirm these preliminary results.
Related Concept Videos
 01:30
Acute Respiratory Failure-III
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:29
Mechanical Ventilation I: Indication and Settings