Related Experiment Video
Updated: Sep 26, 2026

Quantitating Iron Transport Across the Mouse Placenta In Vivo Using Nonradioactive Iron Isotopes
Published on: May 10, 2022
Excretion of foetal bilirubin by the rat placenta-maternal liver tandem
O Briz1, R I R Macias, M A Serrano
1Department of Physiology and Pharmacology, University of Salamanca, Salamanca, Spain.

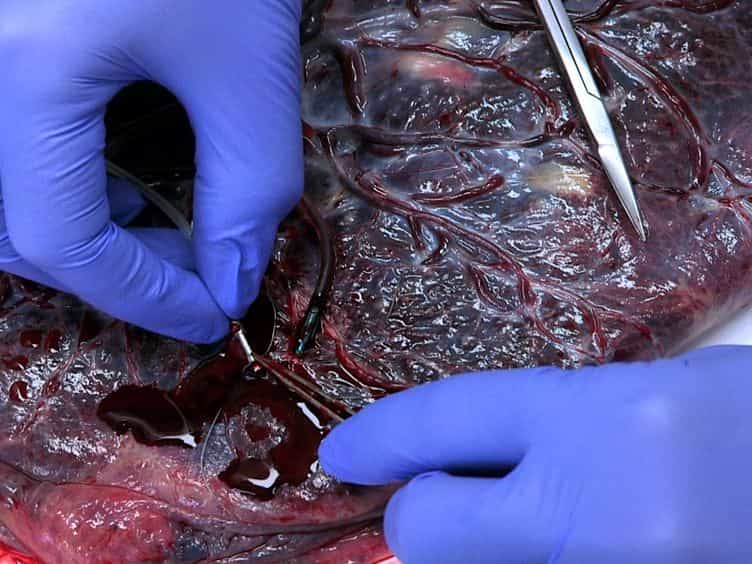
Using plasma membrane vesicles from human trophoblast, carrier-mediated transport of unconjugated bilirubin (UCBR) has been reported. In the present work, using the in situ perfused rat placenta-maternal liver tandem, the relevance of this pathway in vivo was investigated. After single-pass perfusion of rat placenta through the umbilical artery with 0.25 micromol [(3)H]-UCBR, approximately 15 per cent of it was taken up by the placenta, detected in maternal serum (>96 per cent was unconjugated) and subsequently secreted into maternal bile (approximately 15 per cent of administered dose; >88 per cent was glucuronidated bilirubin). Co-administration through the umbilical artery of 0.25 micromol [(3)H]-UCBR and 2.5 micromol unlabelled UCBR, bromosulfophthalein, cholic acid or biliverdin IXalpha, reduced [(3)H]-UCBR placenta uptake, and the amount of radioactivity found in the maternal serum and bile. Co-administration into maternal jugular vein of 0.1 micromol [(3)H]-UCBR-a dose 3-fold higher than that reaching the maternal compartment in placenta perfusion experiments-and 1.0 micromol bromosulfophthalein, cholic acid or biliverdin IXalpha, resulted in no marked inhibition of the amount of radioactivity bile output. When antipyrine and [(3)H]-UCBR were continuously co-infused to the mother, similar antipyrine concentrations in maternal and foetal serum were reached in approximately 15 min, while progressive increase in [(3)H]-bilirubin concentrations in maternal serum above 70 microM was accompanied by a very low transfer of this compound into foetal compartment where [(3)H]-bilirubin concentrations were always <10 microM. These results suggest that the transfer of UCBR across the rat placenta occurs, without biotransformation, via a foetal-to-maternal mainly unidirectional pathway that can be cis-inhibited by UCBR and other cholephilic organic anions.
Using plasma membrane vesicles from human trophoblast, carrier-mediated transport of unconjugated bilirubin (UCBR) has been reported. In the present work, using the in situ perfused rat placenta-maternal liver tandem, the relevance of this pathway in vivo was investigated. After single-pass perfusion of rat placenta through the umbilical artery with 0.25 micromol [(3)H]-UCBR, approximately 15 per cent of it was taken up by the placenta, detected in maternal serum (>96 per cent was unconjugated) and subsequently secreted into maternal bile (approximately 15 per cent of administered dose; >88 per cent was glucuronidated bilirubin). Co-administration through the umbilical artery of 0.25 micromol [(3)H]-UCBR and 2.5 micromol unlabelled UCBR, bromosulfophthalein, cholic acid or biliverdin IXalpha, reduced [(3)H]-UCBR placenta uptake, and the amount of radioactivity found in the maternal serum and bile. Co-administration into maternal jugular vein of 0.1 micromol [(3)H]-UCBR-a dose 3-fold higher than that reaching the maternal compartment in placenta perfusion experiments-and 1.0 micromol bromosulfophthalein, cholic acid or biliverdin IXalpha, resulted in no marked inhibition of the amount of radioactivity bile output. When antipyrine and [(3)H]-UCBR were continuously co-infused to the mother, similar antipyrine concentrations in maternal and foetal serum were reached in approximately 15 min, while progressive increase in [(3)H]-bilirubin concentrations in maternal serum above 70 microM was accompanied by a very low transfer of this compound into foetal compartment where [(3)H]-bilirubin concentrations were always <10 microM. These results suggest that the transfer of UCBR across the rat placenta occurs, without biotransformation, via a foetal-to-maternal mainly unidirectional pathway that can be cis-inhibited by UCBR and other cholephilic organic anions.

Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:25
Jaundice
 01:23
Drug Elimination: Non-Renal Routes
 01:10
Drug Excretion: Miscellaneous Routes
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...
 01:16
Hepatic Drug Excretion: Influencing Factors