Related Experiment Video
Updated: Sep 25, 2026

Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021
Spontaneous fatal intracranial hemorrhage in a child with Evans syndrome
Antonio Ruggiero1, Marco Piastra, Anna Maria Casadei Pistilli
1Division of Pediatric Oncology, Catholic University of Rome, Rome, Italy.

Insights
Spontaneous intracranial hemorrhage is a rare, life-threatening complication in children with Evans syndrome. This case highlights the risk even with moderate chronic thrombocytopenia, emphasizing the need for prompt recognition and aggressive management.
Area of Science:
- Pediatric Hematology
- Neurology
- Critical Care Medicine
Background:
- Evans syndrome is a chronic, relapsing autoimmune disorder characterized by autoimmune hemolytic anemia and immune thrombocytopenia.
- It can be refractory to conventional treatments, posing significant management challenges.
- Intracranial hemorrhage is an infrequent but severe complication, particularly in pediatric cases.
Purpose of the Study:
- To report a fatal case of spontaneous intracranial hemorrhage in a child with chronic Evans syndrome.
- To underscore the potential for this life-threatening event even in cases of moderate chronic thrombocytopenia.
- To highlight the critical need for early diagnosis and aggressive intervention for this rare complication.
Main Methods:
- Case report of a pediatric patient with a history of chronic Evans syndrome.
- Detailed clinical presentation, diagnostic workup, and management course.
- Review of literature regarding intracranial hemorrhage in pediatric Evans syndrome.
Main Results:
- The patient experienced a fatal spontaneous intracranial hemorrhage.
- The hemorrhage occurred despite a moderate grade of chronic thrombocytopenia.
- This outcome illustrates the unpredictable and severe nature of neurological complications in Evans syndrome.
Conclusions:
- Spontaneous intracranial hemorrhage is a rare but devastating complication of pediatric Evans syndrome.
- The risk exists even with moderate thrombocytopenia, necessitating heightened clinical vigilance.
- Prompt recognition and aggressive management strategies are crucial for improving outcomes in affected children.
Abstract:
Evans syndrome is a chronic and recurrent disease often resistant to multiagent therapy. Spontaneous intracranial hemorrhage is a rare but life-threatening complication in children with Evans syndrome. The authors report the fatal course of a child with chronic thrombocytopenia who presented a spontaneous intracranial hemorrhage. The case indicates that this potentially fatal event may occur even in children with a moderate grade of chronic thrombocytopenia. Early recognition and aggressive management is required for an adequate management of this rare complication.

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
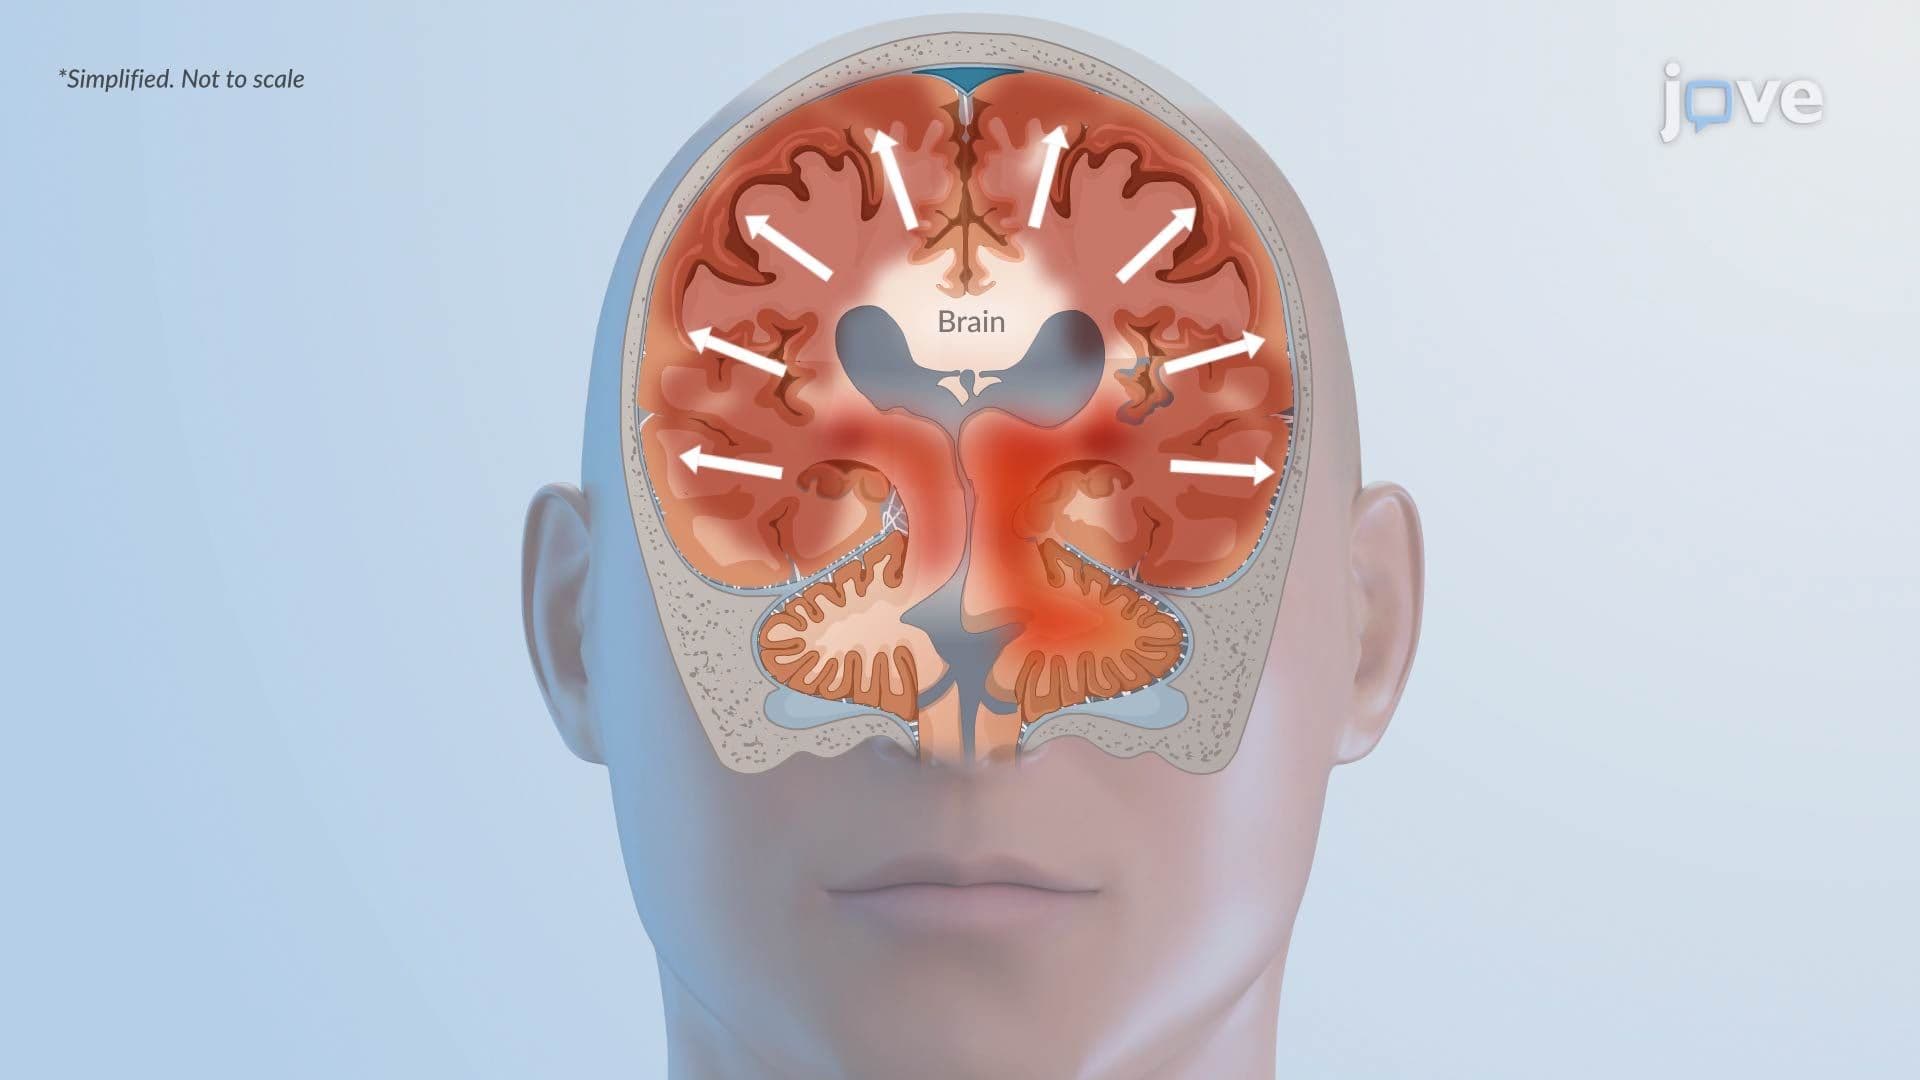 01:21
Cytotoxic Edema: Pathophysiology