Related Experiment Video
Updated: Sep 16, 2026
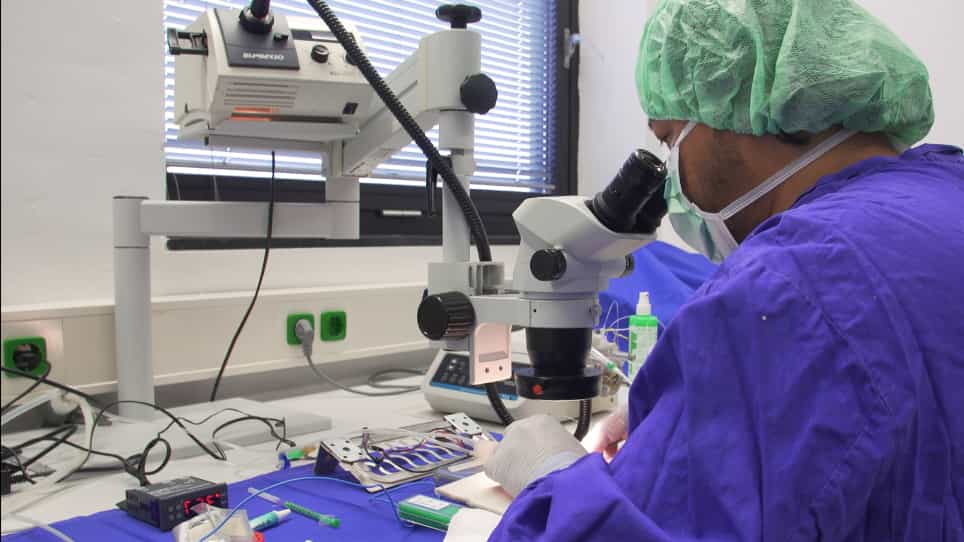

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Neurodevelopmental outcome of infants supported with extracorporeal membrane oxygenation after cardiac surgery
Shannon E G Hamrick1, David B Gremmels, Corinne A Keet
1Department of Pediatrics, University of California San Francisco, 521 Parnassus Ave, C-215, San Francisco, CA 94122-0663, USA. segh@itsa.ucsf.edu

Insights
Infants needing extracorporeal membrane oxygenation (ECMO) after heart surgery face high mortality. Survivors show significant rates of normal neurodevelopmental outcomes, emphasizing the need for neuroprotection strategies.
Area of Science:
- Pediatric Cardiology
- Neonatal Intensive Care
- Neurodevelopmental Pediatrics
Background:
- Congenital heart disease (CHD) necessitates complex surgical interventions.
- Extracorporeal membrane oxygenation (ECMO) is a critical life-support measure for infants with severe cardiopulmonary failure post-cardiac surgery.
- Long-term neurodevelopmental outcomes in this vulnerable population remain a significant concern.
Purpose of the Study:
- To assess the long-term neurodevelopmental status of infants treated with ECMO following cardiac surgery.
- To identify predictors of mortality and neurodevelopmental disability in these infants.
Main Methods:
- Retrospective review of 53 infants with CHD who received postoperative ECMO support (1990-2001).
- Clinical variables were extracted from medical records.
- Neurodevelopmental assessments (cognitive and neuromotor) were conducted at multiple time points up to 4.5 years of age.
Main Results:
- In-hospital survival was 32% (17/53).
- Among survivors, 50% had normal cognitive outcomes and 72% had normal neuromotor outcomes at follow-up.
- Longer aortic cross-clamp times (>40 minutes) were associated with abnormal cognitive outcomes in survivors.
Conclusions:
- Despite high mortality (68%), a substantial proportion of surviving infants treated with ECMO for CHD demonstrate normal neurodevelopmental outcomes.
- The study highlights the critical need for enhanced neuroprotective strategies during and after ECMO in infants with complex cardiac conditions.
- Aortic cross-clamp time emerged as a potential risk factor for cognitive impairment.
Objectives:
To evaluate the long-term neurodevelopmental outcome of infants who underwent cardiac surgery and required extracorporeal membrane oxygenation (ECMO) support, and to examine variables that predict death or disability in these patients.
Methods:
We studied all infants who had congenital heart disease and were supported postoperatively with ECMO from 1990 to 2001 at our institution (n = 53). Medical records were reviewed retrospectively to obtain clinical variables. Neurologic and age-appropriate developmental examinations occurred at ages 1, 1.5, 2.5, and 4.5 years. Median age at follow-up was 55 months (9-101). Cognitive outcome was defined as suspect when scores were between 1 and 2 SD below the mean for age and abnormal when scores were >2 SD below mean for age. Neuromotor outcome was defined as suspect when the patient manifested clumsiness, tremor, or mild tone and reflex changes without functional limitations, and abnormal when there were functional limitations.
Results:
In-hospital survival was 17 (32%) of 53. Of survivors, 14 (88%) of 16 are living and 1 patient was lost to follow-up. Of the 53 patients, 7 survived completely intact (13%). Seven (50%) of 14 patients had a normal cognitive outcome, 3 (21%) had a suspect cognitive outcome, and 4 (29%) were abnormal. Ten (72%) of 14 patients had a normal neuromotor outcome, 1 (7%) patient had a suspect neuromotor outcome, and 3 (21%) were abnormal. No survivor with an aortic cross-clamp time >40 minutes had a normal cognitive outcome. Nonsurvivors were more likely than survivors to have had cardiac arrest as an indication for ECMO (31% vs 6%), to have had a longer aortic cross-clamp time (mean 73 minutes vs 32 minutes), and to have required continuous arteriovenous hemofiltration (78% vs 35%). The age and weight at cannulation, gender, cardiac diagnosis, interval from surgery to ECMO, cardiopulmonary bypass time, diagnosis of sepsis or mediastinitis, and duration of ECMO were not significantly associated with survival.
Conclusions:
Although mortality was 68% in infants who had congenital heart disease and were treated with ECMO postoperatively, of those who survive to hospital discharge, 75% have a normal neuromotor outcome and 50% have a normal cognitive outcome. These high rates of mortality and disability suggest that increased attention be paid to neuroprotection in these complex disorders.


