Related Experiment Video
Updated: Jul 8, 2026

09:40

An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Double lumen esophagus due to reflux esophagitis with fibrous septom formation
Gastroenterology
|July 1, 1976

Abstract:
The unique endoscopic finding of a double lumen esophagus due to the development of a fibrous septum within an area of peptic reflux esophagitis is presented. The pathogenesis of this septum was felt to represent adherence to granulation tissue from opposing esophageal walls. This abnormality was easily managed by esophageal bouginage.


Related Concept Videos
 01:24
Esophagus
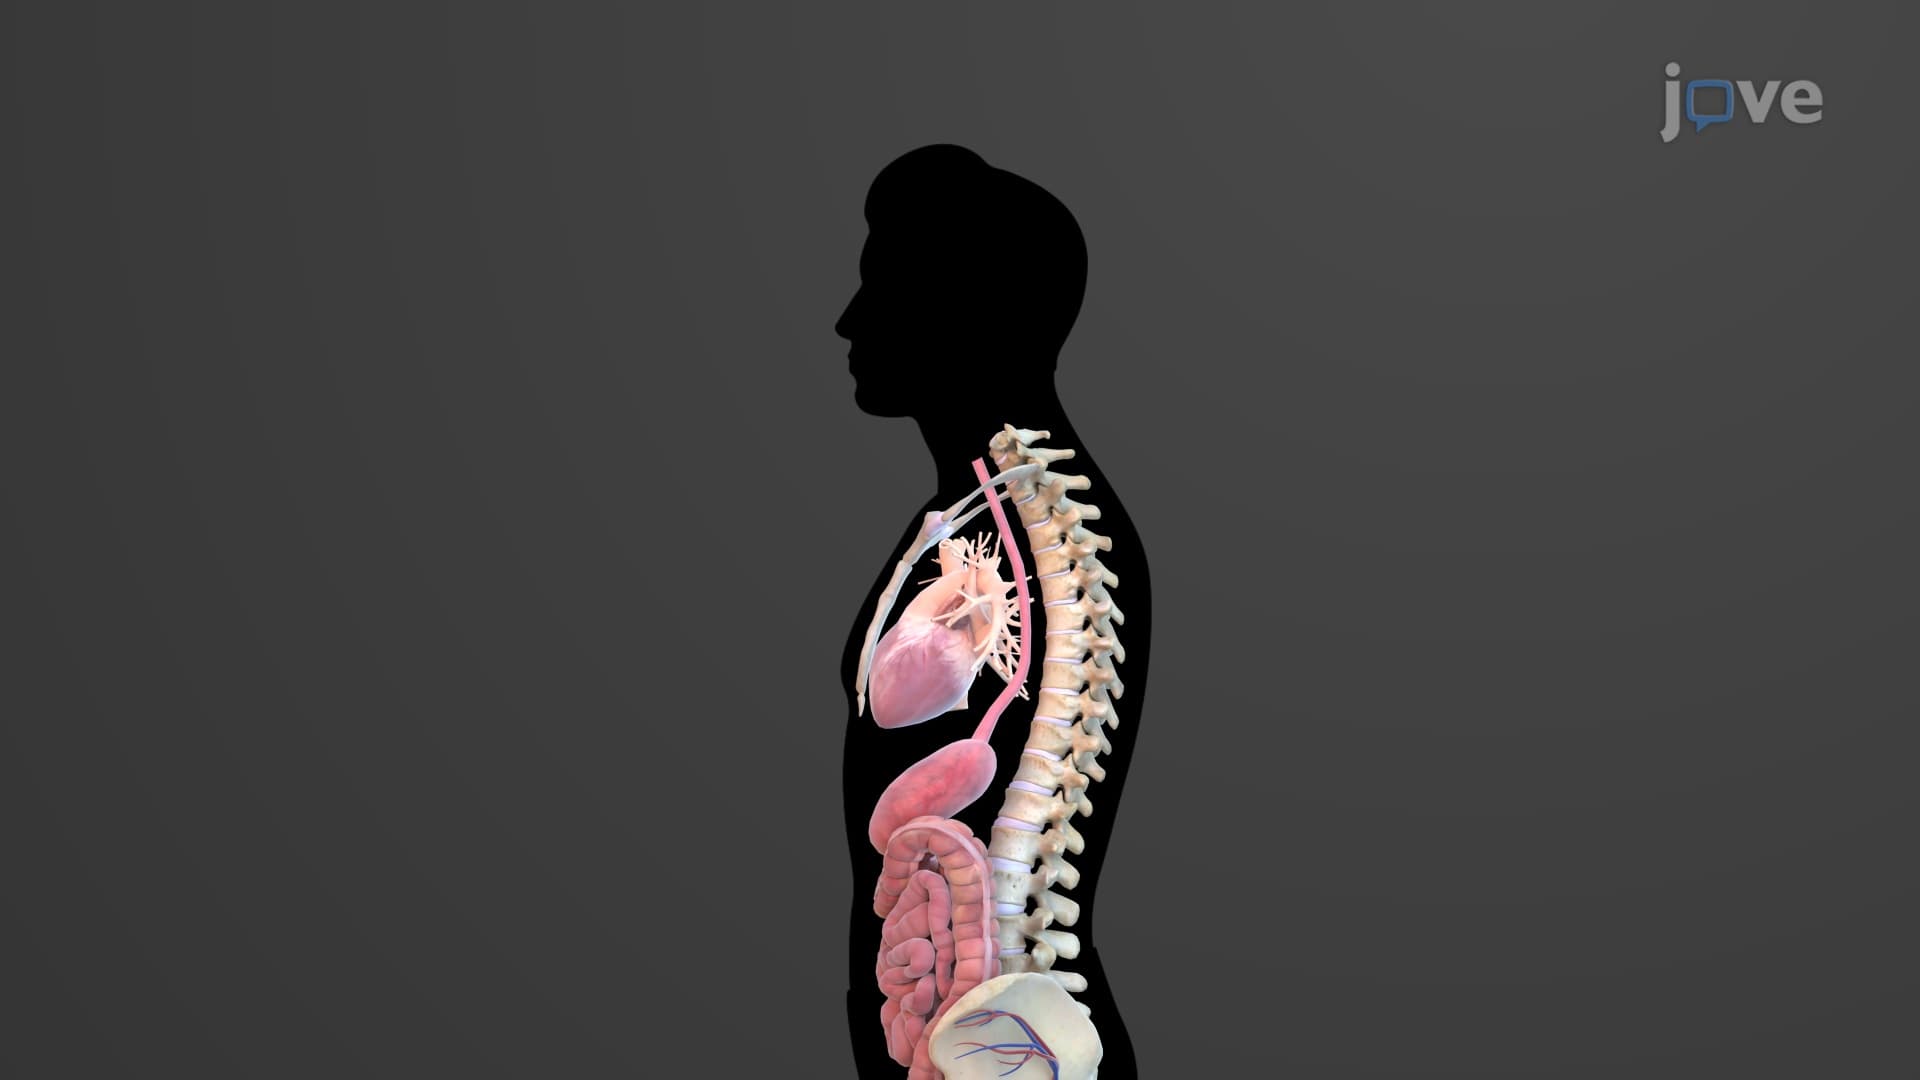
The esophagus, a muscular conduit linking the pharynx and stomach, measures roughly 10 inches (25.4 cm) and sits behind the trachea. It remains collapsed when not swallowing. The esophagus follows a predominantly straight path through the thoracic mediastinum and enters the abdominal cavity through a diaphragmatic opening known as the esophageal hiatus.
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
Individuals with Barrett's esophagus are often asymptomatic, but they may experience symptoms commonly associated with GERD, such as heartburn and acid regurgitation. Additional symptoms can include difficulty swallowing, chest pain, unintentional weight loss, blood in the stool (which may appear black, tarry, or bloody), and episodes of vomiting.
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Patients with esophageal strictures often experience a range of symptoms. Initially, they may have difficulty swallowing solid foods, which can progress to include liquids. Additional symptoms may involve chest pain or discomfort, regurgitating food and fluids, heartburn, unintentional weight loss, coughing or choking during meals, and hoarseness.
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
Gastroesophageal Reflux Disease
Gastroesophageal reflux disease (GERD) is the backward flow of stomach contents (acid, pepsin, or bile) into the esophagus, causing mucosal inflammation known as esophagitis. It results from failure of antireflux mechanisms, mainly the lower esophageal sphincter (LES), influenced by mechanical and physiological factors.Etiology and Risk FactorsGERD develops when LES function is weakened or when intra-abdominal pressure increases. Risk factors include aging, obesity, and sliding hiatal hernia,...
 01:25
Hiatal Hernia
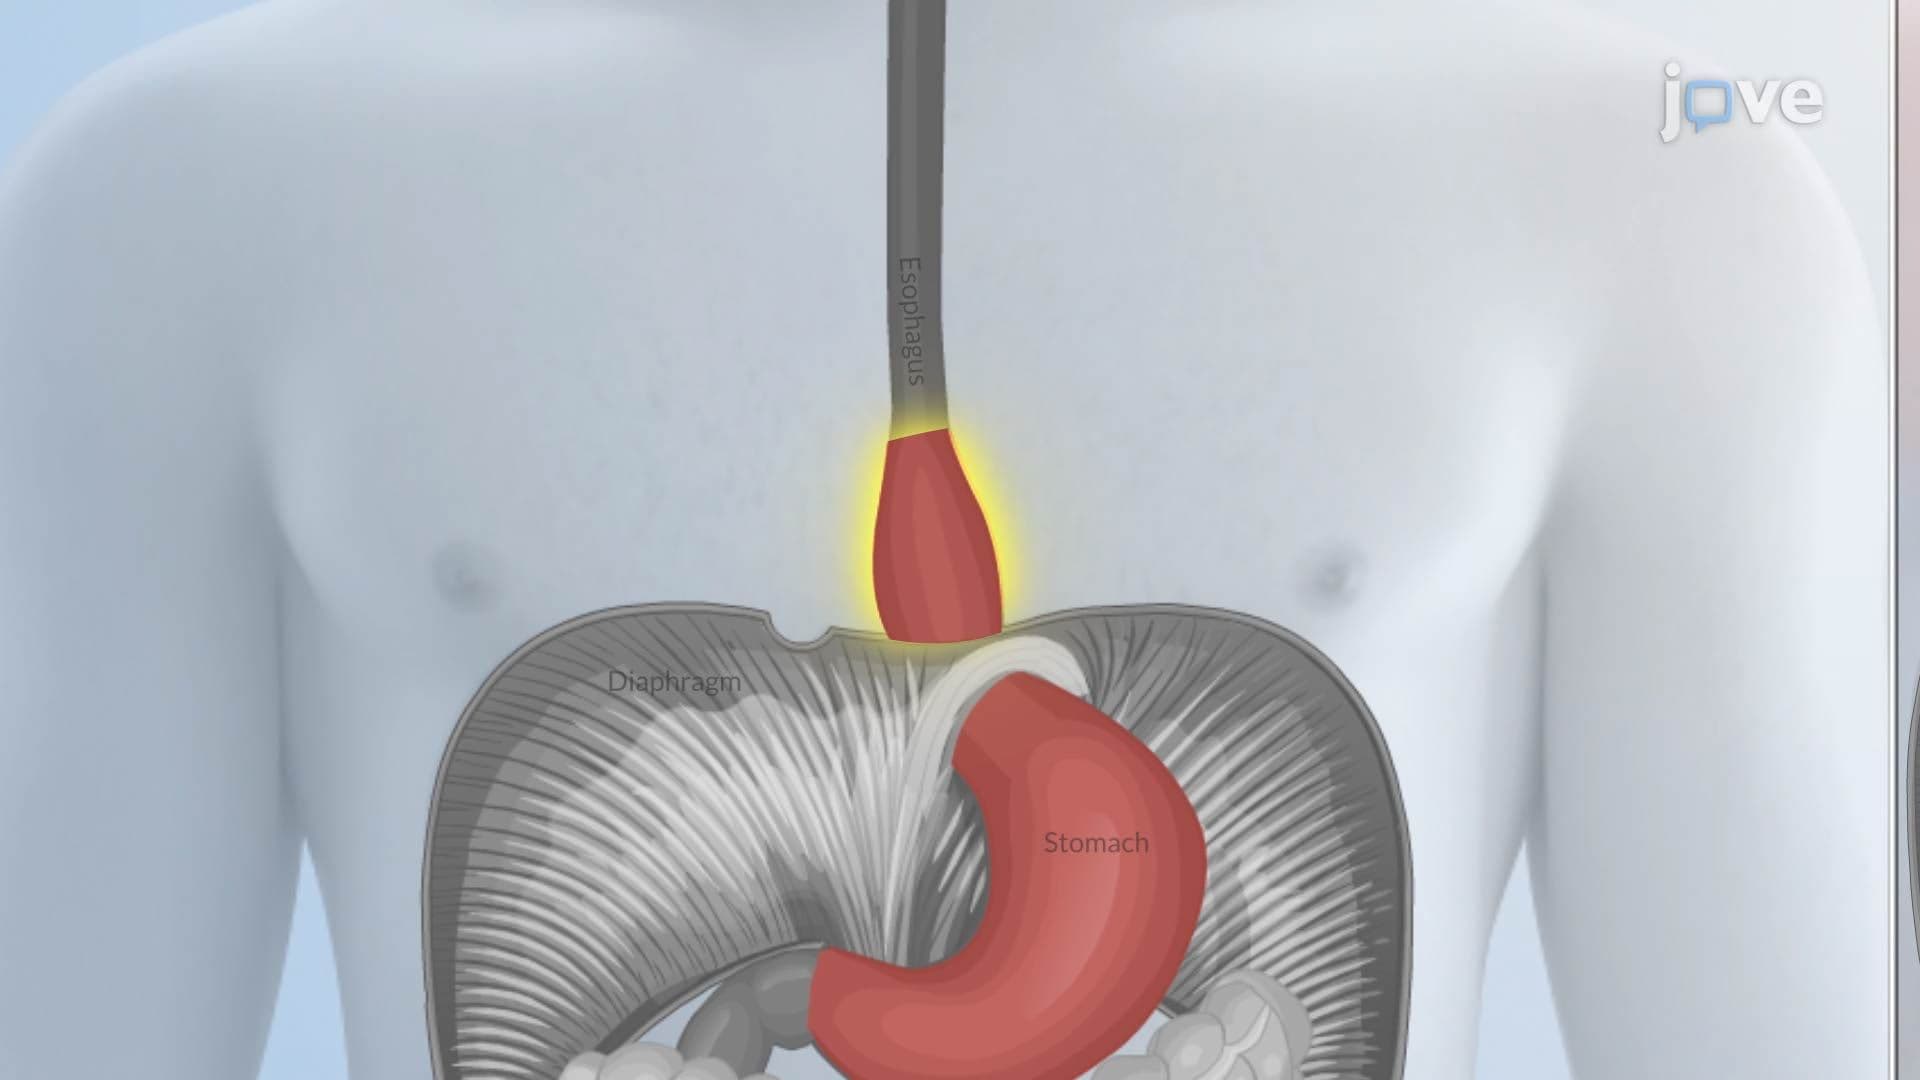
A hiatal hernia is the abnormal protrusion of the stomach or other abdominal organs through the esophageal hiatus of the diaphragm into the thoracic cavity.Normally, the gastroesophageal junction (GEJ) lies below the diaphragm and is supported by the phrenoesophageal membrane, the diaphragmatic crura, and connective tissues. Weakening of these structures—due to aging, congenital defects like a short esophagus, or increased intra-abdominal pressure from coughing, obesity, pregnancy, or heavy...