Related Experiment Video
Updated: Jul 20, 2026

Isolation of Human Atrial Myocytes for Simultaneous Measurements of Ca2+ Transients and Membrane Currents
Published on: July 3, 2013
The relevance of cellular to clinical electrophysiology in classifying antiarrhythmic actions
1Hertford College, Oxford University, England.

The division of class I antiarrhythmic agents (sodium-channel blockers) into Ia, Ib, and Ic subgroups was based on clinical observations. Lidocaine, mexiletine, and tocainide (Ib) did not alter the QRS or H-V interval in sinus rhythm, but prolonged effective refractory period (ERP) in spite of some shortening of the J-T interval. Encainide, flecainide, and lorcainide (Ic) widened the QRS and prolonged H-V in sinus rhythm and at low concentration, but had little effect on the ERP or J-T. These clinical findings could be explained by fast onset/offset kinetics of Ib drugs, that when used in high concentrations, blocked most sodium channels during the action potential plateau; therefore, at the beginning of diastole, insufficient drug-free channels were available to support conduction, and the ERP was prolonged. Rapid dissociation of the drugs after repolarization insured that by the end of diastole most channels were again drug free, so that the QRS and H-V were normal. The Ic compounds were more potent, but of slow onset, so that a steady-state block of Na channels was not achieved until after many beats. Offset was also slow, so that a proportion of channels was persistently unavailable, Na current was reduced, and conduction slowed, causing widening of the QRS and lengthening of H-V. Because the remaining drug-free channels were normal, they recovered rapidly from inactivation, and the ERP was not prolonged. By clinical criteria, moricizine also must be classed as Ic, and its offset/onset kinetics are much slower than those of Ib drugs.(ABSTRACT TRUNCATED AT 250 WORDS)
The division of class I antiarrhythmic agents (sodium-channel blockers) into Ia, Ib, and Ic subgroups was based on clinical observations. Lidocaine, mexiletine, and tocainide (Ib) did not alter the QRS or H-V interval in sinus rhythm, but prolonged effective refractory period (ERP) in spite of some shortening of the J-T interval. Encainide, flecainide, and lorcainide (Ic) widened the QRS and prolonged H-V in sinus rhythm and at low concentration, but had little effect on the ERP or J-T. These clinical findings could be explained by fast onset/offset kinetics of Ib drugs, that when used in high concentrations, blocked most sodium channels during the action potential plateau; therefore, at the beginning of diastole, insufficient drug-free channels were available to support conduction, and the ERP was prolonged. Rapid dissociation of the drugs after repolarization insured that by the end of diastole most channels were again drug free, so that the QRS and H-V were normal. The Ic compounds were more potent, but of slow onset, so that a steady-state block of Na channels was not achieved until after many beats. Offset was also slow, so that a proportion of channels was persistently unavailable, Na current was reduced, and conduction slowed, causing widening of the QRS and lengthening of H-V. Because the remaining drug-free channels were normal, they recovered rapidly from inactivation, and the ERP was not prolonged. By clinical criteria, moricizine also must be classed as Ic, and its offset/onset kinetics are much slower than those of Ib drugs.(ABSTRACT TRUNCATED AT 250 WORDS)


Related Concept Videos
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:30
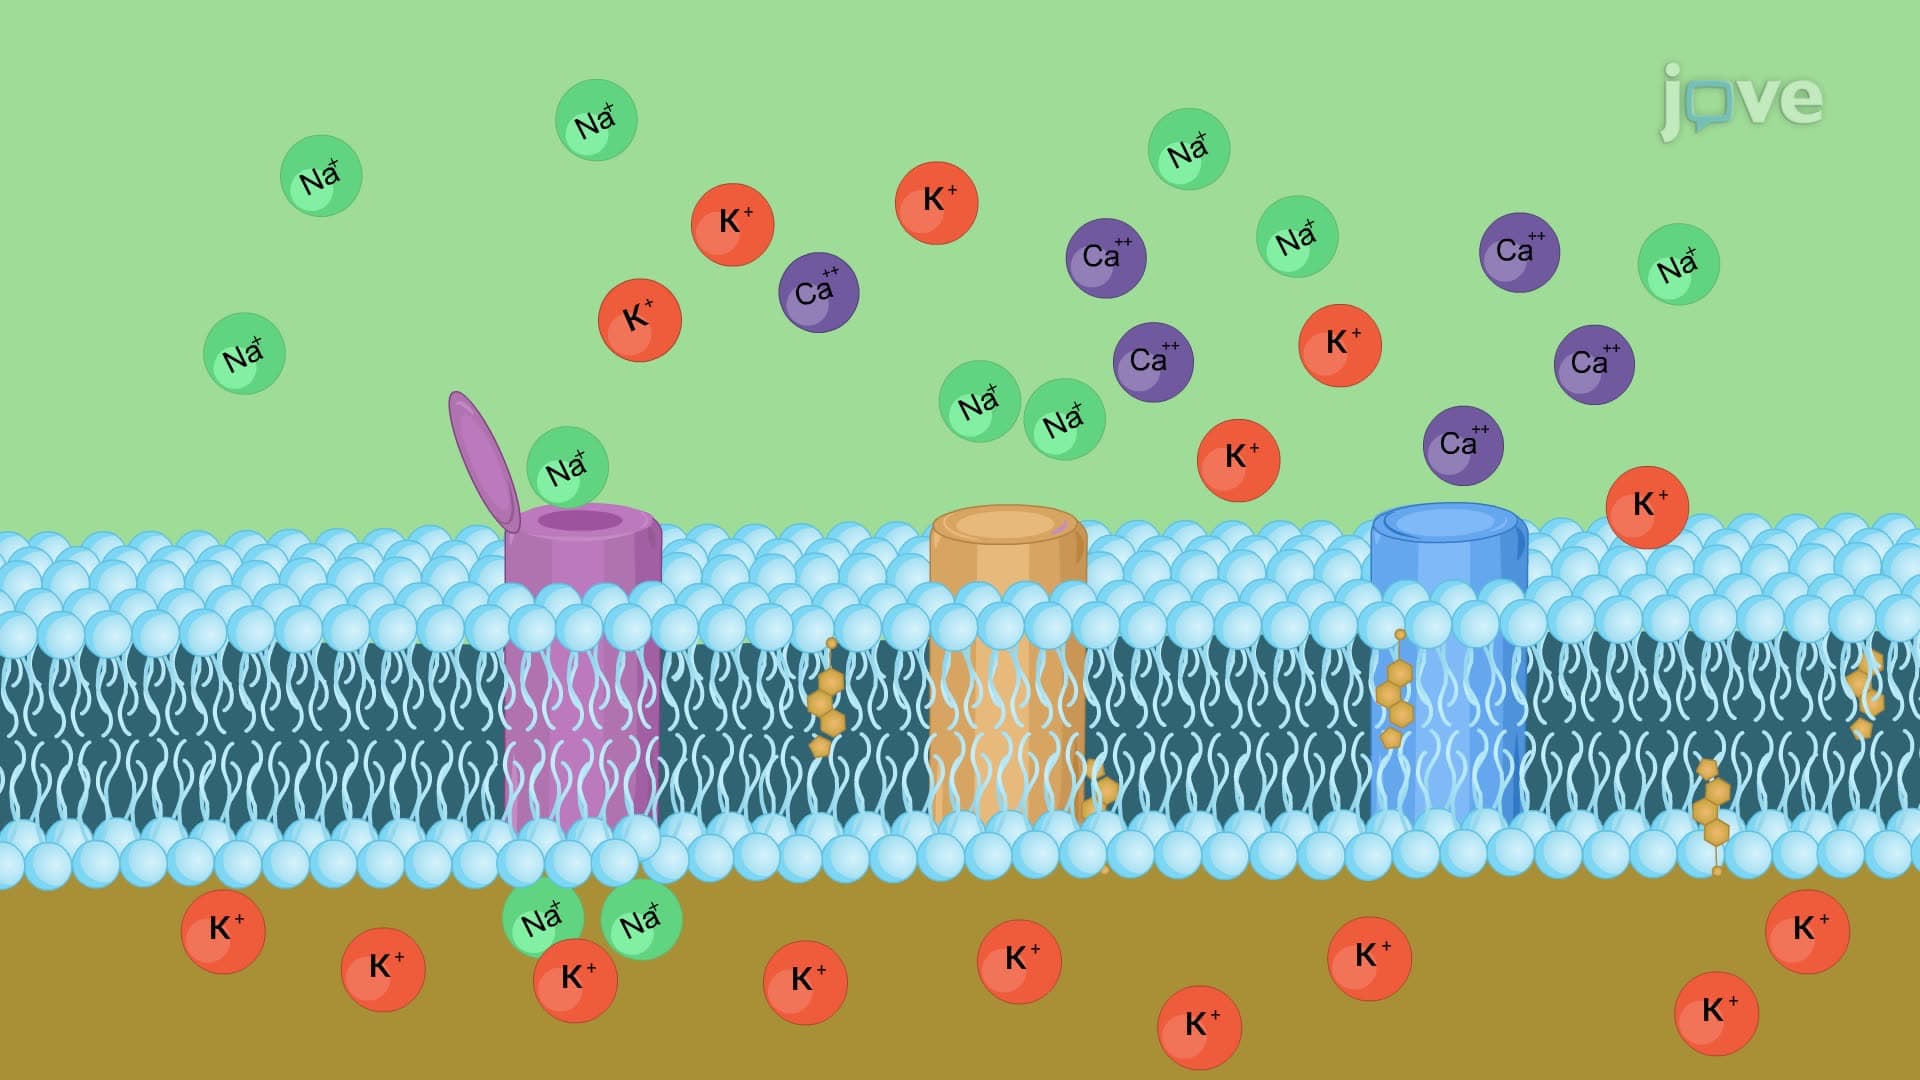
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials