Related Experiment Video
Updated: Aug 15, 2026
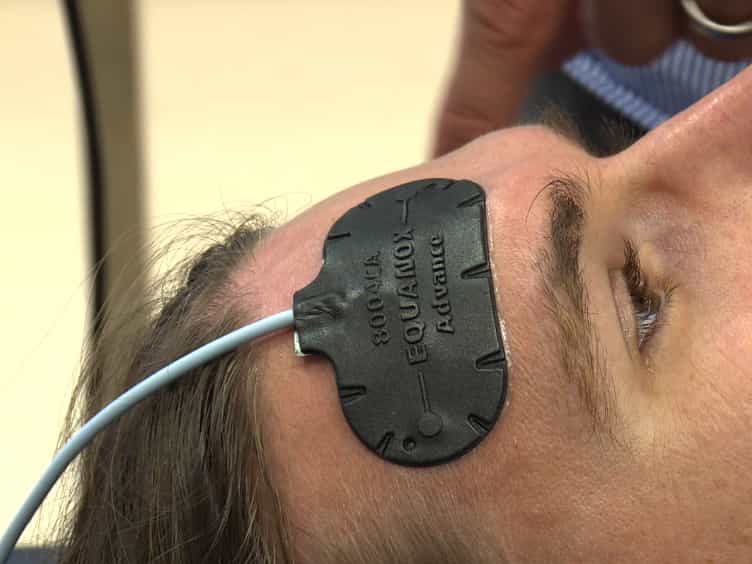

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
Case history of serious altitude decompression sickness following rapid rate of ascent
John A Gibbons1, Carol S Ramsey, James K Wright
1Air Force Research Laboratory, Biodynamics and Protection Division, AFRL/HEPR, High Altitude, Protection Research Brooks City-Base, San Antonio, TX 78235, USA. john.gibbons@brooks.af.mil

Abstract:
Neurologic and respiratory decompression sickness (DCS) symptoms occurring in the same individual represent complications rarely observed in altitude research. A case is presented of multi-symptom serious DCS resulting from exposure to 12,192 m (40,000 ft). Following 90 min of preoxygenation, the patient was decompressed in a hypobaric chamber from ground level to 12,192 m in 30 s. After 69 min at altitude he developed substernal chest pressure and the flight was immediately terminated. During the chamber descent the patient appeared disoriented. By 5486 m (18,000 ft) his chest pressure had resolved. The post-flight medical exam revealed multiple neurological abnormalities. He underwent a Table VI hyperbaric oxygen treatment with complete resolution of all abnormal neurological findings.
More Related Videos

Related Concept Videos
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:25
Hyperpnea and Hyperventilation
 01:30
Acute Respiratory Failure-III
 01:23
Acute Respiratory Failure-IV
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:27
Pneumothorax-II
Clinical Manifestations: