Related Experiment Video
Updated: Sep 25, 2026
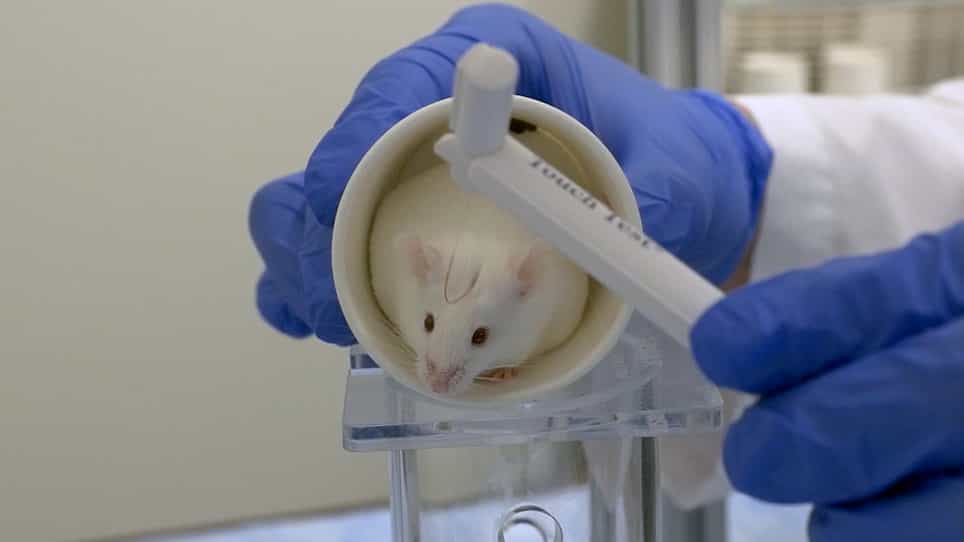
Dural Stimulation and Periorbital von Frey Testing in Mice As a Preclinical Model of Headache
Published on: July 29, 2021
[Postdural puncture headache: diagnosis, prevention and therapy]
U Schwarz1, C Schwan, M Strumpf
1Klinik für Anaesthesiologie, Intensiv- und Schmerztherapie der Berufsgenossenschaftlichen Kliniken Bergmannsheil, Universitätsklinik Bochum.

Abstract:
Lumbar puncture (LP) is a routine technique performed for a variety of procedures, e.g. diagnosis, administration of drugs, myelography and spinal anaesthesia. Postdural puncture headache is a common complication (30-40% in diagnostic LP). Prevention can be accomplished by using small-gauge needles (< or = 25 G) or pencil-point needles (22 G). Therapy should be carried out in a stepwise approach. The first step is bedrest, use of analgetics, i.v. fluids and an adequate guidance of the patient. The second step comprises special drug therapy. Several methods of pharmacologic management have been presented in the literature, but most of these are case reports. There is a lack of large double-blind placebo-controlled studies. Theophylline, caffeine, ACTH and sumatriptan are potentially promising agents for the treatment of postdural puncture headache. The efficacy of theophylline has been proven in a double-blind and placebo-controlled study. There are a few studies and case reports reporting that caffeine p.o. and i.v. is effective in the treatment of postdural puncture headache, but recurrence of headache after caffeine therapy is frequent. ACTH acts on a complex hormonal system. The treatment with sumatriptan has been reported in only a few case reports. The third step, and one of the most effective treatments of postdural puncture headache, is the epidural blood patch. The success rate ranges between 80 and 97%.
Related Concept Videos
 01:26
Brain Abscess l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:22
Bacterial Meningitis I: Introduction