Related Experiment Video
Updated: Sep 17, 2026

Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
[Primary or tertiary hypothyroidism as a cause of growth disturbances in 13-month old boy?]

Insights
Early diagnosis of primary hypothyroidism is possible through screening. This case highlights tertiary hypothyroidism in a child with short stature, emphasizing the need for comprehensive hypothalamic-pituitary-thyroid axis evaluation in unclear growth disorders.
Area of Science:
- Pediatric Endocrinology
- Metabolic Disorders
- Hormone Regulation
Context:
- Short stature is a common pediatric concern requiring thorough diagnostic evaluation.
- Screening examinations can detect primary hypothyroidism early, but other causes like insufficient TSH or TRH secretion exist.
- This case involves a 13-month-old boy presenting with significant short stature below the 3rd percentile.
Purpose:
- To investigate the cause of short stature in a 13-month-old boy.
- To evaluate the hypothalamic-pituitary-thyroid axis function.
- To determine the etiology of growth delay and potential hormonal deficiencies.
Summary:
- A 13-month-old boy with short stature showed normal psychomotor development but had a skeletal age of 3 months and elevated cholesterol.
- Investigations revealed normal thyroid hormone levels but increased TSH after TRH stimulation, suggesting tertiary hypothyroidism.
- Treatment with L-thyroxine normalized thyroid hormone levels and GH secretion.
Impact:
- This case underscores the importance of a full diagnostic workup of the hypothalamic-pituitary-thyroid axis in children with unexplained growth disorders.
- It highlights the potential for tertiary hypothyroidism, stemming from regulatory center insufficiency, to cause significant growth impairment.
- Prompt diagnosis and treatment with L-thyroxine can lead to normalization of hormone levels and improved growth outcomes.
Unlabelled:
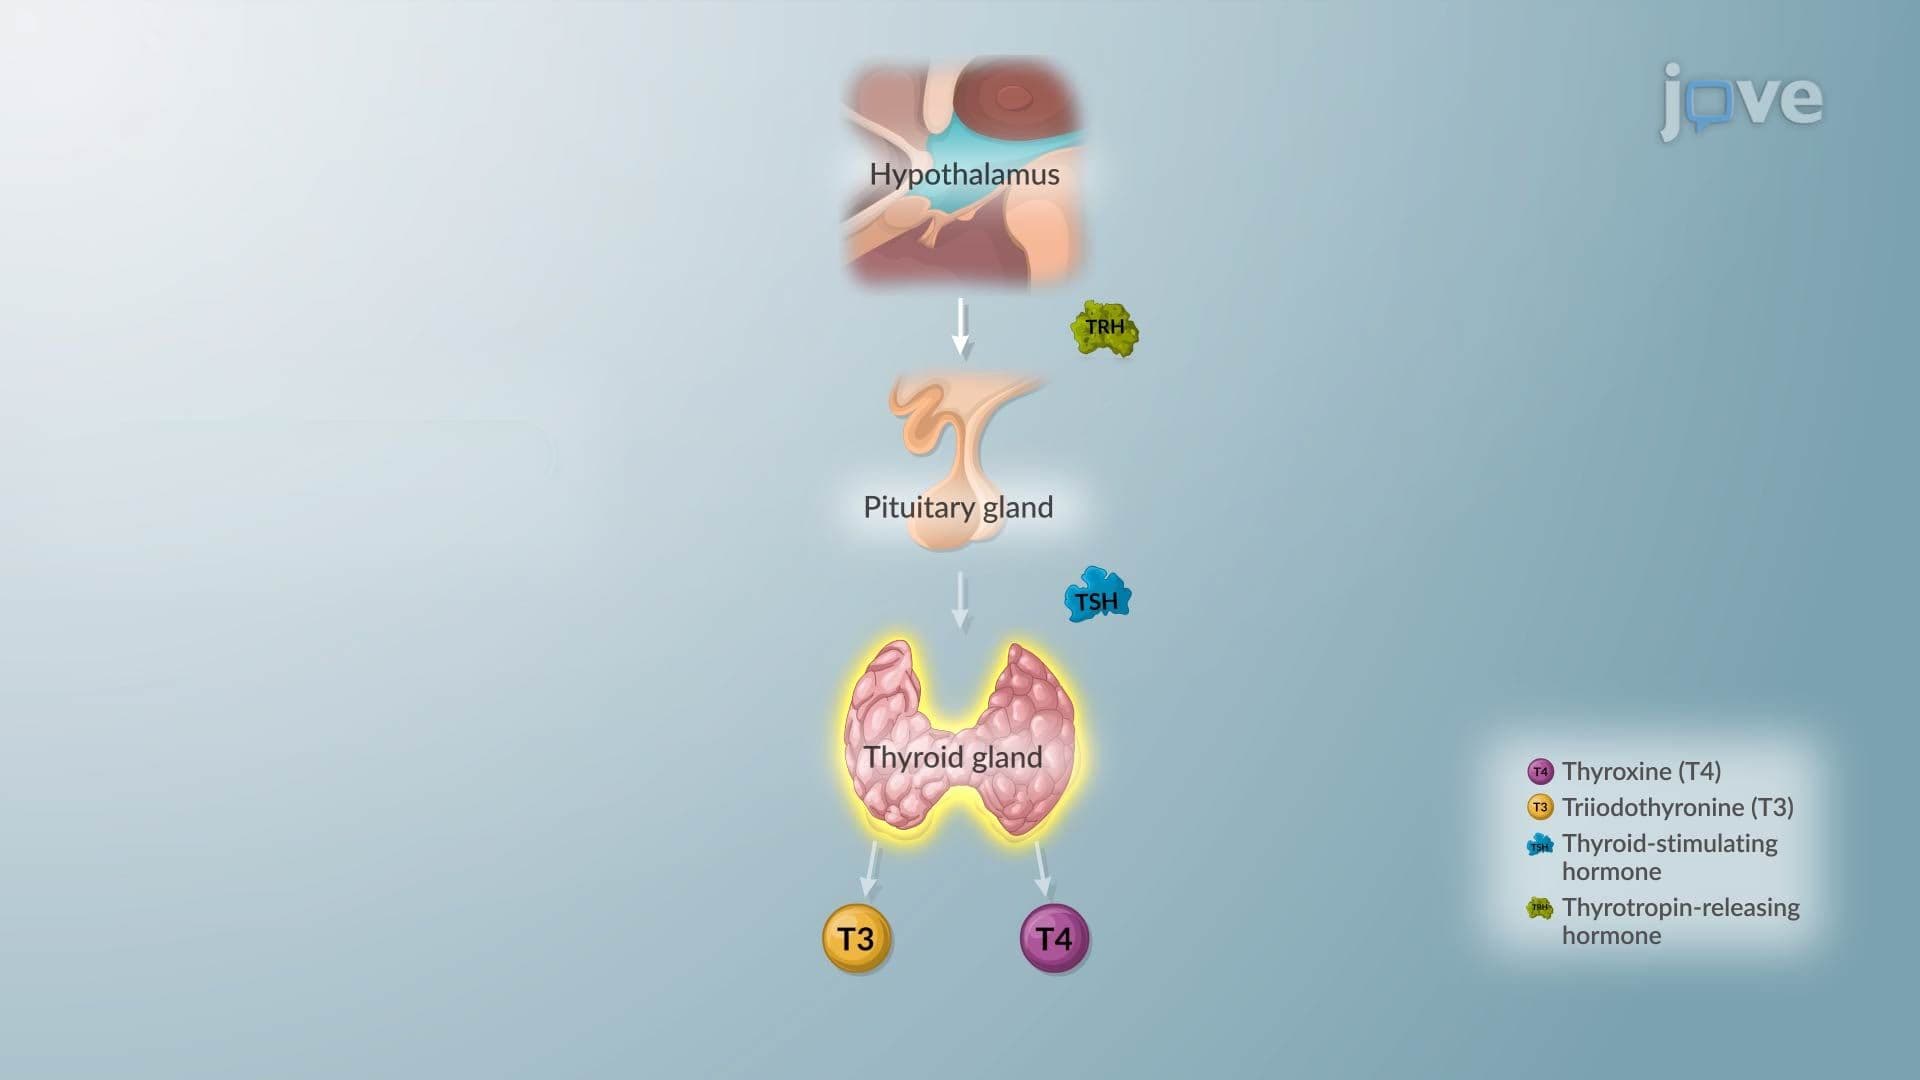
Due to the screening examination it is possible to diagnose primary hypothyreosis at the very beginning. On the other hand, hypothyreosis may be also caused by insufficient secretion of TSH or TRH. We present a 13-month old boy (A.I.) admitted to our Department because of short stature. The child was from normal pregnancy, birth spontaneous at full term with weight 4400 g, length 56 cm, 10 points in Apgar scale, TSH - 1,87 micro IU/ml in the screening examination. The psychomotor development was normal. At the admission the height was 72 cm (below 3 c), weight - 10,1 kg, body proportions normal, atresic fontanels, 7 teeth. Additional examinations revealed: skeletal age - 3 months, blood cell count normal, biochemical examinations normal except for level of cholesterol (209 mg/dl). We found lack of the GH secretion after clonidine. TSH value was slightly above normal range. The levels of free thyroid hormones, anti-TPO antibodies and thyroid ultrasonography were normal. The TSH level was increased in the stimulation test with TRH. Result of the MR examination of the brain was normal. On the basis of the whole picture tertiary hypothyreosis can not be excluded. The normalisation of thyroid hormone levels and GH in stimulation test with glucagone was obtained after therapy with L-thyroxine.
Conclusion:
In cases of unclear growing disorders the full diagnostics of the hypothalamic-hypophyseal-thyroid axis should be done because of the possibility of regulatory centres insufficiency.


Related Concept Videos
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Goiter
 01:23
Hypothyroidism II: Pathophysiology